How Ketamine-Assisted Psychotherapy Works, Step by Step
Zora Neuro Spa Editorial · September 18, 2026

The question "how does ketamine assisted psychotherapy work?" has a two-part answer: one part is pharmacology, and one part is conversation. This guide walks through the brain science, the three phases of a session arc, how the approach differs from a standalone infusion or Spravato, and what the published evidence does — and doesn't — yet show.
Quick Answer
Ketamine-assisted psychotherapy (KAP) is a structured treatment that pairs a clinician-monitored dose of ketamine with talk therapy before, during, and after the medicine session. Ketamine acts as an NMDA receptor antagonist (Ketamine — StatPearls), and researchers studying rapid-acting antidepressants describe a downstream cascade that temporarily makes the brain more adaptable. The therapy is what gives that adaptability direction. In short: the medicine may loosen rigid thinking, and the therapy works on what to do with the opening.
TL;DR
- KAP is not a standalone infusion — it bundles preparation, a monitored dosing session, and integration therapy into one protocol. See how the phases fit together
- Ketamine blocks NMDA receptors, and the resulting cascade is thought to support a period of heightened brain plasticity. Read the mechanism in plain English
- The plasticity is content-neutral. Structured therapy is what turns a chemical shift into a psychological one. Understand why the therapy hour matters
- KAP, IV ketamine alone, and Spravato differ in who's in the room, FDA status, and insurance pathways. Compare the three approaches side by side
- Not everyone is a candidate — blood pressure, psychiatric history, and pregnancy all factor in. Check the candidacy criteria
In This Article
- What Is Ketamine-Assisted Psychotherapy? — the definition, minus the marketing.
- How Does Ketamine Change the Brain During Therapy? — the receptor-level story.
- Why Does the Therapy Part Matter So Much? — the clay analogy.
- How Does Ketamine Assisted Psychotherapy Work Session by Session? — prep, dosing, integration.
- How Does KAP Compare to IV Ketamine Alone and Spravato? — a decision table.
- Does KAP Work for Treatment-Resistant Depression? — what the evidence supports.
- Who Is and Isn't a Good Candidate? — honest screening criteria.
- What Should You Ask a KAP Provider Before Booking? — eight questions.
- Frequently Asked Questions
What Is Ketamine-Assisted Psychotherapy?
KAP is a protocol in which a licensed therapist prepares you before a medically monitored ketamine dose, stays present or on call during it, and guides dedicated therapy sessions afterward. The medicine is one component. The relationship and the processing are the other two.
Integration refers to the therapy work that follows a dosing session, where emotions, images, and shifted perspectives get translated into language and concrete choices. Psycholytic dosing uses a lower dose that keeps you verbal and able to talk through material. Psychedelic dosing uses a higher dose that turns the session inward and mostly nonverbal, with the talking saved for afterward. Clinics choose between these based on your goals, your history, and the route of administration.
That's different from a plain IV infusion clinic model. In standalone IV ketamine therapy, the focus is the medical dose and monitoring, and any therapy you do happens separately with your own provider. It's also different from at-home oral ketamine offered through telehealth, where supervision and session structure vary considerably by program — ask any provider directly what monitoring they include.
⚠️ Watch the wording. "Ketamine therapy" and "ketamine-assisted psychotherapy" get used interchangeably in advertising, but they describe different services. If a therapist being in the room matters to you, ask specifically — don't assume the phrase guarantees it.
How Does Ketamine Change the Brain During Therapy?
Ketamine works differently from conventional antidepressants. It acts primarily as an NMDA receptor antagonist rather than by raising serotonin levels (Ketamine — StatPearls). In psychiatric use, doses are low and subanesthetic — well below the levels used for surgical anesthesia.
Researchers studying rapid-acting antidepressants describe a chain of events that follows that receptor blockade:
- NMDA blockade on certain inhibitory neurons reduces their braking effect.
- A glutamate surge follows, since glutamate is the brain's main excitatory messenger.
- AMPA receptor activation carries that signal forward.
- Growth-factor signaling (BDNF and the mTOR pathway) is the step most often proposed as the link to structural change.
- New synaptic connections in prefrontal circuits are the outcome this line of research is investigating.
The practical version is friendlier. Depression, anxiety, and PTSD tend to run on grooves — the same thought arriving the same way, hundreds of times a day. What people commonly report during a session is that those grooves feel less fixed, and that they can look at a painful memory or belief from a slight distance rather than from inside it.
That distance is the therapeutic opportunity. For the deeper neuroscience walkthrough, including how this differs from the SSRI mechanism, see our explainer on how ketamine works on the brain.
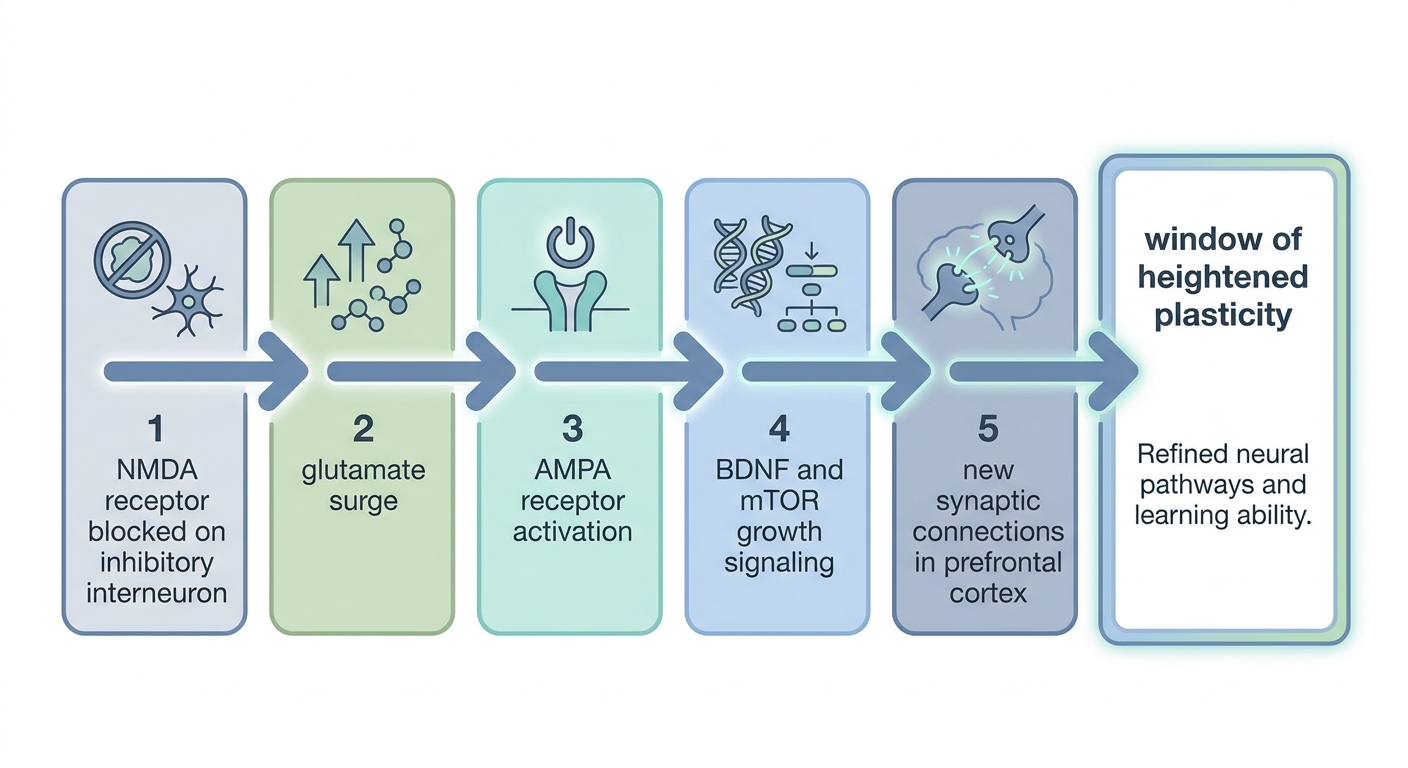
Key takeaway: Ketamine's antidepressant mechanism is still being mapped, but the working model is that it opens a temporary period of increased adaptability rather than delivering a fixed chemical correction.
Why Does the Therapy Part Matter So Much?
Because plasticity is content-neutral. A more adaptable brain is more open to new patterns — but nothing about that state decides which patterns. Left unstructured, the same well-worn grooves are the ones most likely to get reinforced.
The neuroplasticity window refers to the limited period after dosing when the brain is thought to be unusually receptive to new learning. Think of it like clay that's been warmed and softened. It can be reshaped, but it will also harden again — into whatever shape it was left in.
Structured therapy is how clinicians try to influence that shape. During the session, a therapist provides safety and gentle guidance. Afterward, integration sessions name what surfaced and connect it to something you'll actually do differently this week.
Trials combining ketamine with a formal psychotherapy protocol — cognitive behavioral therapy, for example — have been published, and researchers in this area are actively testing whether added therapy helps sustain improvement. That evidence base is still smaller and more varied than the infusion-only literature, so treat "therapy extends the benefit" as a reasonable clinical hypothesis under study rather than a settled finding. Discuss expectations with your own prescriber.
Who does this work matters too. Some clinics employ therapists in-house; others coordinate with an outside clinician. If you want to understand that role in more detail, read about working with a ketamine integration therapist.
How Does Ketamine Assisted Psychotherapy Work Session by Session?
A full KAP arc has three phases: preparation, the medicine session, and integration. Most programs schedule one or two preparation meetings, set aside several hours for each dosing day, and book integration therapy soon afterward — often within a few days, while the window is thought to be open.
If you want the procedural detail on the medical side specifically, see what to expect from IV ketamine.
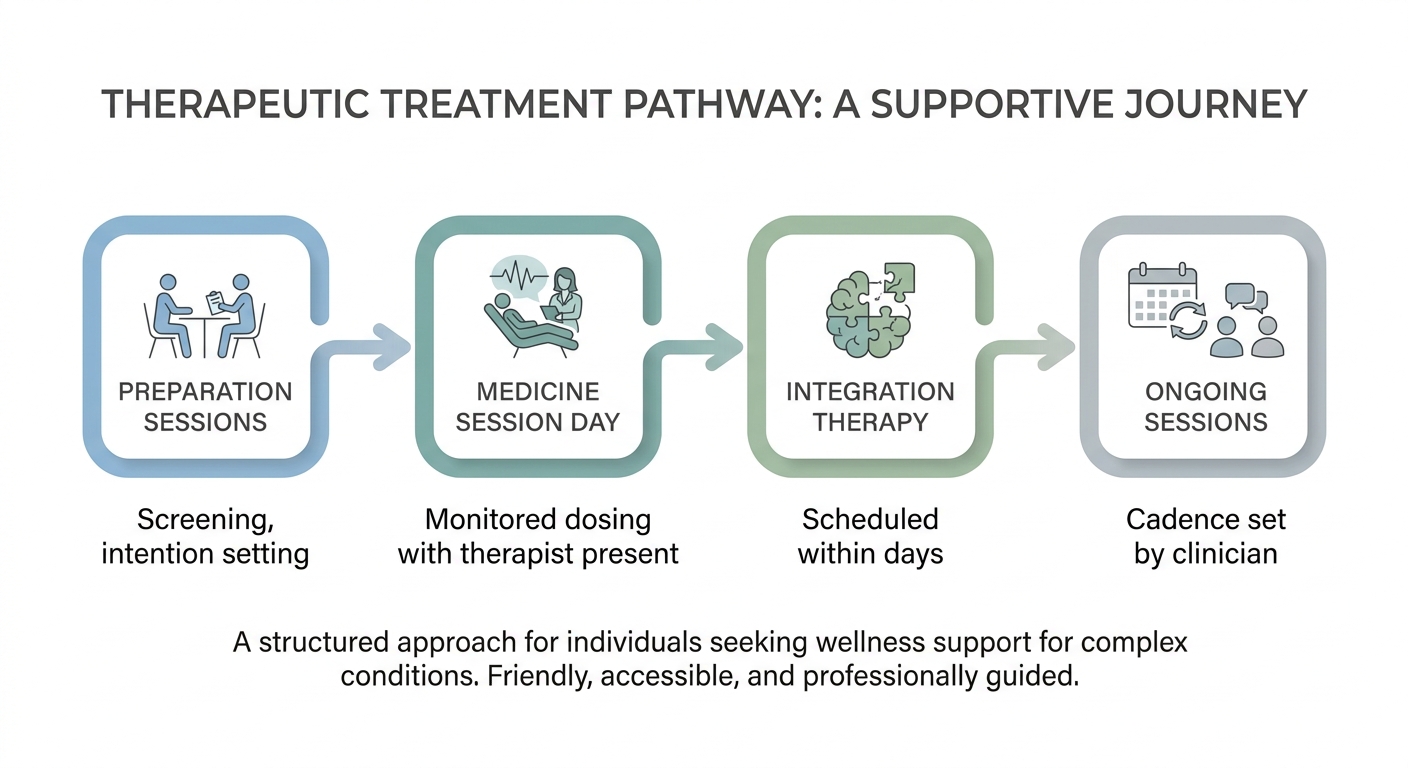
Key takeaway: The dosing hour gets the attention, but the preparation and integration hours are what make it psychotherapy rather than a medication appointment.
Phase 1: Preparation — What Do You Talk About Beforehand?
Preparation covers screening, logistics, and intention. Your clinician reviews your medical and psychiatric history, current medications, blood pressure, and prior treatment attempts. Some medications are thought to influence the session experience, which is one reason the full list gets reviewed by your prescriber.
The therapy side of preparation focuses on what you want to work on and what you'll do if the experience gets intense. Rehearsing that in advance is the point — "I'll notice my breath, and my therapist is right here" is easier to use when you practiced it sober.
A typical pre-session checklist:
- Confirm your ride home — you cannot drive after dosing.
- Follow fasting instructions — many clinics ask you to skip food for several hours, since nausea is a recognized adverse effect (Ketamine — StatPearls).
- Bring or choose music — a curated playlist and headphones are standard in most KAP models.
- Pack comfort items — eye mask, blanket, layers.
- Write one intention — a question or theme, not a demand for a specific outcome.
- Tell your clinician about any medication change, however small.
Phase 2: The Medicine Session — What Does the Therapist Actually Do?
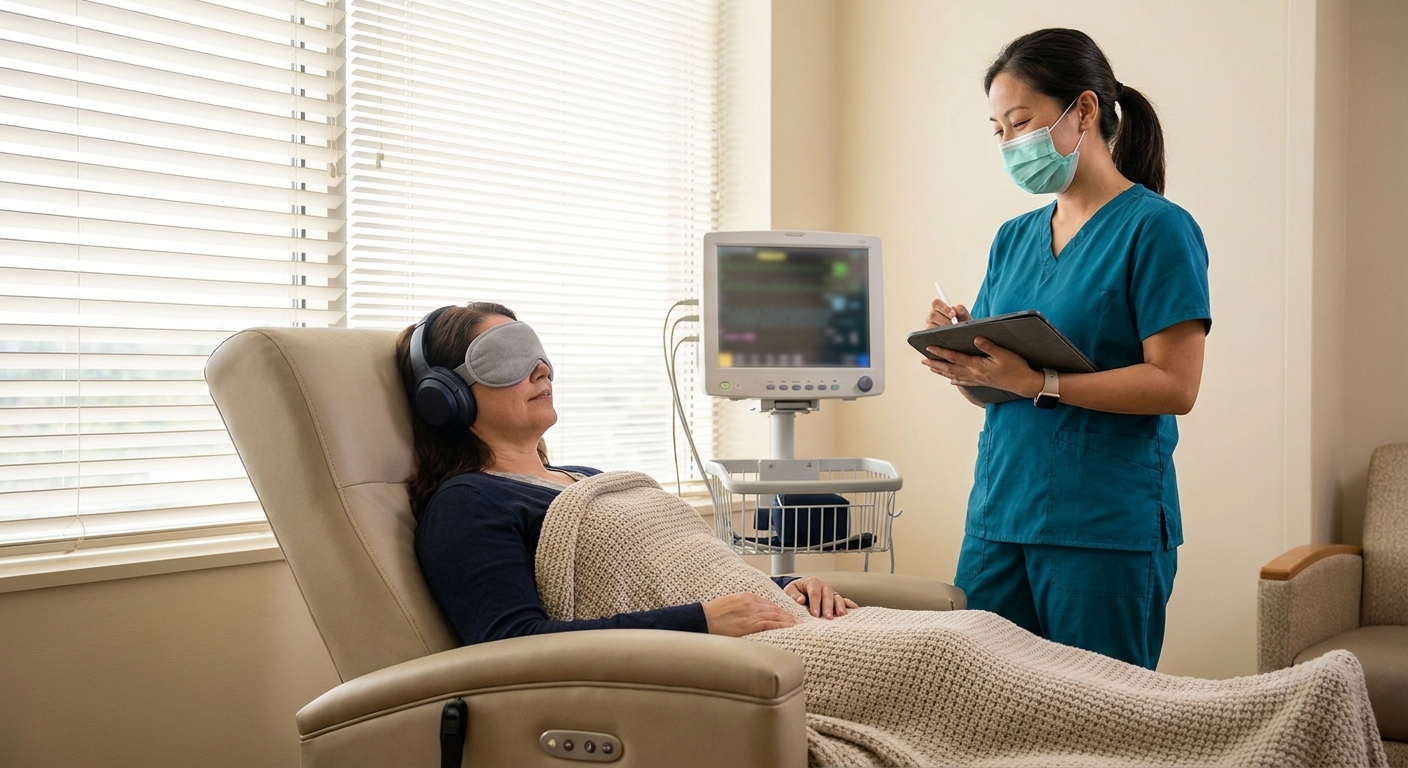
Mostly, the therapist holds quiet, attentive presence. In psychedelic-dose KAP, the dosing period is largely nonverbal: you recline with an eye mask and music while the therapist stays nearby, available if you need grounding. As effects taper, they invite you to start putting words to what happened.
Route of administration shapes the session:
| Route | How it's given | Session shape |
|---|---|---|
| IV infusion | Slow infusion through an IV line | Tightly controlled, clinician can adjust mid-session |
| Intramuscular (IM) | Single injection | No line to manage; dose is fixed once given |
| Sublingual troche | Lozenge dissolved under the tongue | Gentler onset and a longer, often more verbal session |
Medical monitoring runs alongside the therapy. Blood pressure increases and dissociative effects are recognized effects of ketamine and esketamine, which is why vitals are checked and staff remain available throughout (SPRAVATO prescribing information). Anti-nausea medication is typically on hand.
Phase 3: Integration — How Do Insights Become Change?
Integration is the therapy session where you translate the experience into something usable. A session can produce vivid imagery, an unexpected wave of grief, or a sudden sense of perspective on a relationship. On its own, that's a memory. Integration turns it into a plan.
Common integration tools:
- Guided journaling within a day of dosing, before details fade.
- Body-based practices — breathwork, walking, gentle movement — to stay connected to what shifted.
- Behavioral homework — one small, specific action tied to the insight.
- Values clarification — naming what you actually want your weeks to look like.
Scheduling matters here. Because the plasticity window is thought to be time-limited, most KAP models place integration soon after dosing rather than weeks later.
How Does KAP Compare to IV Ketamine Alone and Spravato?
The core difference is who's in the room and what's billable. KAP adds a therapist and structured processing. Standalone IV ketamine focuses on the medical dose. Spravato (esketamine) nasal spray is FDA-approved for treatment-resistant depression in adults in conjunction with an oral antidepressant, is available only through a restricted REMS program, and requires that patients be monitored by a healthcare provider for at least two hours after each dose (SPRAVATO prescribing information, FDA label as of September 2026).
| Approach | Therapist present during dosing | FDA status for depression | Monitoring setting | Often considered by |
|---|---|---|---|---|
| KAP | Yes — core to the model | Ketamine is used off-label for depression | In-clinic, therapist plus medical staff | People who want the psychological work built in |
| IV ketamine infusion | Not typically | Off-label for depression | In-clinic, medically supervised | People with an existing outside therapist |
| Spravato (esketamine) | Not built into the protocol | FDA-approved for TRD with an oral antidepressant | In-clinic under a REMS program, with post-dose observation | People prioritizing an insurance pathway |
| At-home oral ketamine | Varies by program — ask | Off-label | Varies considerably; confirm before enrolling | People weighing access against supervision |
Ketamine's FDA-approved indication is as an anesthetic agent, so psychiatric use is off-label prescribing (Ketamine — StatPearls). Off-label doesn't mean unstudied — it means the manufacturer never sought that specific approval. For a closer look at the two most common in-clinic options, see our breakdown of Spravato vs IV ketamine.
Cost usually tracks with staffing. A session that includes a therapist for several hours is priced differently than a nurse-monitored infusion, and the therapy portion may be billed separately.
Does KAP Work for Treatment-Resistant Depression?
Treatment-resistant depression (TRD) refers to depression that hasn't responded adequately to multiple antidepressant trials — the clinical program behind SPRAVATO enrolled adults with inadequate response to at least two prior antidepressants (SPRAVATO prescribing information). Depression is common and highly treatable for many people, but a meaningful portion of patients don't improve on first-line options (Depression — NIMH).
Here's the honest state of the evidence, in three parts:
- Ketamine and esketamine for TRD are the best-studied piece. Esketamine has an FDA-approved indication for this population, which reflects completed controlled trials (FDA label).
- Ketamine plus a defined psychotherapy has been tested, and researchers are examining whether the added therapy helps maintain improvement. These studies are generally smaller, and therapy protocols differ between them.
- KAP as delivered in private clinics varies widely in dose, route, therapist training, and session count, which makes clinic-level results hard to compare with trial results.
What that means for you: ketamine-based treatment is an established option for TRD, and adding therapy is a rational, actively studied extension of it — not a guaranteed upgrade. Individual results vary, and relapse can occur, which is why most programs plan ongoing sessions rather than a single course.
If you're weighing options after several failed medication trials, our guide to treatment-resistant depression help in Idaho covers the broader landscape, including non-ketamine approaches.
Key takeaway: The strongest evidence sits with ketamine and esketamine themselves; the therapy layer is a promising, still-maturing area of research. A good provider will tell you that plainly.
Who Is and Isn't a Good Candidate?
Candidacy is decided in a clinical consultation, not by an article. That said, providers screen along fairly consistent lines, and knowing them helps you prepare.
| Often a reasonable fit | Needs closer evaluation first |
|---|---|
| Treatment-resistant depression after multiple medication trials | Uncontrolled or poorly controlled high blood pressure |
| PTSD, anxiety, or OCD symptoms that haven't responded to standard care | Active psychosis or a history of mania |
| Stable vitals and no unstable cardiac or vascular disease | Significant cardiac, vascular, or aneurysm history |
| An established therapy relationship or willingness to start one | Pregnancy or breastfeeding |
| Ability to arrange transportation and time for integration | Untreated substance use disorder, including alcohol |
| Realistic expectations about a process, not a one-visit fix | Certain liver, thyroid, or neurological conditions |
Blood pressure elevation and dissociative or sedative effects are documented effects of this drug class, which is why cardiovascular and psychiatric screening come first (SPRAVATO prescribing information; Ketamine — StatPearls).
⚠️ Never stop a psychiatric medication on your own to prepare for a consultation. Any change to antidepressants, mood stabilizers, or benzodiazepines should be made by the prescriber who manages them.
Our clinic evaluates candidacy for depression, PTSD, anxiety, OCD, chronic pain, and migraine across our ketamine therapy services in Boise and Eagle, and a consultation includes an honest answer about whether KAP, an infusion series, or a different path fits your history best.

What Should You Ask a KAP Provider Before Booking?
Ask about staffing, structure, and safety — in that order. Thin clinic pages often list services without answering any of this, so put the questions directly to the practice.
- Who is physically in the room during dosing? A good answer names roles and licenses, not just "our team."
- What KAP-specific training does the therapist have? Look for a named training program and a current clinical license.
- How many preparation sessions are included? A clear number, with what each covers.
- When is integration scheduled relative to dosing? Soon after, with a specific interval — not "whenever you'd like."
- How is each component billed? Medicine, monitoring, and therapy are often priced separately. Get it itemized in writing.
- What route and dosing approach do you use, and why? They should tie the choice to your goals and history.
- What's the emergency protocol? Expect specifics: vitals monitoring, blood pressure management, who is on site, when they'd stop a session.
- What happens if I don't respond? A trustworthy provider has a plan B and will say so before you pay for a series.
If the answers feel rehearsed or vague, keep looking. Our 5-step checklist for choosing a clinic adds credentialing and safety items worth verifying before you commit.
Frequently Asked Questions
Short, direct answers to what people ask most before their first consultation.
How many KAP sessions do most people need?
Protocols vary by clinician and condition. Many depression programs are structured as a series of medicine sessions over a two-to-three-week period, paired with at least two integration therapy sessions, followed by less frequent sessions on a cadence your provider sets. Your actual plan depends on your history, response, and goals — which is why the number is decided in consultation rather than quoted in advance.
Is ketamine-assisted psychotherapy covered by insurance?
Coverage is usually split. IV ketamine for depression is off-label (Ketamine — StatPearls), so the medicine and monitoring are commonly paid out of pocket, while the psychotherapy hour may be billable under standard psychotherapy codes. Spravato, being FDA-approved for treatment-resistant depression, more often has an insurance pathway. Plans differ — verify directly with your insurer. Our guide to ketamine therapy costs in Idaho explains what to ask.
Do you have to talk during the ketamine session?
No. In most psychedelic-dose KAP models, the dosing period is intentionally quiet and inward — eye mask, music, minimal conversation. The therapist is present for safety and grounding, not interrogation. Verbal processing typically begins as effects taper and continues in your integration session. Lower psycholytic doses are more conversational, so ask which approach your clinic uses.
Can you do KAP if you're already seeing your own therapist?
Yes, and many people prefer it. Clinics frequently handle the medical screening and dosing while your existing therapist leads integration, coordinated through a signed release of information. Continuity is a real advantage — your therapist already knows your history. Confirm in advance that both sides are willing to communicate, and that your therapist is comfortable supporting integration work.
Summary: What's the Next Step If This Sounds Like a Fit?
So, how does ketamine assisted psychotherapy work? It works in three linked parts: preparation that sets an intention and clears you medically, a monitored dosing session with a therapist present, and integration therapy that turns what surfaced into something you can act on. The mechanism researchers point to is a temporary window of heightened brain plasticity — and the therapy is what fills it.
The next step is a consultation, not a commitment. A clinician reviews your diagnosis history, medications, blood pressure, and goals, then tells you honestly whether ketamine-assisted psychotherapy, a standalone infusion series, Spravato, or something else entirely makes the most sense. If you're in the Boise or Eagle area and want that conversation, you can request a ketamine consultation and get clear answers before anything is scheduled. Individual results vary, and suitability is always determined clinically.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.