Why Ketamine-Assisted Psychotherapy Works: The Mechanism
Zora Neuro Spa Editorial · October 3, 2026
Ketamine-assisted psychotherapy sits at an unusual intersection: a medicine that changes brain chemistry for a few hours, paired with a conversation that can shape what happens next. If you've been researching ketamine therapy in Boise and keep running into vague promises, this guide takes a different route — it explains how does ketamine assisted psychotherapy work at the level of receptors, timing, and session design. You'll learn what the drug actually does, why the therapy half isn't optional, and how to judge whether a program is built well.
Quick Answer
Ketamine-assisted psychotherapy (KAP) is a treatment model that pairs a supervised sub-anesthetic dose of ketamine with structured therapy sessions before and after dosing. Ketamine blocks NMDA receptors — a type of glutamate receptor in the brain — which researchers believe triggers a cascade ending in new synaptic connections. That shift is thought to create a short period of heightened flexibility. The therapy is what gives that flexibility a direction.
TL;DR
- Ketamine is classified as an NMDA receptor antagonist, and researchers link that action to downstream changes in synaptic signaling. See the receptor-to-synapse cascade explained
- A more flexible brain is not automatically a healthier one — plasticity is directionally neutral, which is the entire argument for adding therapy. Read why the therapy half carries the weight
- A KAP course has three moving parts: preparation, dosing, and integration — each scheduled deliberately. Walk through the full course structure
- Infusion-only care and KAP differ in who's in the room, session length, and cost. Compare KAP against infusion-only ketamine
- Candidacy depends on diagnosis, prior medication trials, cardiovascular status, and psychiatric history. Check the candidacy and exclusion criteria
In This Article
Here's the path we'll take, from receptors to the questions you should ask a Boise or Eagle clinic before booking.
- What Happens in the Brain During Ketamine-Assisted Psychotherapy?
- Why Does the Therapy Part Matter at All?
- How Is a KAP Course Structured, Start to Finish?
- KAP vs Infusion-Only Ketamine: What's the Real Difference?
- Does KAP Work With Spravato, or Only IV Ketamine?
- Who Is a Good Candidate for Ketamine-Assisted Psychotherapy?
- How Long Do the Effects of KAP Last?
- What Should You Ask a Clinic Before Starting KAP?
What Happens in the Brain During Ketamine-Assisted Psychotherapy?
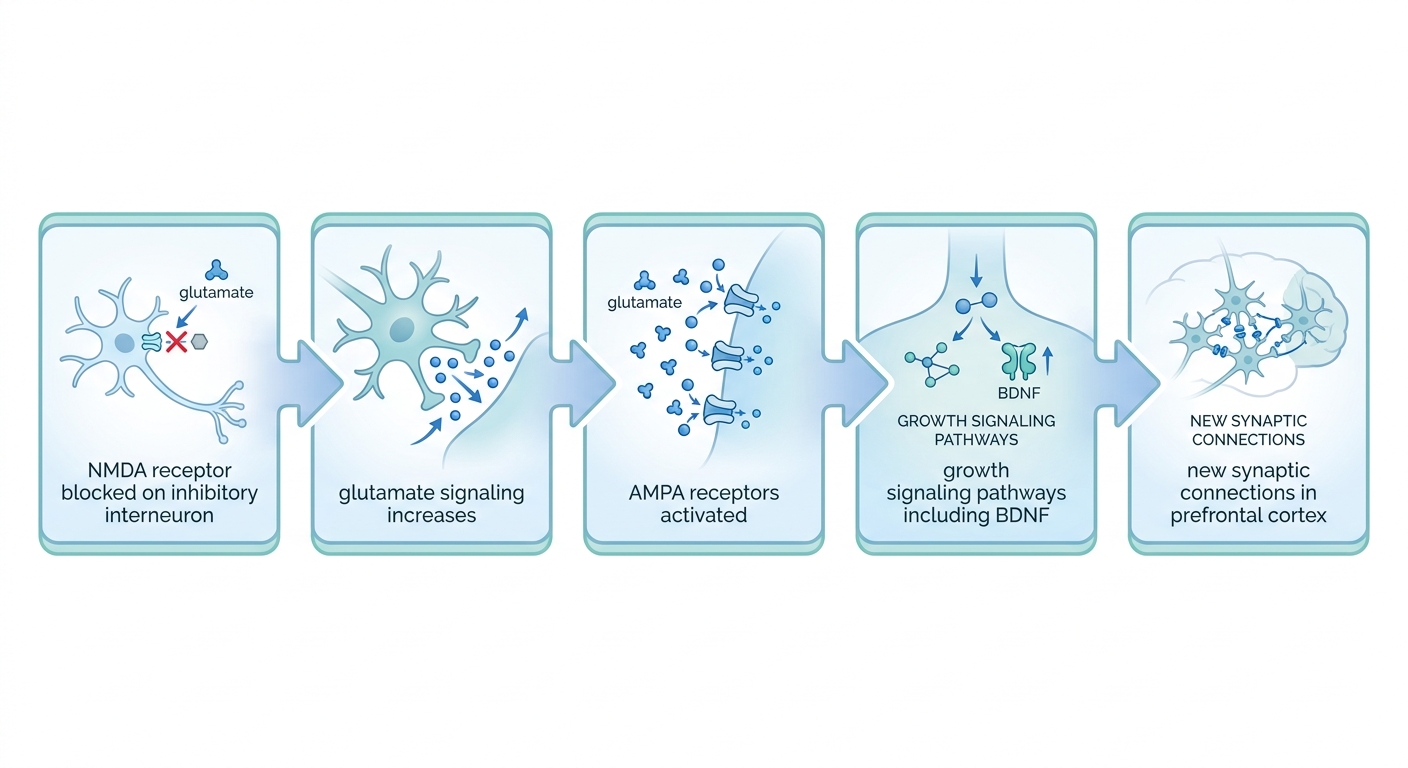
Ketamine is a dissociative anesthetic that acts primarily as an NMDA receptor antagonist — meaning it blocks a specific gateway that the neurotransmitter glutamate normally uses, as described in the clinical monograph on ketamine pharmacology. At anesthetic doses, that blockade produces sedation. At the much lower sub-anesthetic doses used in mental health care, it produces something stranger and more interesting.
The widely discussed explanation among researchers runs like this:
- Receptor blockade — Ketamine preferentially blocks NMDA receptors on inhibitory interneurons, the cells whose job is to keep excitatory signaling quiet.
- Glutamate release — With the brakes eased, glutamate signaling increases in cortical regions.
- AMPA activation — That glutamate acts on a different receptor type, AMPA, which researchers associate with downstream growth signaling.
- Growth signaling — Pathways including mTOR and the protein BDNF (brain-derived neurotrophic factor) are activated.
- Synaptic change — Laboratory research has described new dendritic spines — the physical contact points between neurons — forming in prefrontal regions after sub-anesthetic exposure.
Neuroplasticity refers to the brain's ability to reorganize its connections in response to experience. It is the reason a skill gets easier with practice, and it is the property that KAP programs are trying to put to work.
Two cautions matter here. First, much of the synaptic evidence comes from animal research, and translating it to human experience is still an active area of study. Second, a mechanism is not an outcome — understanding the pathway does not tell you how any individual will respond. Depression itself is a complex condition with varied presentations, as the National Institute of Mental Health outlines in its overview of depression, and no single mechanism explains every case.
If you want the deeper neuroscience without the therapy framing, our companion piece on how ketamine works on the brain goes further into the synaptic research.
Key takeaway: Ketamine's mental-health effects are tied to NMDA blockade and downstream synaptic signaling — a biological opening, not a finished result.
Why Does the Therapy Part Matter at All?
Because plasticity has no opinion about what gets learned. A brain that is temporarily more open to forming new connections can just as easily re-encode the same rumination loop it has been running for years. The therapy exists to influence what fills the space.
Researchers studying psychedelics and related compounds have proposed that these medicines may reopen "critical periods" — developmental windows when the brain learns from experience unusually readily. Under that framework, the medicine is a context, and the experience inside that context does the teaching. This is a hypothesis under active investigation, not settled science, and clinicians should present it that way.
Integration is the structured therapeutic work of translating what surfaced during a dosing session into language, meaning, and concrete behavior change. Without it, a dosing session is an experience. With it, it becomes material.
There are three practical reasons programs build therapy around dosing:
- Direction — Preparation establishes an intention, so the session has a focus rather than drifting.
- Containment — Dissociative experiences can surface difficult memories. A trained clinician helps process rather than suppress them.
- Transfer — Insight fades fast unless it's attached to a specific action: a boundary set, a conversation had, an avoidance behavior tested.

⚠️ Important distinction: Neuroplasticity is directionally neutral. Being in a more malleable state in a stressful, unsupported environment is not the same as being in one with a trained clinician and a plan. Setting is part of the protocol, not a nicety.
Clinics offering ketamine therapy in Boise vary widely in how much therapeutic structure they wrap around the medicine. That variation is one of the most important things to compare, and it rarely shows up in advertising.
How Is a KAP Course Structured, Start to Finish?
A KAP course is a multi-week sequence, not a single appointment. Most programs organize it into five stages: intake and screening, preparation, a dosing series, integration, and a maintenance decision point. The dosing series is commonly delivered as a cluster of sessions spread across two to four weeks, with therapy contacts woven between them.
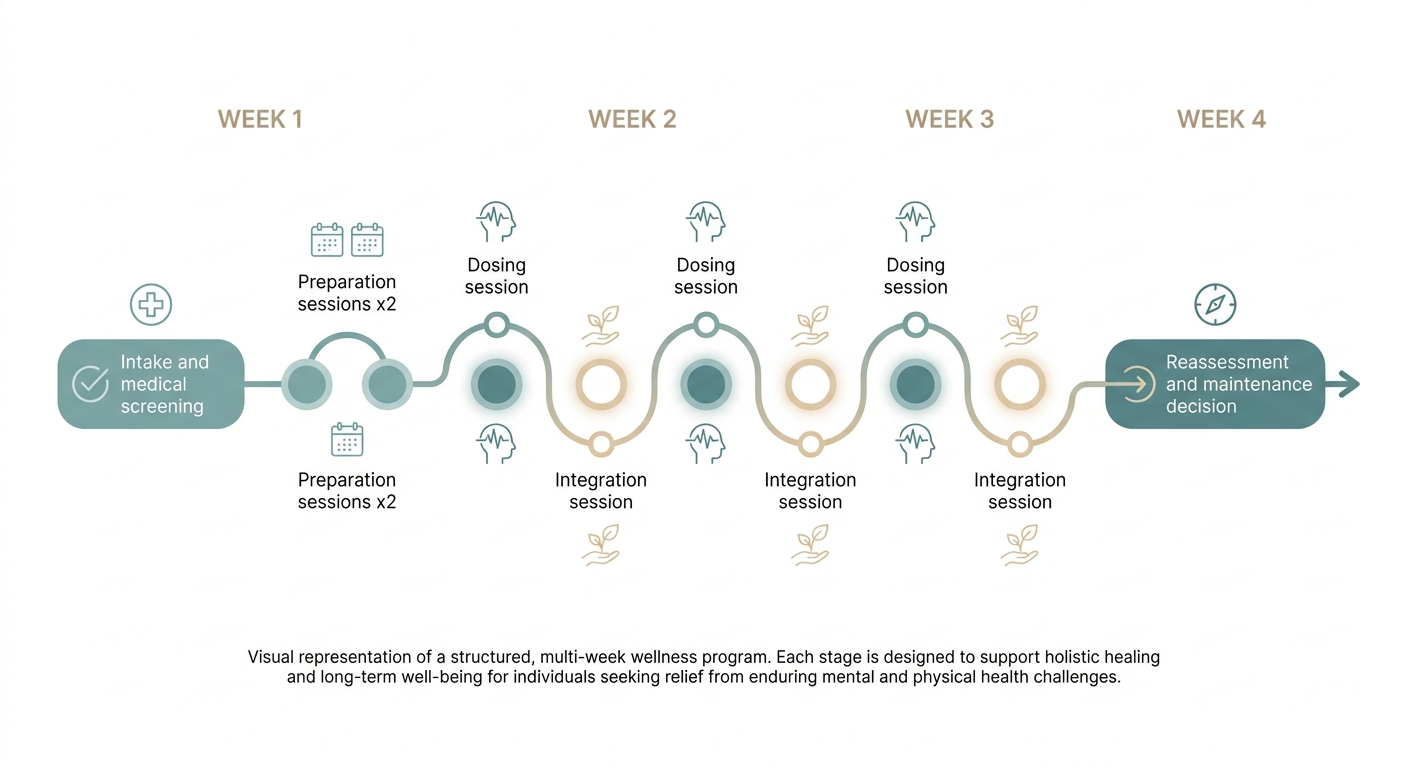
Here is what each stage covers:
| Stage | Typical focus | Who leads it |
|---|---|---|
| Intake and screening | Diagnosis, medication review, cardiovascular and psychiatric history | Prescribing clinician |
| Preparation | Intention setting, expectation calibration, logistics | Therapist or clinician |
| Dosing series | Supervised administration with monitoring | Medical team, therapist present in full KAP |
| Integration | Meaning-making, behavior planning | Therapist |
| Reassessment | Symptom tracking, maintenance planning | Prescribing clinician |
What varies most between programs is the ratio of therapy hours to dosing hours. Some clinics provide a therapist in the room for the entire dosing session. Others offer dosing with medical monitoring only, then separate integration appointments. Neither is automatically wrong — but the price, the schedule, and the experience differ substantially.
If you'd like a closer look at the hour-by-hour texture of a single appointment rather than the course arc, our guide to what a ketamine-assisted psychotherapy session involves covers that ground in detail.
What Does the Preparation Phase Actually Do?
Preparation screens risk and builds the working relationship that the rest of the course depends on. It's the least dramatic phase and arguably the most load-bearing.
A thorough preparation phase typically covers:
- Intention — One or two specific questions or themes to bring into the session, rather than a vague hope.
- Expectation calibration — What dissociation may feel like, so it isn't alarming in the moment.
- Medication review — Clinicians review your full list; some medications, including benzodiazepines and certain mood stabilizers, are discussed because of potential interaction with ketamine's effects.
- Medical clearance — Blood pressure, cardiac history, and relevant conditions are assessed.
- Logistics — Arranging a driver, clearing the rest of your day, food and hydration guidance.
Our walkthrough on preparing for your first ketamine session expands this checklist into a practical day-before plan.
What Happens in Integration Sessions?
Integration sessions convert the raw material of a dosing session into something usable. They are ordinary talk therapy in format — typically a standard 50-minute appointment — but their timing is deliberate.
Many programs schedule integration within one to three days of dosing, because researchers have proposed that the period of heightened synaptic flexibility is relatively brief. A common integration session includes:
- Reviewing notes or journaling captured right after dosing
- Naming themes without forcing interpretation
- Connecting insight to values: what would acting on this look like?
- Designing one small behavioral experiment before the next dose
Working with a dedicated ketamine integration therapist in Boise means someone is tracking the throughline across the whole series, not just the last appointment.
KAP vs Infusion-Only Ketamine: What's the Real Difference?
Infusion-only care delivers the pharmacology under medical supervision. KAP delivers the same pharmacology plus a structured psychological framework around it. The difference shows up in staffing, duration, and cost.
| Factor | Infusion-only ketamine | Ketamine-assisted psychotherapy |
|---|---|---|
| Therapist present during dosing | Not typically | Usually, for part or all of the session |
| Total appointment length | Shorter — dosing plus recovery monitoring | Longer — preparation, dosing, and debrief in one block |
| Separate integration sessions | Optional, often arranged elsewhere | Built into the course |
| Cost per session | Generally lower | Generally higher, reflecting therapist hours |
| Billing | Typically self-pay for the infusion | Psychotherapy hours may be billable separately |
| Best fit | People already in stable therapy elsewhere | People who want medicine and therapy coordinated |
Evidence specifically comparing KAP to infusion-only care is still developing. Published work has explored pairing ketamine with structured psychotherapy, and interest in the combination continues to grow — but the research base is younger and smaller than the base supporting ketamine administration itself. Any clinic claiming settled superiority for one model is overstating what's currently known.
A practical middle path exists too. Some people receive IV ketamine therapy in Boise and Eagle while continuing with an outside therapist who understands the work. That can function well if the two providers actually communicate about timing — and poorly if they don't.
Key takeaway: The core question isn't "which model is better," it's "how much therapeutic structure do I have around dosing, and who is providing it?"
Does KAP Work With Spravato, or Only IV Ketamine?
Both routes can be paired with therapy, and each creates a different container. SPRAVATO (esketamine) nasal spray comes with built-in monitoring time, while IV allows the clinician finer control over dose and pace.
Esketamine is the S-enantiomer of ketamine, formulated as a nasal spray and FDA-approved for treatment-resistant depression in adults in conjunction with an oral antidepressant. Per the FDA prescribing information for SPRAVATO, it is available only through a restricted program under a Risk Evaluation and Mitigation Strategy (REMS), must be administered under the direct observation of a healthcare provider, and patients must be monitored for at least two hours afterward. That mandated two-hour window is, in practice, a ready-made space for therapeutic contact.
| Route | Administration setting | Therapy-pairing notes |
|---|---|---|
| IV infusion | Clinic, with monitoring | Dose and rate adjustable; session length set by protocol |
| Intramuscular | Clinic, with monitoring | Single injection; no rate adjustment after administration |
| Sublingual / oral | Varies by program | Lower-intensity format some programs use between dosing clusters |
| Esketamine nasal spray | Clinic only, under REMS, with at least two hours of monitoring per the FDA label | Monitoring period provides a structured post-dose window |

Cost and coverage differ meaningfully between routes, and so do the eligibility rules. Our side-by-side breakdown of Spravato vs IV ketamine covers insurance criteria, scheduling, and what each route requires of you. For many people searching for esketamine in Boise, insurance coverage is the deciding factor — not mechanism.
⚠️ The FDA label lists contraindications for SPRAVATO including aneurysmal vascular disease, arteriovenous malformation, and a history of intracerebral hemorrhage. Candidacy for any route is determined by a prescribing clinician, not by a website.
Who Is a Good Candidate for Ketamine-Assisted Psychotherapy?
Candidacy is decided in a clinical consultation, but programs generally look at diagnosis, prior treatment history, medical stability, and whether you can meaningfully engage in talk therapy.
Commonly considered, pending evaluation:
- Treatment-resistant depression — usually defined as inadequate response to at least two adequate antidepressant trials. Our guide to treatment-resistant depression help in Idaho explains how "adequate trial" is actually measured.
- PTSD — often a reason people seek ketamine for PTSD in Boise, evaluated case by case.
- Anxiety disorders and OCD — considered off-label; discussed with a clinician regarding evidence and expectations.
- Certain chronic pain conditions — assessed separately from mood indications.
Factors that commonly require caution or exclude someone:
- Uncontrolled hypertension or significant cardiovascular disease
- Active psychosis or a history of psychotic disorder
- Current substance use disorder involving dissociatives or alcohol
- Pregnancy or breastfeeding
- Certain hepatic or intracranial conditions flagged during screening
Ketamine's known adverse effects — including dissociation, elevated blood pressure, nausea, and dizziness — are documented in the clinical ketamine monograph and are part of why monitoring is standard.
⚠️ Screening caution: A personal or family history of bipolar disorder or psychosis changes the risk calculation. Be fully transparent at intake even if a past diagnosis felt wrong to you — the clinician needs the whole picture to screen properly.
Key takeaway: The strongest candidates are medically stable, honestly screened, and able to show up for the therapy half — not just the dosing half.
How Long Do the Effects of KAP Last?
Duration varies between individuals, and honest clinics say so plainly rather than quoting a number. What's consistent is the structure used to track it: a defined induction series, formal reassessment, and a maintenance decision made with your clinician based on your symptom measures over time.
Here's what reassessment typically involves:
- Standardized symptom scales completed before the series, during it, and after
- Functional check-ins on sleep, routine, and engagement with therapy goals
- A maintenance conversation about whether, when, and how often booster dosing is appropriate
- A non-response plan — what the next option is if the series doesn't produce the change you hoped for
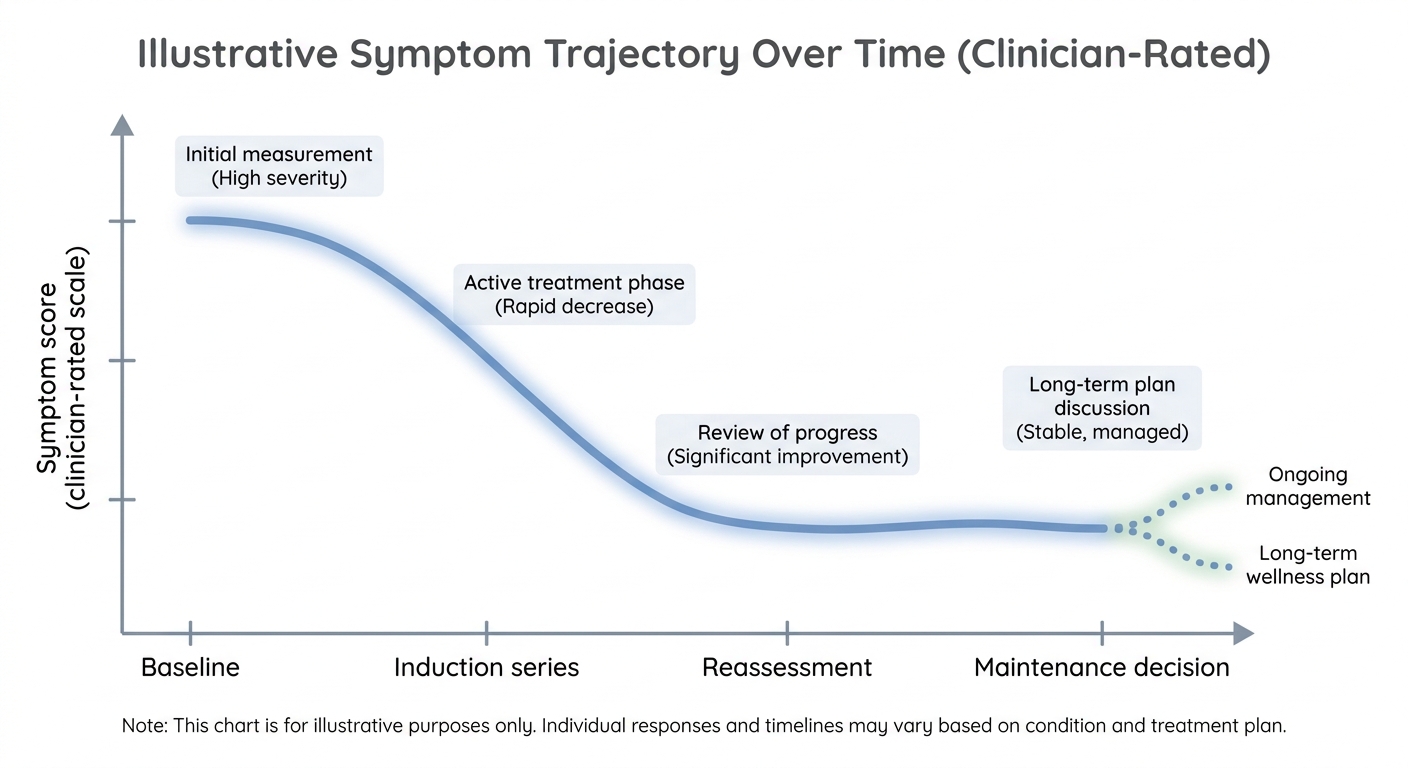
Published trials of ketamine in treatment-resistant depression report that some participants respond while others do not, and that symptoms may return over time without a maintenance plan. Because reported figures vary by trial design, dose, and population, we don't quote a single success rate here — ask your clinician what the evidence shows for your specific diagnosis and route.
Individual results vary, and no clinic can promise a particular outcome or duration. What a good program can promise is measurement: you should know, in numbers, whether anything changed.
What Should You Ask a Clinic Before Starting KAP?
Ask who is physically in the room during dosing, whether integration is included or billed separately, and what the total course costs in writing. Those three answers separate a structured program from a dosing counter.

Eight questions worth asking on the phone:
- Who is present during dosing — a therapist, a nurse, a physician, or a combination?
- Is integration included in the quoted price, or billed as separate psychotherapy?
- What is the total cost of a full induction course, not just one session?
- Which routes do you offer — IV, intramuscular, sublingual, esketamine nasal spray?
- How do you measure response — which scales, and how often?
- What happens if I don't respond to the series?
- Who manages my other medications during the course, and do you coordinate with my prescriber?
- What is your emergency and after-hours protocol?
Pricing in the Treasure Valley varies by route, session length, and whether therapy hours are bundled, so ask for a written estimate rather than relying on a range you read online. Our breakdown of how to choose a ketamine clinic in Boise expands these questions into a full vetting checklist.
Frequently Asked Questions
Is ketamine-assisted psychotherapy the same as psychedelic therapy?
They're related but distinct. Ketamine is a dissociative anesthetic acting mainly at NMDA receptors, not a classic serotonergic psychedelic like psilocybin. The therapeutic framework borrows from psychedelic-assisted models — preparation, dosing, integration — but the pharmacology differs, and ketamine is legally available now under medical supervision.
How many KAP sessions do most people need?
Most programs use a clustered induction series spread over several weeks, paired with preparation sessions beforehand and an integration session after each dose. The exact count is set by your clinician based on diagnosis, route, and how you're tracking on symptom measures. Maintenance is decided at reassessment, not scheduled in advance.
Does insurance cover ketamine-assisted psychotherapy?
Coverage is split. IV ketamine for mental health indications is generally handled as self-pay, while the psychotherapy hours around it are often billable through standard mental health benefits. SPRAVATO is FDA-approved for treatment-resistant depression and is more frequently covered when plan criteria are met. Idaho plans vary — verify your specific benefits before starting.
Can you do KAP if you're already taking an antidepressant?
Usually yes. Many people continue SSRIs or SNRIs throughout a course, and the FDA label for SPRAVATO specifies use in conjunction with an oral antidepressant. Benzodiazepines and certain mood stabilizers are reviewed carefully at intake because of possible interaction with ketamine's effects. Never stop a prescribed medication without talking to the prescriber.
What does a KAP dosing session feel like?
People commonly describe altered time perception, a floating sensation, and a sense of distance from their usual thought patterns. Dissociation is an expected, monitored effect rather than a complication. Experiences vary considerably between individuals and between sessions — our IV ketamine therapy overview covers the session format in more detail.
Summary: How Does Ketamine Assisted Psychotherapy Work?
How does ketamine assisted psychotherapy work comes down to a sequence: a sub-anesthetic dose blocks NMDA receptors, downstream signaling is thought to increase synaptic flexibility, and structured ketamine psychotherapy aims to give that flexibility a direction. The medicine is the opening. Preparation, dosing, and integration are what determine whether anything durable gets built inside it.
If you're weighing ketamine treatment options in Boise or Eagle, judge programs on structure rather than promises — who's in the room, how response is measured, and what the whole course costs. That's the difference between a clinic selling an appointment and one running a protocol.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.