Ketamine for CRPS in Kuna: Who Responds and Why
Zora Neuro Spa Editorial · September 26, 2026

Complex regional pain syndrome is one of the few conditions where patients are often told, honestly, that standard pain treatment may not be enough. That is why so many people in Kuna and the wider Treasure Valley start researching infusions — and why questions about candidacy and ketamine infusion side effects come up before questions about cost. This guide covers who tends to be screened as a good candidate, what published research does and does not show, and the trade-offs worth weighing before you book.
Quick Answer
Ketamine infusions are considered for a subset of CRPS patients — generally those with a diagnosis confirmed by clinical criteria, a clear neuropathic pain pattern, and no untreated psychosis, uncontrolled high blood pressure, or active substance misuse. Relief reported in published studies is partial and time-limited for most people, not curative. Candidacy is decided in a medical consultation, not from a website, and results vary between individuals.
TL;DR
- The best candidates have CRPS confirmed by clinical criteria, stable blood pressure, and no untreated psychiatric or substance-use issues. See the full candidacy checklist
- CRPS pain protocols use more cumulative ketamine than depression protocols, which changes the monitoring plan. Compare outpatient and inpatient protocols
- Published research describes relief measured in weeks to months, not a cure. Read what response data actually shows
- Dissociation, nausea, blood pressure changes, headache and fatigue are the effects patients notice most. Review the side effects that matter for pain patients
- Ketamine sits alongside physical therapy, not instead of it. See how it compares to other CRPS options
In This Article
- What Is CRPS and Why Does It Respond Differently Than Other Pain?
- Who Is a Good Candidate for Ketamine Infusion Therapy?
- How Do Outpatient and Inpatient Ketamine Protocols Compare?
- What Do Response Rates Actually Look Like?
- Which Ketamine Infusion Side Effects Matter Most for CRPS Patients?
- How Does Ketamine Compare to Other CRPS Treatments?
- What Should Kuna and Treasure Valley Patients Ask Before Booking?
What Is CRPS and Why Does It Respond Differently Than Other Pain?
Complex regional pain syndrome (CRPS) is a chronic pain condition in which the nervous system keeps amplifying pain signals in a limb long after the original injury has healed. The pain is out of proportion to the injury, and it usually comes with swelling, temperature and color changes, sweating differences, and skin that hurts to touch.
Two forms are recognized:
- CRPS Type I refers to cases that follow an injury with no confirmed nerve damage.
- CRPS Type II refers to cases that follow a documented nerve injury.
The reason ordinary pain treatment often underperforms here is central sensitization — the spinal cord and brain become tuned to treat mild input as severe pain. NMDA receptors, a type of glutamate receptor involved in pain signaling, are a central part of that process. Ketamine is an NMDA receptor antagonist, which is why it entered pain medicine in the first place (StatPearls, NCBI Bookshelf). UCSF's Pain Management Education page states that ketamine has been shown to prevent and reverse central sensitization and to enhance the body's descending inhibitory pain pathways.
That mechanism is the whole argument for infusions — it targets the amplification itself rather than only dampening the signal downstream. We cover the biology in more depth in our explainer on why CRPS resists traditional treatment.
⚠️ CRPS is a clinical diagnosis, not an imaging one. There is no scan or blood test that confirms it. Clinicians use a standardized symptom-and-sign framework known as the Budapest Criteria, which means an accurate diagnosis depends on a careful in-person exam and history.
Who Is a Good Candidate for Ketamine Infusion Therapy?
The strongest candidates have CRPS confirmed against standard clinical criteria, a clearly neuropathic pain pattern, medically stable blood pressure and heart function, and no active psychosis or history of ketamine misuse. Screening is a conversation plus objective measurements — not a checkbox form.
Which factors are green lights?
- Confirmed CRPS diagnosis from a physician using the Budapest Criteria
- Burning, electric, or allodynic pain (pain from light touch) rather than purely mechanical pain
- Prior trials of first-line care, including physical or mirror therapy and neuropathic medications
- Stable cardiovascular status, since ketamine can raise blood pressure and heart rate (StatPearls)
- A reliable ride home and a support person for infusion days
Which factors need a closer look?
- Long symptom duration — longer-standing cases are often discussed with more conservative expectations
- High-dose opioid or benzodiazepine use, which affects sedation planning
- Prior bladder or urinary symptoms, which are reviewed before repeat dosing
- Liver disease or abnormal liver enzymes, which may change the protocol
- Untreated sleep apnea or other airway concerns
Which factors are usually disqualifying?
- Active, untreated psychosis
- Uncontrolled hypertension or unstable cardiac disease
- Active ketamine or stimulant misuse
- Pregnancy
- Severe, untreated liver disease
A thorough workup before your first infusion typically includes a baseline blood pressure and heart-rate check, a review of liver function labs, a bladder and urinary symptom review, a full psychiatric history, and a complete medication reconciliation. If you want that evaluation done properly, a CRPS treatment consultation in Eagle is where it starts — Kuna is roughly a 25-minute drive.
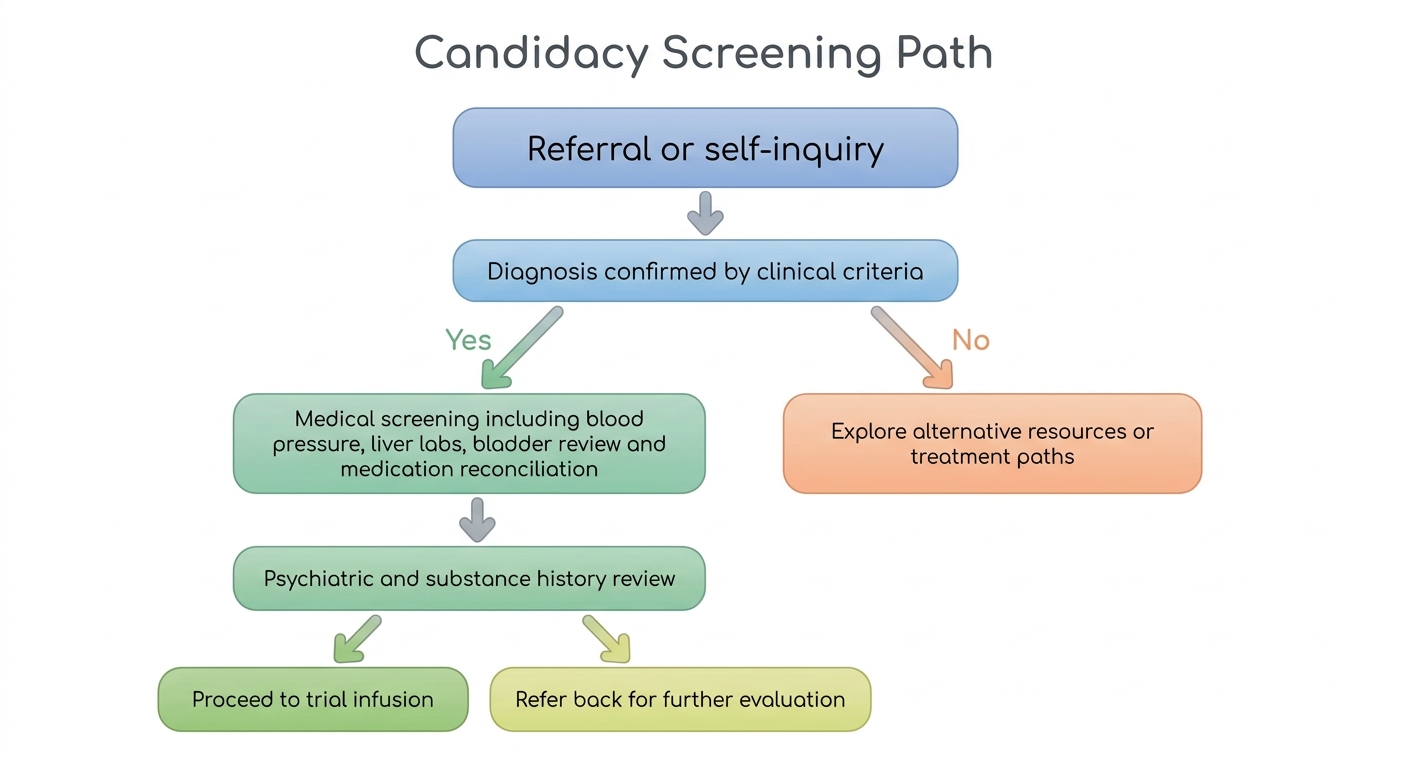
Key takeaway: Candidacy for ketamine for CRPS treatment rests on three things — a confirmed diagnosis, a neuropathic pain pattern, and medical stability for repeated dosing.
How Do Outpatient and Inpatient Ketamine Protocols Compare?
Two very different approaches exist under the same drug name, and confusing them is the most common source of unrealistic expectations. Outpatient sub-anesthetic infusions are the standard approach in US clinics. High-dose anesthetic protocols — sometimes described as "ketamine coma" — are used in a small number of overseas inpatient settings and are not part of routine US outpatient practice.
| Factor | Outpatient sub-anesthetic infusion | High-dose anesthetic inpatient protocol |
|---|---|---|
| Dose level | Well below anesthetic doses | Anesthetic-range dosing |
| Setting | Clinic recliner, awake and responsive | Hospital or ICU with airway management |
| Session length | Typically under a few hours | Multi-day continuous administration |
| Monitoring | Blood pressure, heart rate, oxygen saturation, clinician present | Full critical-care monitoring |
| Risk profile | Lower, but requires medical supervision | Substantially higher |
| Availability near Kuna | Available at Treasure Valley clinics | Not offered in routine US practice |
A Cleveland Clinic ConsultQD article published in November 2025 describes a low-dose outpatient protocol for chronic refractory pain of 0.5 mg/kg infused over 40 minutes. Protocols vary between clinics, and the dose, infusion rate, and number of sessions should be explained to you in writing before you consent.
CRPS protocols generally differ from mood-disorder protocols in two ways: infusions often run longer, and the series is often scheduled over consecutive or near-consecutive days. That means more total ketamine over a shorter window, which is exactly why screening and monitoring matter more here. Our breakdown of ketamine infusion protocols for CRPS covers the dosing mechanics in detail.
⚠️ Be cautious with any clinic that markets an anesthetic-level protocol as a routine outpatient service. Deep sedation requires airway management and critical-care monitoring — not a recliner and a blanket.
What Do Response Rates Actually Look Like?
Published research on ketamine for chronic neuropathic pain reports that a portion of participants experience reduced pain scores, with relief typically described in weeks to a few months rather than as a permanent change. No published trial demonstrates that ketamine cures CRPS.
The clearest way to hold this in your head:
- Response is partial for most people. Studies generally measure reductions in pain scores, not elimination of pain.
- Duration is limited. Relief described in the literature is measured over a time window, which is why maintenance or booster infusions are part of most plans.
- Variation is wide. Some participants in published studies report little or no change.
- Function matters as much as pain scores. Many clinicians pair infusions with physical therapy so that any window of reduced pain can be used for movement.
A 2014 review of ketamine for chronic pain surveys this body of evidence and discusses both the benefits and the risks of repeated administration. Randomized controlled trials on ketamine for CRPS have been published and are frequently referenced in the clinical literature. Because the evidence base is modest in size and the designs vary, any specific promise about how much better you will feel, or how fast, is not something an honest clinic can make.
It is reasonable to ask your provider directly: what are we measuring, when do we reassess, and what result would tell us this is not working for me? That conversation belongs in your first chronic pain evaluation, before the first infusion.
Key takeaway: Treat ketamine therapy as a possible window of reduced pain to be used for rehabilitation — not as a one-time fix. Individual results vary.
Which Ketamine Infusion Side Effects Matter Most for CRPS Patients?
The effects that matter most during a pain protocol fall into three groups: what happens during the session, what lingers the same day, and what repeated cumulative dosing can affect over time.
During the infusion, the commonly described effects include dissociation (a floating or detached feeling), dizziness, nausea, blurred or double vision, and increases in blood pressure and heart rate (StatPearls). Clinics monitor vitals throughout and can slow or pause the infusion.
For the rest of the day, patients commonly report headache, fatigue, grogginess, and unsteadiness. That is why a ride home is non-negotiable and why driving is off the table until the next day.
With repeated, higher cumulative dosing, the concerns clinicians track are transient liver enzyme elevation and bladder or urinary irritation. This is where CRPS protocols differ from depression protocols — more total drug across a compressed series means liver labs and bladder symptom reviews are checked more deliberately.

⚠️ Therapeutic dosing and recreational misuse are not the same risk picture. The severe bladder and cognitive problems most often cited in the literature come from frequent, high-dose, unsupervised use over long periods — not from monitored, medically dosed infusion series. That distinction matters, and it is one consumer articles frequently blur.
For a fuller walk-through, see our guide to the potential side effects of CRPS infusions. Tell your clinic about every symptom, even minor ones — dose and rate can usually be adjusted.
How Does Ketamine Compare to Other CRPS Treatments?
Ketamine is one option among several, and it usually enters the conversation after first-line care has been tried. The American Society of Regional Anesthesia and Pain Medicine's July 2022 newsletter discusses ketamine infusion therapy as a component of multimodal chronic pain care rather than a standalone treatment.
| Approach | What it involves | Invasiveness | Typical role in care |
|---|---|---|---|
| Physical / mirror therapy | Graded movement, desensitization, mirror visual feedback | None | Foundational; usually continues alongside everything else |
| Gabapentinoids | Daily oral neuropathic pain medication | None | Commonly tried early |
| Bisphosphonates | Medication affecting bone turnover | Low (oral or IV) | Considered in earlier-stage cases |
| Sympathetic nerve blocks | Injected local anesthetic near sympathetic nerves | Moderate, procedural | Diagnostic and therapeutic trial |
| Spinal cord stimulation | Implanted device delivering electrical stimulation | High, surgical | Considered in refractory cases |
| Ketamine infusions | Supervised IV sub-anesthetic dosing series | Moderate, IV-based | Off-label option for refractory neuropathic pain |
The practical point: these are not competitors. Most pain physicians build a stacked plan, and infusions are often timed so that any reduction in pain can be used to push physical therapy further than before. If you are weighing where infusions fit in your own plan, a chronic pain treatment consultation is the right place to map it out with your existing specialist in the loop.
What Should Kuna and Treasure Valley Patients Ask Before Booking?
Ask about supervision, monitoring, protocol details, total sessions, aftercare, and coordination with your existing pain physician. Kuna sits roughly 25 minutes from Eagle, so infusion-day logistics — driver, timing, work schedule — are worth planning before you commit.
Copy these into your phone:
- Who administers the infusion, and are they physically present the entire time?
- What monitoring equipment is used, and what vitals are recorded?
- What dose, rate, and infusion length does your CRPS protocol use?
- How many sessions are planned before we reassess?
- What labs or screenings do you require before the first infusion?
- What are your rules for driving, eating, and having a support person?
- How do you handle side effects during and after a session?
- Will you communicate with my pain specialist or primary care provider?
Ketamine for pain is used off-label in the US, which in practice means most Idaho patients should expect the infusion itself to be self-pay. Ask for itemized billing codes so you can submit them yourself. You can review how our own IV ketamine therapy in Boise and Eagle is structured before your consultation.
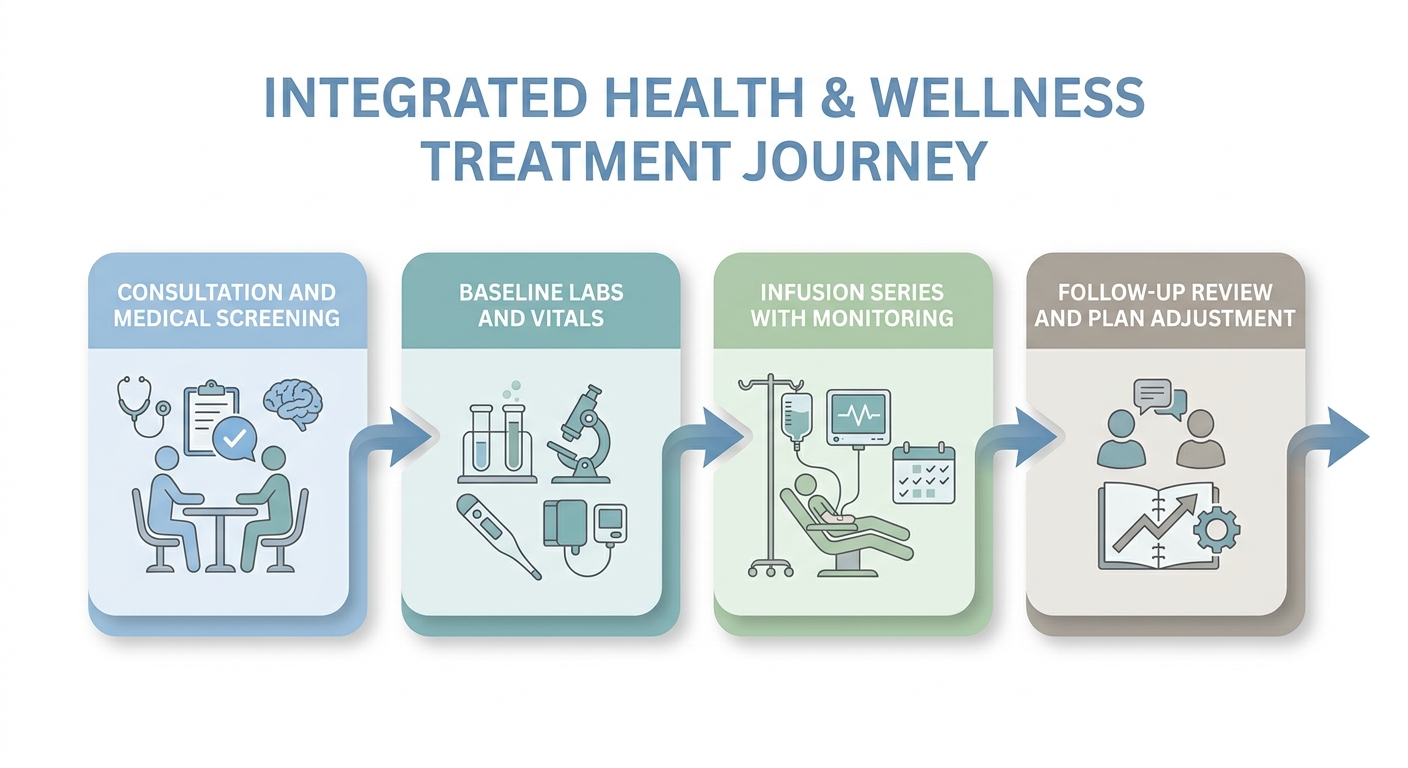
Key takeaway: A clinic that answers all eight questions clearly and in writing is showing you its safety culture. Vague answers are the signal to keep looking.
Frequently Asked Questions
How many ketamine infusions are typically needed for CRPS?
Pain protocols generally involve a series scheduled over consecutive or near-consecutive days, which is a different shape than the spread-out series often used for mood conditions. The exact number is set by your clinician based on your diagnosis, medications, and how you tolerate the first sessions. Many plans also include booster infusions scheduled when symptoms return rather than on a fixed calendar.
Does insurance cover ketamine for CRPS in Idaho?
IV ketamine for pain is off-label, so most Idaho plans do not cover the infusion itself. Some plans do cover the consultation or related office visits, so it is worth asking your insurer specifically about evaluation codes. Request itemized documentation from the clinic so you can submit a claim yourself. Our ketamine therapy cost and process FAQ explains what to expect financially.
Can ketamine cure CRPS?
No published evidence supports a cure. Research describes relief that is partial and time-limited for most participants, with wide variation between individuals. That is precisely why maintenance planning and ongoing physical therapy are built into most treatment plans rather than treated as optional add-ons.
Is ketamine safe if I already take gabapentin or opioids?
Usually it can be managed, but only after a full medication reconciliation with a physician. Sedating medications can stack, and blood pressure effects need to be anticipated in advance. Benzodiazepines are also discussed carefully, since some clinicians believe they may blunt the response. Bring a complete list of everything you take, including supplements, to your consultation.
What Happens Next
The people most likely to be cleared for infusions are those with a confirmed CRPS diagnosis, a burning or touch-sensitive neuropathic pain pattern, stable cardiovascular health, and a willingness to pair treatment with physical therapy. The honest framing is that ketamine therapy may open a window of reduced pain for some patients — a window best used for movement and rehabilitation — and that the ketamine infusion side effects worth weighing are real, mostly short-lived, and manageable under proper monitoring. Results vary between individuals, and candidacy is always decided in a clinical consultation. If Kuna is home and you are ready for a straight answer about whether this fits your case, a consultation is the next step.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.