Ketamine Infusion Protocols for CRPS, Explained
Zora Neuro Spa Editorial · September 20, 2026

If you have researched ketamine for CRPS, you have probably found two kinds of pages: thin local ads with a phone number, and dense research papers. Neither tells you what a protocol actually involves — the dosing logic, how many sessions a series runs, or which ketamine infusion side effects show up at pain-level doses rather than mood-level doses. This guide fills that gap for patients across Boise, Eagle, Caldwell, and the wider Treasure Valley.
Quick Answer
CRPS protocols use longer infusions and more total drug than the depression protocol most people read about first. For depression, a widely described sub-anesthetic schedule is 0.5 mg/kg given over roughly 40 minutes, according to the StatPearls clinical monograph on ketamine. Pain-focused protocols generally stretch the infusion over several hours and repeat it across a short block of sessions, often followed by periodic booster visits. Side effects at these doses are largely dose-related and are monitored in the chair until they settle.
TL;DR
- Pain protocols are not mood protocols. CRPS series use longer sessions and higher cumulative exposure than the standard depression infusion. See why central sensitization changes the dosing math
- There are three recognizable tiers of protocol, and only some of them are offered in routine US outpatient clinics. Compare the protocol tiers side by side
- Most plans have a loading phase and a maintenance phase. Skipping the booster plan is the most common reason people feel like the series "stopped working." See how loading and booster cadence is structured
- Common effects are dissociation, nausea, drowsiness, and a temporary rise in blood pressure and heart rate, all managed during the drip. Read the side effect and management table
- The rare risks worth real attention — bladder irritation and liver enzyme changes — are documented mainly with frequent, long-term, high-dose exposure. See the monitoring practices that address them
In This Article
Here is the path we will walk, in plain order, from biology to the questions you should ask before booking:
- Why Does CRPS Need a Different Ketamine Protocol Than Depression?
- What Does a CRPS Ketamine Protocol Actually Look Like?
- How Many Infusions and Boosters Will You Realistically Need?
- What Side Effects Should You Expect During a CRPS Infusion?
- Which Rare Risks Actually Matter at Pain-Protocol Doses?
- How Effective Is Ketamine for CRPS, and Who Responds Best?
- What Should You Ask a Clinic Before Starting a CRPS Series?
Why Does CRPS Need a Different Ketamine Protocol Than Depression?
Because CRPS pain is generated and maintained by the nervous system itself, not by ongoing tissue damage. That changes how much drug exposure clinicians plan for.
Central sensitization is the nervous system's amplification of pain signals after the original injury has healed. Nerve cells in the spinal cord become easier to fire and slower to quiet down. Light touch, a sock, or a breeze can register as searing pain — a phenomenon called allodynia.
Ketamine is an NMDA-receptor antagonist, meaning it blocks a receptor involved in how pain signals are amplified and stored, as described in the StatPearls monograph. That mechanism is the reason the same molecule shows up in two very different conversations: mood and pain.
Why doesn't a standard depression infusion work the same way here?
The depression protocol was built around mood outcomes. The National Institute of Mental Health describes depression as a condition with multiple treatment pathways, and the sub-anesthetic infusion used in that setting is short — commonly 0.5 mg/kg over about 40 minutes, per StatPearls.
Pain clinicians generally plan for more drug-time, not just more drug. The working idea is that a sensitized spinal cord needs a longer window of receptor blockade to settle. This is also part of why CRPS resists traditional treatment — anti-inflammatories and opioids act on pathways that are not the main driver.
Two practical consequences follow. Sessions run longer, so plan your day around them. And because dose and duration go up, the intensity of the in-chair experience usually goes up too.
Key takeaway: CRPS protocols are longer and heavier than mood protocols because the target is a sensitized nervous system, not a mood state.
What Does a CRPS Ketamine Protocol Actually Look Like?
There are three recognizable tiers, and they differ enormously in setting, supervision, and availability. Knowing which tier a clinic offers is the single most useful question you can ask.
| Protocol tier | How it is dosed | Session length | Series shape | Setting |
|---|---|---|---|---|
| Sub-anesthetic mood protocol (shown for contrast) | 0.5 mg/kg over ~40 min (StatPearls) | Under an hour | Short block of sessions | Outpatient clinic |
| Outpatient CRPS series | Weight-based sub-anesthetic dosing, often titrated upward across sessions | Typically several hours | Loading block over about two to three weeks | Outpatient clinic with continuous monitoring |
| Extended multi-hour outpatient infusion | Higher cumulative exposure per visit | Half-day visits | Repeated on consecutive or near-consecutive days | Outpatient with extended recovery capacity |
| Inpatient anesthetic-dose protocol | Anesthetic dosing with airway and ventilatory support | Continuous, over days | One-off intensive admission | Hospital or ICU; not routine US outpatient care |
Most people researching a CRPS treatment consultation in Eagle are choosing between tier two and tier three. The anesthetic-dose tier is not something a Boise or Caldwell outpatient clinic provides, and any page implying otherwise deserves scrutiny.
Sub-anesthetic dosing refers to drug amounts below the level used for surgical anesthesia — you stay awake, breathing on your own, and able to respond.
What varies between clinics, and what should not?
Dose ceilings, titration steps, and infusion length vary legitimately between programs. What should not vary is whether those details are written down for you.
- Written mg/kg range — your starting dose and the maximum your prescriber will go to.
- Infusion duration — a two-hour session and a four-hour session are different treatments.
- Titration rule — what triggers an increase, and what triggers holding steady.
- Monitoring plan — vitals cadence, pulse oximetry, and who is in the room.
- Stop criteria — what would cause the team to slow or end an infusion early.
Ask for these in writing before you pay a deposit. A clinic running a real pain protocol will have them ready; a page built mainly for local ketamine clinic Boise search traffic often will not.
Key takeaway: Protocol tier, written dosing range, and infusion length are the three details that separate a genuine CRPS program from a general ketamine therapy Boise offering.
How Many Infusions and Boosters Will You Realistically Need?
Plan for a block, not a single visit. Outpatient CRPS care is generally structured in two phases, and the second phase is the one people underestimate.
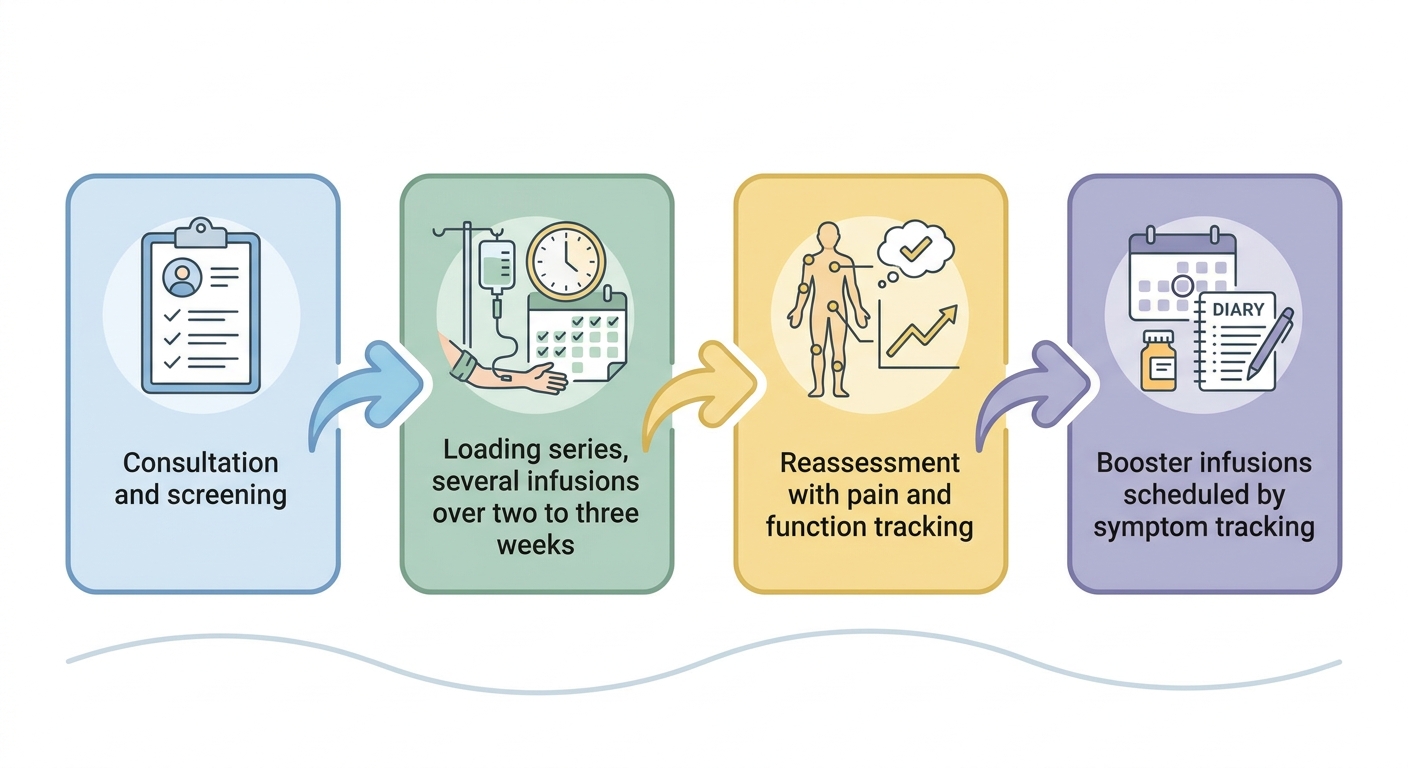
A loading series is the initial concentrated block of infusions given close together to establish a response. A booster infusion is a single maintenance session scheduled later to hold that response. Many clinics build CRPS plans around a loading block of roughly five to ten sessions over two to three weeks, though the exact number is set by your prescriber and your response.
Why does relief sometimes fade between phases?
Because the loading series is designed to start something, not finish it. Clinicians generally treat ketamine as a window rather than a permanent reset, and boosters exist to keep that window from closing unnoticed.
Booster cadence is usually set by tracking, not by a fixed calendar. Practical markers your team may use include:
- Pain scores recorded weekly rather than recalled at the next visit.
- Function measures — sleep, grip, stair tolerance, how long you can stand.
- Allodynia mapping — whether the touch-sensitive area is shrinking or spreading.
- Medication load — whether other pain medications are being adjusted.
Boosters are commonly scheduled anywhere from a few weeks to a few months apart. If a clinic cannot tell you how booster timing is decided, that is a gap worth naming out loud.
It also helps to know the practical rhythm of the visits themselves — what a full IV ketamine series involves covers arrival, monitoring, and recovery time so you can arrange rides and time off in advance. For patients driving in from Caldwell or Nampa, that logistics planning matters as much as the protocol itself.
Key takeaway: Ask about the maintenance plan before the loading series starts — that is where most CRPS treatment plans succeed or quietly drift.
What Side Effects Should You Expect During a CRPS Infusion?
Expect a handful of predictable, temporary effects that peak while the drip is running and ease afterward. The StatPearls monograph lists the recognized adverse effects of ketamine, including emergence phenomena, elevated blood pressure and heart rate, nausea and vomiting, and increased salivation.
Dissociation is a temporary sense of detachment from your body or surroundings. It is expected at therapeutic doses, not a sign something has gone wrong — but at pain-protocol doses it is usually more pronounced than at mood-protocol doses.
| Effect | How it is typically described | When it is most noticeable | How clinics commonly manage it |
|---|---|---|---|
| Dissociation | Very common at therapeutic doses | Mid-infusion, at peak concentration | Slowing the drip rate, quiet room, eye mask, staff reassurance |
| Nausea | Common | Mid-infusion and shortly after | Antiemetic medication on hand, slower titration |
| Blood pressure and heart rate rise | Recognized cardiovascular effect (StatPearls) | Early to mid-infusion | Scheduled vitals checks, pausing or slowing the infusion |
| Blurred or double vision | Common | Peak dose | Waiting it out in the chair; no driving afterward |
| Drowsiness and unsteadiness | Common | During and immediately after | Assisted walking, required ride home |
| Emergence agitation | Less common | As the infusion ends | Calm environment; a benzodiazepine only if the prescriber judges it appropriate |
Which ketamine infusion side effects are dose-dependent?
Most of them. That is precisely why pain protocols feel different from mood protocols.
- Dissociation intensity rises with dose and infusion rate.
- Cardiovascular stimulation tends to track with dose, which is why baseline blood pressure is screened first.
- Nausea is frequently rate-related, so slowing the drip is often the first adjustment.
- Post-session grogginess generally reflects total exposure, so a four-hour session needs a longer recovery buffer than a 40-minute one.
Two things are worth separating: what happens in the chair, and what lingers. For the full timeline, see which ketamine side effects last minutes vs months.
⚠️ Never drive yourself home after an infusion, and do not plan a work call for that afternoon. Arrange a ride before your first session.
Which Rare Risks Actually Matter at Pain-Protocol Doses?
Three deserve genuine attention: urinary and bladder problems, liver enzyme changes, and blood pressure elevation in people with poorly controlled hypertension. The StatPearls monograph associates urinary and hepatobiliary complications primarily with frequent, long-term, high-dose ketamine exposure — the pattern seen in heavy recreational use rather than a supervised clinic series.
That distinction matters, but it does not make monitoring optional. Pain protocols involve more drug than mood protocols, so a responsible program screens accordingly.
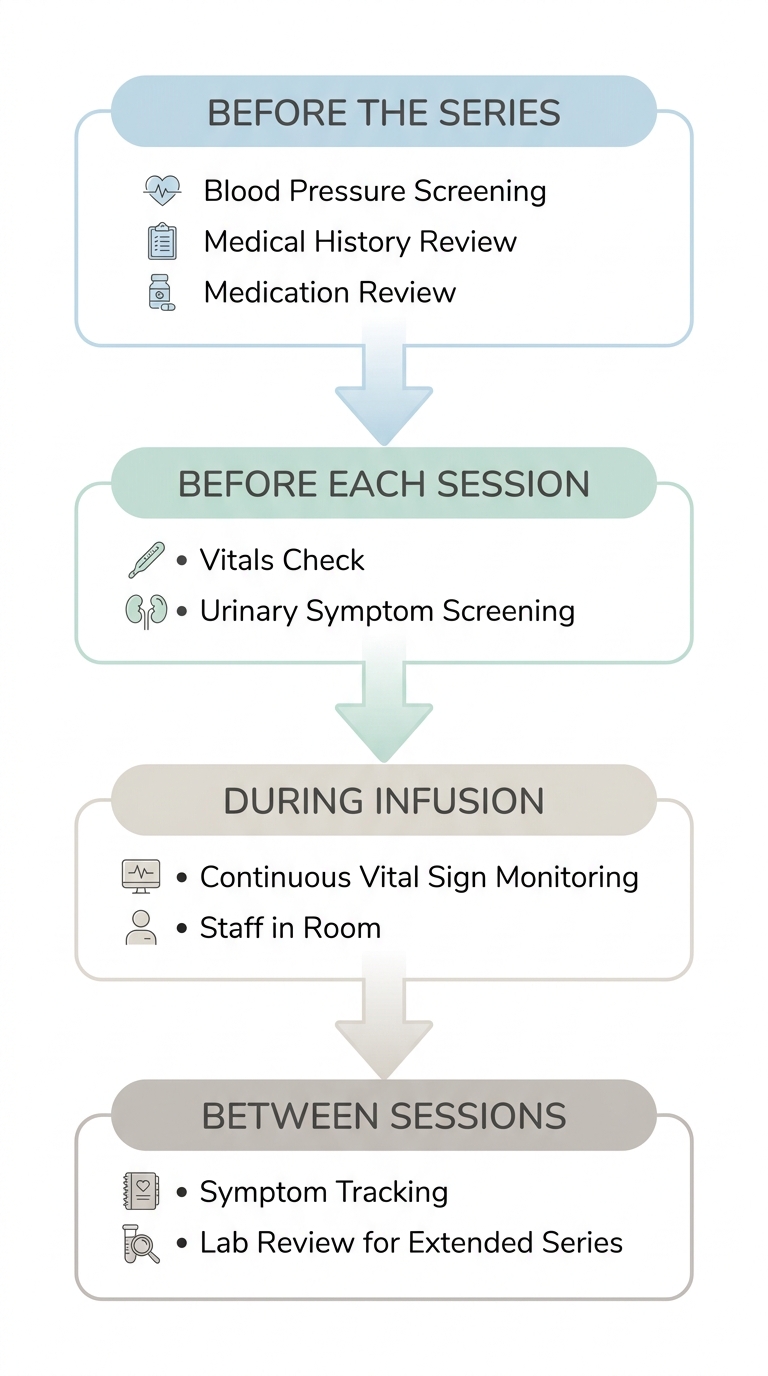
Reasonable monitoring practices to ask about include:
- Baseline blood pressure and a plan for what happens if readings run high on the day.
- Liver function testing before and during an extended or repeated high-dose series.
- Urinary symptom screening at every visit — urgency, frequency, or pain with urination should be reported immediately, not at the end of the block.
- Medication reconciliation, including any sedatives you take at home.
- Continuous monitoring in the room for the length of the infusion.
Regulators take in-clinic observation seriously for related medications. The FDA prescribing information for SPRAVATO (esketamine) requires administration in a certified healthcare setting with post-dose monitoring under a restricted program. IV ketamine for chronic pain is prescribed off-label, so the equivalent safeguards come from clinic policy rather than a federal program — which is exactly why you should ask to see those policies.
⚠️ Tell your prescriber about uncontrolled high blood pressure, liver disease, a history of bladder symptoms, or any substance use history before your first session. These change the plan.
How Effective Is Ketamine for CRPS, and Who Responds Best?
Honest framing first: ketamine is generally discussed as a time-limited option for some people with CRPS, not a cure, and responses vary widely between individuals. Suitability is decided in a clinical consultation, not from an article.
Pain specialists commonly describe better odds earlier in the disease course, before the pain pattern has been entrenched for years. Prominent allodynia — that touch-triggered pain — is another feature clinicians often discuss as relevant when assessing candidacy. Long-duration CRPS with fixed dystonia and joint contracture is generally regarded as harder to influence.

Does ketamine replace the rest of your pain care?
No — it is almost always used alongside other care, not instead of it. Many clinicians view the period after an infusion as a chance to engage in therapies that pain previously made intolerable.
That typically means coordinating with your existing team on:
- Physical therapy and desensitization work, which some patients find easier to tolerate during a treatment block.
- Medication review, since your prescriber may adjust other agents around the series.
- Sleep and mood support, because CRPS and mood symptoms frequently travel together.
- Realistic goal setting, defined in function rather than a single pain number.
If you are still mapping the landscape, our overview of chronic pain treatment options explains where infusion therapy sits among other approaches. Results vary between individuals, and no clinic can promise a specific outcome.
Key takeaway: Ketamine is best evaluated as one component of a multimodal CRPS plan, with candidacy determined during a clinical consultation.
What Should You Ask a Clinic Before Starting a CRPS Series?
Ask about protocol specifics, monitoring equipment, and prescriber credentials — the details thin local landing pages rarely publish. Here is a checklist you can screenshot and bring with you:
- What mg/kg range will I start at, and what is the ceiling? Get it in writing.
- How long is each infusion, door to door? Include recovery time.
- How many sessions are in the loading series, and how are they spaced?
- What is the written booster plan, and what triggers one?
- Who is in the room during my infusion, and are they ACLS-certified?
- What monitoring is used? Ask specifically about continuous pulse oximetry, blood pressure cadence, and whether capnography is available.
- What are your stop criteria? A clinic should be able to say what would end an infusion early.
- What is the total cost of the series, including boosters? Ask what is billed and what is self-pay.
If you want a broader vetting framework beyond CRPS specifically, we also published a 5-step checklist for vetting a ketamine clinic.
Patients across Boise, Eagle, Caldwell, and Meridian frequently tell us the hardest part is not choosing ketamine — it is getting straight answers about protocol design before committing. That conversation should be free, unhurried, and specific to your history.
Frequently Asked Questions
Does insurance cover ketamine infusions for CRPS?
IV ketamine for CRPS is prescribed off-label, and in Idaho it is most often handled as an out-of-network or self-pay service. Some patients submit a superbill and pursue partial reimbursement for the infusion or facility component, with results varying by plan. Ask your clinic exactly which codes appear on your receipt before the first session. Coverage rules change, so verify current details directly with your insurer.
How long after a CRPS infusion does pain relief start?
No clinic can promise a timeline, and individual responses vary considerably. Clinicians generally assess change across the loading series rather than after a single visit, using pain and function tracking between sessions. Ask your prescriber how they measure response and at which session they plan to formally reassess. That reassessment point matters more than any expectation set in advance.
Can ketamine be combined with gabapentin, nerve blocks, or physical therapy?
In most CRPS plans, ketamine is used as an adjunct rather than a replacement for existing care. Many clinicians coordinate infusions with physical therapy and desensitization work so those sessions are more tolerable. Benzodiazepines are worth flagging specifically, as some prescribers review or adjust them around infusion days. Bring a complete medication list — including supplements — to your consultation.
Is at-home oral ketamine an option for CRPS?
Oral and sublingual ketamine pass through the digestive tract and liver before reaching the bloodstream, while an IV dose enters circulation directly. Because of that difference in route, oral formats are generally discussed as a maintenance option between supervised infusions rather than a primary CRPS protocol. If you are weighing formats, see how at-home oral ketamine compares. Any at-home plan should be prescriber-supervised.
Summary
CRPS protocols differ from mood protocols in three concrete ways: longer infusions, a structured loading series, and a booster plan that carries the work forward. The ketamine infusion side effects you are most likely to encounter — dissociation, nausea, drowsiness, and a temporary cardiovascular bump — are dose-related and managed in the chair. The rarer risks are tied mainly to frequent, long-term, high-dose exposure and are addressed through baseline screening and ongoing monitoring.
Use the eight-question checklist above when you call any ketamine clinic in Boise, Eagle, or Caldwell. A program built for pain will answer every item without hesitation. Individual results vary, and whether ketamine for CRPS treatment fits your situation is a decision for a clinical consultation with a qualified prescriber.