Ketamine Infusion Side Effects, Hour by Hour
Zora Neuro Spa Editorial · September 22, 2026

Ketamine Infusion Side Effects, Hour by Hour
If you are scheduled for a first appointment in Boise or Eagle, most of what you have read online about ketamine side effects probably describes recreational misuse — not a slow, monitored IV drip in a clinical chair. Those are different doses, different frequencies, and different levels of supervision. Here is an honest, hour-by-hour look at what happens during a clinical infusion, that same evening, and the next morning.
Quick Answer: What Side Effects Does a Ketamine Infusion Cause?
During a sub-anesthetic IV infusion, most people notice dissociation (a floating, detached feeling), mild dizziness, blurred or drifting vision, and a temporary rise in blood pressure and heart rate. Nausea is among the most commonly reported effects and is often addressed with anti-nausea medication beforehand. Because ketamine has a short duration of action, the acute ketamine side effects generally fade within the hour after the drip ends, per the StatPearls clinical monograph on ketamine.
TL;DR
- In-chair effects and after-effects are two different categories. Dissociation and dizziness belong to the drip itself; tiredness belongs to the evening. See the hour-by-hour infusion timeline
- Nausea is common but largely manageable. Clinics routinely combine a fasting window with pre-dosed anti-nausea medication. Review how clinics reduce side effects
- Blood pressure and heart rate changes are expected and monitored. Vitals are checked repeatedly throughout the session. Read what happens during the infusion itself
- Bladder, memory, and dependence concerns come mainly from frequent high-dose misuse. That literature is not a description of a supervised infusion series. Compare clinical dosing with recreational use
- Some symptoms deserve a phone call, not a wait-and-see. Know the red flags before your first session. Check the red-flag list
In This Article
- Why Are IV Infusion Side Effects Different From Ketamine's Reputation?
- What Happens During the Infusion Itself?
- The Hour-by-Hour Timeline: How Long Do Ketamine Side Effects Last?
- Which Side Effects Are Common, Which Are Rare?
- What About Bladder Problems, Memory, and Dependence?
- How Do Clinics Actually Reduce These Side Effects?
- When Should You Call Your Clinic?
- Frequently Asked Questions
Why Are IV Infusion Side Effects Different From Ketamine's Reputation?
Dose, frequency, route, and supervision change the risk picture completely. General drug fact sheets and harm-reduction pages describe patterns of misuse — larger amounts, taken repeatedly, often by snorting, with no vitals monitoring. A clinical infusion is a measured, slow delivery in a supervised room.
Sub-anesthetic ketamine refers to a dose range well below the levels used to produce surgical anesthesia, delivered slowly by IV. The StatPearls monograph describes ketamine's anesthetic and analgesic uses alongside its adverse effect profile, and the distinction between anesthetic and sub-anesthetic dosing is central to how IV ketamine therapy is delivered for mood and pain conditions.
| Factor | Recreational use | Clinical IV infusion | At-home oral dosing |
|---|---|---|---|
| Amount taken | Unmeasured, often far higher | Weight-based, calculated by a clinician | Prescribed dose, self-administered |
| Frequency | Can be daily or binge-pattern | Scheduled series with spacing between sessions | Varies by prescriber's plan |
| Route | Often snorted or injected | Slow IV over a set session length | Swallowed or dissolved in the mouth |
| Monitoring | None | Continuous observation, repeated vitals checks | Not monitored in person during the dose |
| Main documented concerns | Bladder injury, cognitive effects, misuse with chronic heavy use | Transient dissociation, nausea, blood pressure changes | Dose effects without in-room clinical support |
⚠️ A caution on sourcing: Government and harm-reduction fact sheets are accurate about misuse, but they were never written as guides to supervised care. Reading them as a preview of your infusion will overstate what you are likely to experience.
Patients traveling in from Boise, Eagle, Nampa, and Caldwell often arrive with this exact mismatch in their heads — expecting the misuse profile and finding a quiet recliner, a blanket, and a nurse checking a blood pressure cuff.
Key takeaway: Judge your infusion by clinical dosing data, not by fact sheets written about unmeasured, unmonitored use.
What Happens During the Infusion Itself?
Effects typically begin within the first few minutes of the drip starting and are most noticeable somewhere in the middle of the session. Dissociation is a temporary sense of detachment from your body, surroundings, or sense of time — it is the signature in-chair experience, and for many people it is the part that feels strangest the first time.
A typical infusion room is deliberately low-stimulation: a reclining chair, a folded blanket, headphones and an eye mask within reach, an IV pole beside the chair, and soft daylight through a shaded window.
Commonly reported sensations and effects during the drip include:
- Floating or weightlessness — limbs may feel heavy, distant, or pleasantly disconnected.
- Time distortion — the session can feel much shorter or much longer than the clock says.
- Visual drift — colors, patterns, or movement with eyes closed; blurring with eyes open.
- Nystagmus — involuntary rhythmic eye movement, listed among ketamine's recognized effects in the clinical literature.
- Mild dizziness or a metallic taste — usually brief and settling as the drip tapers.
- A temporary rise in blood pressure and heart rate — expected, which is exactly why vitals are checked at intervals throughout the session.
It helps to separate sensation from side effect. Dissociation is intrinsic to how the medication acts, not a sign something has gone wrong — our deeper guide to what a ketamine infusion feels like walks through the subjective experience in detail. Nausea, headache, or anxiety during the drip are the effects clinicians actively work to reduce.
If the intensity feels like too much, say so. Slowing the drip rate is a standard adjustment, and staff would far rather adjust mid-session than have you white-knuckle it.
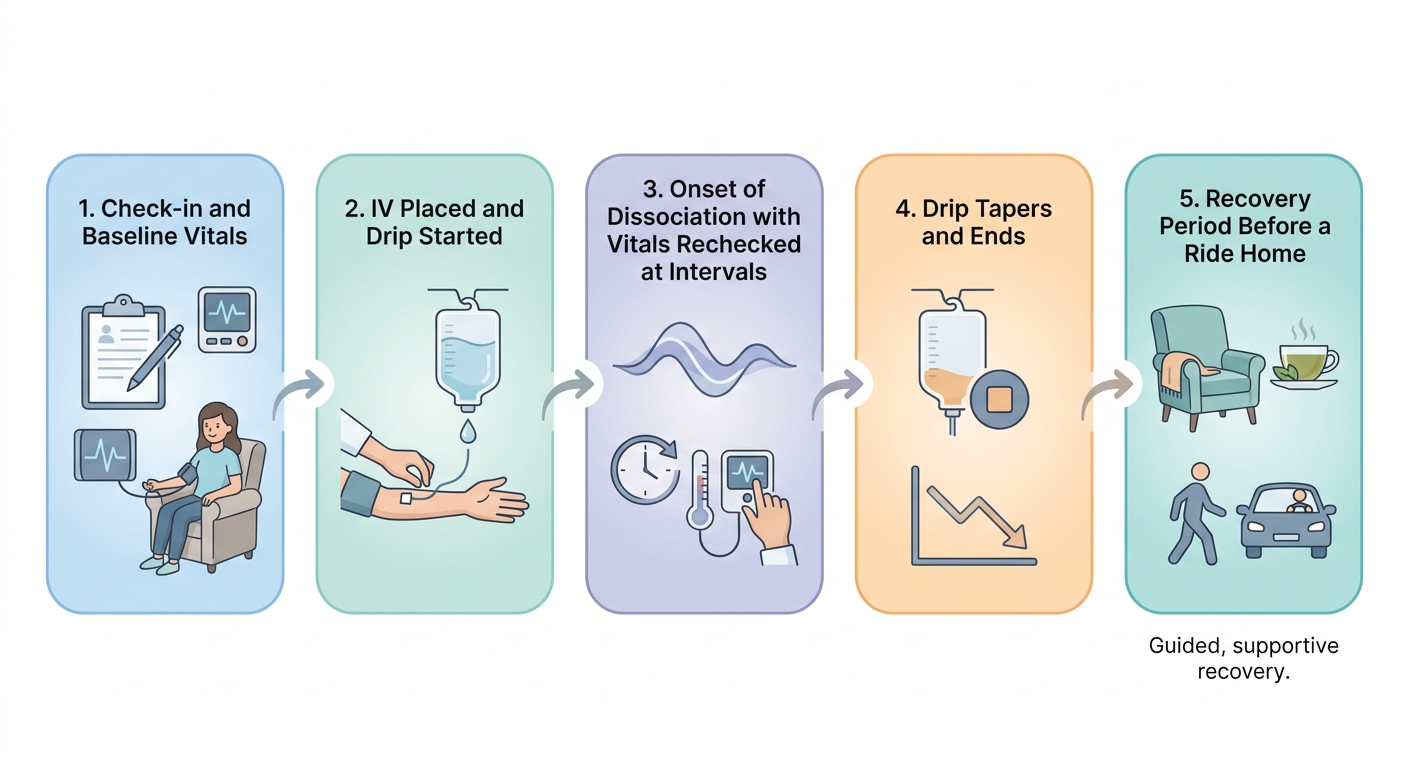
In sequence, a monitored session runs: check-in and baseline vitals → IV placed and drip started → onset of dissociation with vitals rechecked at intervals → drip tapers and ends → recovery period before a ride home.
Key takeaway: Most of what you feel during the drip is the medication's expected action, monitored in real time and adjustable on request.
The Hour-by-Hour Timeline: How Long Do Ketamine Side Effects Last?
Acute effects generally resolve within the hour or two after the infusion ends, with residual tiredness possible for the rest of the day. Ketamine has a short duration of action, which is the main reason the in-chair experience does not linger, as described in the StatPearls ketamine monograph.
| Time point | What most people report |
|---|---|
| First few minutes | Warmth, mild dizziness, early floating sensation |
| Mid-infusion | Peak dissociation, time distortion, visual drift; vitals rechecked |
| Final minutes of the drip | Intensity tapers noticeably as the rate winds down |
| 30–60 minutes after | Orientation returns; unsteadiness on standing is common |
| 1–2 hours after | Supervised recovery, then a ride home with another adult |
| That evening | Tiredness, appetite changes, vivid dreams, an early bedtime |
| Next morning | Usually clear-headed; no driving or safety-sensitive work until then |
That last row matters. The FDA prescribing information for SPRAVATO (esketamine) nasal spray instructs patients not to drive or operate machinery until the next day following a restful sleep — a conservative standard that infusion clinics apply to IV sessions as well. Plan your ride and your evening before you arrive.
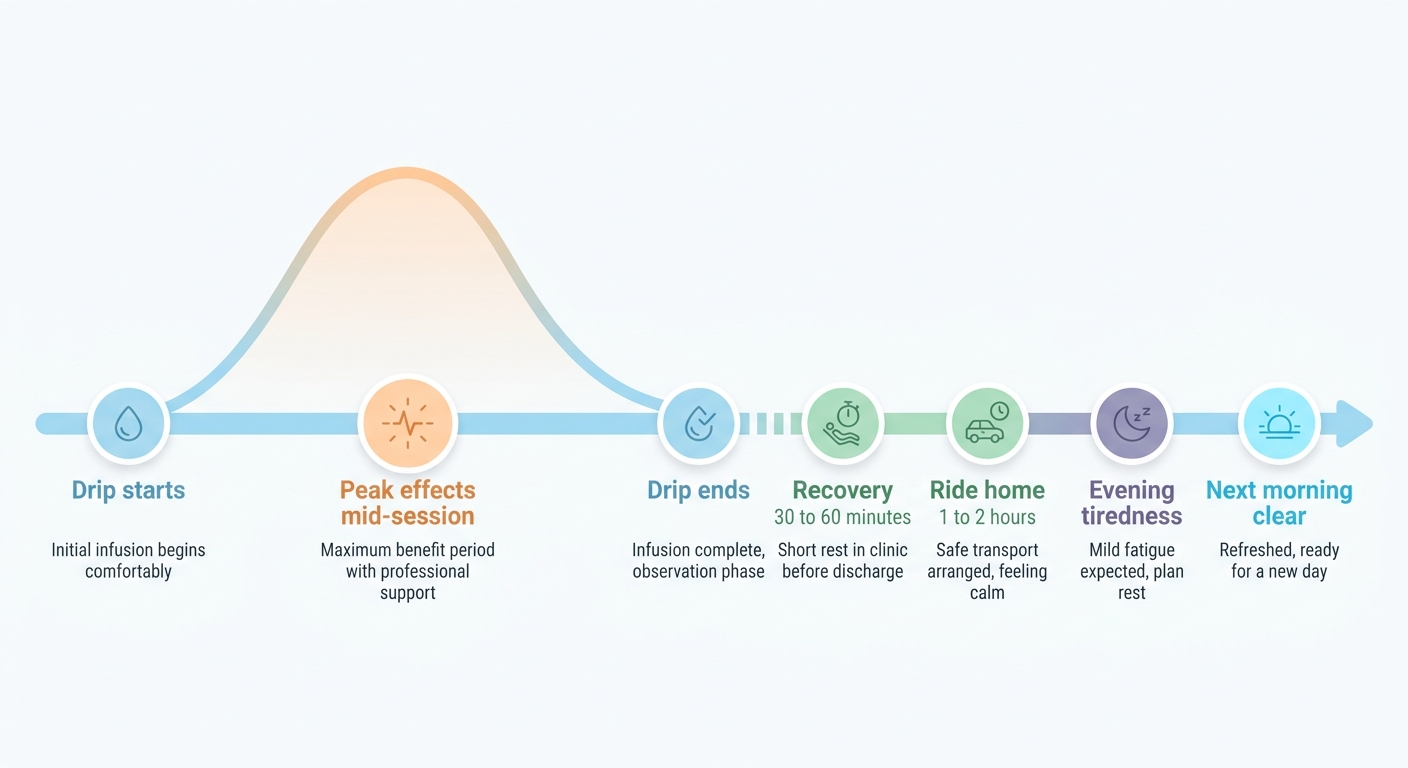
Plotted as a curve, intensity climbs from the moment the drip starts, peaks mid-session, then falls steadily through the end of the drip, the 30-to-60-minute recovery window, the ride home, evening tiredness, and a clear next morning.
A useful mental model: effects that arrive with the drip leave with the drip, while effects that arrive afterward are mostly fatigue-shaped. For a fuller look at which effects are measured in minutes versus which belong to a longer horizon, see our minutes-versus-months breakdown.
Key takeaway: Build your schedule around a quiet evening and a next-morning restart, not around being back at your desk in two hours.
Which Side Effects Are Common, Which Are Rare?
Frequency matters more than the raw list. A page that stacks "hallucinations" next to "drowsiness" without ranking them makes a routine session sound alarming. Here is the same information sorted by how often it tends to come up in supervised infusion care.
| Tier | Effects |
|---|---|
| Commonly reported | Dissociation, dizziness, nausea, transient rise in blood pressure or heart rate, headache |
| Less common | Vomiting, anxiety or agitation during the drip, blurred vision lasting past the recovery hour, irritation at the IV site |
| Uncommon | Emergence agitation requiring intervention, blood pressure elevation needing treatment, dissociation that outlasts the expected window |
Emergence phenomena are the confusion, agitation, or vivid dreamlike states that can occur as a person comes out of ketamine's effects; they are among the adverse effects documented in the clinical literature on ketamine and are a standard part of what recovery-period monitoring is designed to catch.
Two honest qualifiers belong here. First, published safety data come from specific dosing protocols and screened patients, so your personal risk depends on your health history — that is what a consultation is for. Second, individual results and individual experiences vary; two people on the same schedule can describe very different sessions.
⚠️ Cardiovascular effects deserve particular respect. Because ketamine can raise blood pressure and heart rate, uncontrolled hypertension and certain cardiac histories are screening questions rather than footnotes.
Key takeaway: The effects you are most likely to meet are mild and short-lived; the frightening ones sit in the uncommon tier and are exactly what monitoring exists to catch.
What About Bladder Problems, Memory, and Dependence?
These three concerns are legitimate, and they deserve a straight answer rather than reassurance. The bladder injury, cognitive changes, and misuse patterns documented in the literature come overwhelmingly from frequent, high-dose, long-running recreational use — a very different exposure from a spaced clinical series.
- Bladder and urinary effects. Urinary and bladder complications are recognized in the clinical literature on ketamine, associated with chronic heavy use. Painful, frequent, or bloody urination is a symptom to report to your prescriber, not to wait out.
- Memory and thinking. Cohort research on long-term recreational users has reported cognitive difficulties, which is why prescribers ask about frequency and re-dosing rather than treating dose as unlimited.
- Dependence and misuse. Ketamine is a controlled substance with recognized misuse potential. In practice, this is managed through prescriber control of supply, scheduled in-clinic administration, and honest conversation about history of substance use.
Because the clinical evidence base for repeated sub-anesthetic dosing is still developing, the responsible posture is monitoring rather than dismissal — periodic check-ins about urinary symptoms, mood, memory, and any urge to dose outside the plan. Our guide to the long-term effects of ketamine therapy covers the longer horizon in more depth.
⚠️ Unmonitored at-home dosing makes this picture harder to read. When nobody is tracking how much is taken or how often, early warning signs — creeping frequency, urinary symptoms, tolerance — can go unnoticed for months.
Depression itself also shapes this conversation. The National Institute of Mental Health describes depression as a serious but treatable condition with multiple treatment paths, and weighing any one option means weighing it against the alternatives with a clinician.
How Do Clinics Actually Reduce These Side Effects?
Most infusion side effects are dose-, rate-, and setting-dependent, which means they can largely be designed around. That is the core argument for in-clinic administration over dosing alone at home.

Before the drip begins, a clinician places a blood pressure cuff on the patient's upper arm while they settle into the recliner — the baseline reading every later vitals check is compared against.
A well-run protocol typically includes:
- Pre-treatment screening — blood pressure, cardiac history, thyroid status, and any history of bipolar disorder or psychosis, since those change candidacy and monitoring.
- Anti-nausea medication before the drip — commonly given in advance rather than in response to symptoms.
- A fasting window — usually no solid food for several hours and only clear liquids closer to the appointment, which reduces the chance of vomiting.
- Eye mask and curated audio — a quiet, low-stimulation environment tends to make dissociation feel less disorienting.
- A slow, adjustable drip rate — reducing the rate mid-session is a normal response to intensity that feels overwhelming.
- Repeated vitals checks — so a blood pressure change is noticed at minute 15, not at checkout.
- A required ride home — arranged before the session, not figured out afterward.
- A recovery period — time to reorient in the chair before standing, walking, or making decisions.
Preparation on your side moves the needle too: honest medication disclosure, a light schedule for the rest of the day, hydration, and a realistic mindset about the first session. Our guide to preparing for your first session covers the practical checklist in more detail.
Key takeaway: The difference between a rough session and a manageable one is usually screening, timing, and rate — all things a monitored clinic controls and an unsupervised dose does not.
When Should You Call Your Clinic?
Call about anything that outlasts its expected window. The point of knowing the timeline is so you can tell a normal evening from a reason to pick up the phone.
Contact your provider promptly for:
- Dissociation or confusion persisting well past the recovery window rather than steadily fading.
- Vomiting that prevents you from keeping down fluids.
- Chest pain, severe headache, or visual changes that do not settle.
- Painful, frequent, or bloody urination in the days after a session.
- Worsening mood, hopelessness, or thoughts of self-harm — this is an urgent call, not a next-appointment topic.
- Unusual elevation, racing thoughts, or reduced need for sleep, particularly with any bipolar history.
For emergencies, use 911 or your nearest emergency department. For mental health crises in the US, the 988 Suicide & Crisis Lifeline is available by call or text. Routine questions about scheduling, cost, and monitoring are answered in our ketamine safety and process FAQ.
Key takeaway: Expected effects fade on a predictable curve; anything that intensifies, persists, or involves your heart, head, bladder, or mood warrants a call.
Summary
Clinical ketamine side effects cluster into three tidy buckets: what happens in the chair (dissociation, dizziness, blurred vision, blood pressure changes), what happens that evening (tiredness, vivid dreams, appetite shifts), and what needs a phone call (anything that outlasts its window). The bladder, memory, and dependence concerns that dominate search results come primarily from frequent high-dose misuse, not from a screened, spaced, supervised infusion series — though they remain worth monitoring honestly. Suitability is decided in a clinical consultation, and experiences vary from person to person.
Frequently Asked Questions
How long do ketamine side effects last after one infusion?
Acute effects typically ease within the first hour or two after the drip ends, largely because ketamine has a short duration of action. Many people feel tired or a little foggy for the rest of the day, then clear-headed the next morning. Standard practice is no driving or safety-sensitive work until the following day.
Is nausea after a ketamine infusion normal?
Yes — nausea is among the most commonly reported ketamine infusion side effects. It is usually addressed preventively with anti-nausea medication given before the drip starts, combined with a fasting window so your stomach is empty. Tell your care team if you have a history of motion sickness or post-anesthesia nausea, since that changes the plan.
Can I drive myself home after a ketamine infusion?
No. Arrange an adult driver or a rideshare before your appointment. The FDA label for SPRAVATO (esketamine) directs patients not to drive or operate machinery until the day after a restful sleep, and infusion clinics apply the same conservative standard.
Do IV infusion side effects differ from Spravato or oral ketamine?
Yes. Route affects how quickly effects arrive, how intense the peak feels, and how long you are observed afterward. Esketamine nasal spray is given under a REMS program with a required post-dose monitoring period, per its FDA prescribing information. Oral or at-home dosing shifts the experience into an unmonitored setting, which changes what can be adjusted mid-dose — our ketamine safety and process FAQ covers those differences.
Do side effects get milder with later infusions in a series?
Many people describe later sessions as more predictable than the first, partly because dose and drip rate get tuned to how they responded and partly because anticipatory anxiety drops once the experience is familiar. This is a pattern patients commonly report, not a guaranteed trajectory. Keep reporting each session honestly so adjustments can continue.
What should I eat or drink before my appointment?
Follow the fasting window your clinic gives you — typically no solid food for several hours beforehand, with clear liquids allowed closer to the appointment. An empty stomach is one of the simplest ways to reduce the odds of vomiting. Steady hydration in the day or two before helps as well, and our guide to preparing for your first session walks through the rest of the checklist.
Does a stronger side effect mean ketamine therapy is working better?
No. The intensity of dissociation is not a reliable scorecard for how the treatment is working. Some people have vivid sessions and modest change; others barely drift and still respond. Report what you felt honestly rather than trying to chase or avoid a particular experience — your prescriber uses those reports to adjust dose, rate, and spacing over the series.
Should I tell my clinic about medications and supplements?
Yes, all of them — prescriptions, over-the-counter products, and supplements — before your first appointment. Blood pressure medications, sedatives, and anything affecting mood are especially relevant to screening and monitoring. Never stop or change a medication on your own; that decision belongs to the prescriber who wrote it.
How much of my day should I block off for a session?
Plan for the appointment itself plus a supervised recovery period, a ride home with another adult, and a quiet evening afterward. Most people find the rest of the day is best kept free of work, errands, and big decisions. If you are driving in from Nampa or Caldwell, factor the travel time into the ride you arrange.
Can I bring someone with me to my infusion?
Ask your clinic — policies vary by treatment room and session type, and your driver often waits nearby rather than in the chair-side space. What matters most is that someone knows your schedule and can get you home safely. Bringing a familiar person for check-in and pickup helps many first-timers feel steadier about the whole thing.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.