Ketamine for CRPS: Who It Helps and How Well
Zora Neuro Spa Editorial · September 30, 2026
Complex Regional Pain Syndrome turns a healed injury into a limb that burns, swells, and flinches at the touch of a bedsheet — and the usual painkillers often barely move it. That's why so many Treasure Valley patients start researching ketamine for CRPS treatment after sympathetic blocks, nerve medications, and physical therapy have all fallen short. This guide covers who tends to qualify, what the evidence actually supports, how it stacks up against other CRPS options, and what getting started looks like in Boise and Eagle.
Quick Answer
Ketamine is an anesthetic and NMDA-receptor antagonist used off-label for CRPS, given as a series of low-dose intravenous infusions under medical monitoring. The goal is to quiet the central nervous system's amplified pain signaling — not to cure the condition. Relief, when it happens, is usually partial and temporary, and it varies a lot between individuals. Most pain specialists position it as a second- or third-line option that works best alongside physical therapy, and suitability is decided in a clinical consultation, such as a CRPS treatment consultation in Eagle, Idaho.
TL;DR
- Ketamine blocks the NMDA receptor, a pathway tied to the central sensitization that makes CRPS pain spread and persist. See why CRPS behaves differently from ordinary pain
- Candidacy is specific, not universal — a confirmed diagnosis, failed first-line care, and a cleared cardiovascular and psychiatric screen all matter. Review the candidacy checklist
- There is no single FDA-approved CRPS protocol. Clinics use different infusion models, and the model changes the time commitment. Compare the three common protocol models
- Evidence is stronger for short-term pain scores than for lasting functional gains, which is exactly why rehab pairing is emphasized. Read the evidence breakdown by CRPS stage
- Off-label use usually means out-of-pocket. Spravato's FDA approval is for depression, not pain. See how cost and insurance actually work
In This Article
- Why Does CRPS Respond to Ketamine When Other Painkillers Fail?
- Who Is a Good Candidate for Ketamine for CRPS Treatment?
- What Does a CRPS Ketamine Protocol Actually Look Like?
- What Does the Evidence Show, by CRPS Stage and Duration?
- How Does Ketamine Compare to Other CRPS Treatments?
- What Are the Risks and Side Effects?
- What Does CRPS Ketamine Treatment Cost, and Will Insurance Cover It?
- How Do You Get Started With CRPS Ketamine Care in the Treasure Valley?
- Frequently Asked Questions
Why Does CRPS Respond to Ketamine When Other Painkillers Fail?
CRPS pain is generated and amplified inside the central nervous system, not only at the injured limb. That's the core reason drugs aimed at tissue inflammation or peripheral nerves so often disappoint. Ketamine works at a different address entirely.
Central sensitization refers to a state in which pain-processing neurons in the spinal cord and brain become hyper-responsive, so ordinary input — light touch, cool air, clothing — registers as severe pain. Once that amplification is established, the original injury is no longer the main driver. The wiring is.
Ketamine is an NMDA receptor antagonist, meaning it blocks a glutamate receptor involved in how pain signals are relayed and reinforced in the central nervous system. It has a long history in anesthesia and is also used at lower, subanesthetic doses in pain management settings, as described in the clinical monograph on ketamine published on NCBI Bookshelf. Blocking that receptor is the mechanistic rationale pain physicians cite when they consider infusions for neuropathic-type pain syndromes.
Opioids, by contrast, act on a separate receptor system. For some people with long-standing CRPS they provide limited benefit, and clinicians also weigh the possibility of opioid-induced hyperalgesia — increased pain sensitivity associated with ongoing opioid exposure. That mismatch between the drug's target and the actual pain mechanism is a recurring theme in why CRPS resists conventional pain treatment.
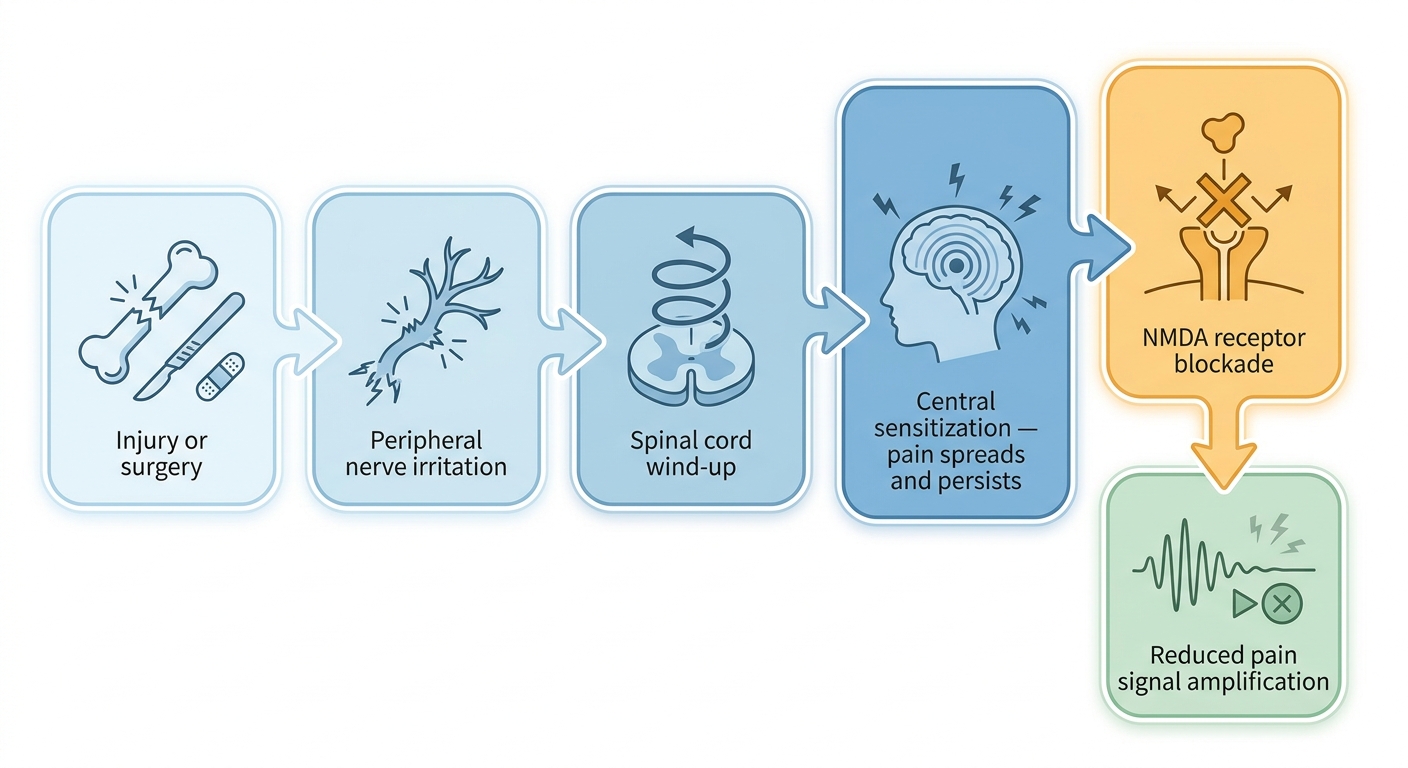
Here's the sequence clinicians are trying to interrupt:
- Injury or surgery — often minor, sometimes trivial relative to the pain that follows
- Peripheral nerve irritation — abnormal signaling begins in the affected limb
- Spinal "wind-up" — repeated input makes dorsal horn neurons progressively more reactive
- Central sensitization — pain spreads, outlasts healing, and resists peripheral treatments
- NMDA receptor blockade — the point where ketamine is introduced into the picture
Key takeaway: Ketamine is considered for CRPS because it targets central amplification rather than peripheral tissue — a different mechanism than most first-line pain drugs.
Who Is a Good Candidate for Ketamine for CRPS Treatment?
The strongest candidates have a confirmed CRPS diagnosis, symptoms that haven't responded adequately to first-line care, stable cardiovascular and psychiatric health, and the ability to participate in physical therapy afterward. Candidacy is a clinical decision, made after a full history review — not something you can self-determine from an article.
What diagnostic criteria do clinicians use?
The Budapest Criteria are the diagnostic standard pain specialists commonly use for CRPS. They require continuing pain disproportionate to the original injury, plus reported symptoms and observed signs across four categories:
- Sensory — hyperalgesia (heightened pain response) or allodynia (pain from non-painful touch)
- Vasomotor — temperature differences, skin color changes or asymmetry
- Sudomotor/edema — swelling, or changes in sweating patterns
- Motor/trophic — reduced range of motion, weakness, tremor, or changes to hair, nail, and skin texture
A clinician also has to rule out other conditions that would better explain the findings. Bringing prior imaging, specialist notes, and any documented block results to your consult makes this step faster.
Which factors make someone more likely to be accepted?
- Documented first-line attempts — physical therapy, gabapentinoids, sympathetic blocks, or topical agents already tried
- Shorter symptom duration — earlier-stage CRPS is generally prioritized in pain-medicine practice
- Rehab readiness — a PT plan you can actually engage with after infusions
- Controlled blood pressure — ketamine can raise blood pressure and heart rate, so this is screened
- Stable psychiatric status — no active psychosis or untreated substance use disorder
- A support plan — including a driver for infusion days
What typically rules someone out?
Common exclusions discussed during screening include pregnancy, severe hepatic disease, conditions involving elevated intracranial or intraocular pressure, uncontrolled hypertension, and a history of ketamine-associated bladder problems (cystitis). Certain cardiac histories require clearance first. Some of these are absolute; others simply mean more workup before a decision. The ketamine clinical monograph on NCBI Bookshelf outlines the contraindications and monitoring considerations clinicians weigh.

If you're weighing whether your case fits, a CRPS treatment consultation in Eagle, Idaho is where that assessment happens — including an honest answer if infusions aren't the right next step for you.
Key takeaway: Ketamine candidacy for CRPS depends on a confirmed diagnosis, failed first-line care, medical clearance, and a realistic rehab plan — all confirmed in consultation.
What Does a CRPS Ketamine Protocol Actually Look Like?
There is no single FDA-approved ketamine protocol for CRPS, because the use is off-label. Clinics generally follow one of three broad models, and they differ enormously in dose intensity, time commitment, and setting. Knowing which model a clinic uses is one of the most useful questions you can ask on a first call.
| Protocol model | Dose level | Session length | Course structure | Setting |
|---|---|---|---|---|
| Standard low-dose outpatient series | Subanesthetic | Under about an hour | Repeated sessions over a few weeks | Outpatient clinic, monitored |
| Extended multi-hour outpatient infusions | Subanesthetic, often escalating | Several hours per session | Consecutive-day block, sometimes over a week or more | Dedicated infusion program |
| Anesthetic-dose "ketamine coma" | Anesthetic | Continuous, multi-day | One-time intensive admission | Inpatient/ICU; studied outside routine US outpatient care |
⚠️ The anesthetic-dose ("ketamine coma") approach is an intensive-care intervention, not an outpatient service. If a clinic markets anything resembling it in an office setting, treat that as a serious red flag.
How is the dose determined?
Dosing is weight-based and individualized. Your clinician sets a starting rate, then adjusts based on how you tolerate it — blood pressure response, nausea, and how dissociative the experience feels. Ketamine is administered at doses well below those used for general anesthesia in these pain protocols, with continuous monitoring throughout, consistent with the administration guidance in the NCBI ketamine monograph.
Practical elements most CRPS protocols share:
- A loading phase — a clustered series of infusions rather than a single session
- A reassessment point — a scheduled check on pain, function, and side effects after the series
- A maintenance decision — booster infusions scheduled based on how long benefit holds
- PT coordination — rehab timed to follow infusions, not run independently of them
- Adjunct medications — some clinics use agents like midazolam or anti-nausea medication to improve tolerability
How often are booster infusions scheduled?
Booster cadence is set by response, not by a fixed calendar. If relief fades, the interval tightens; if it holds, the interval stretches. Many programs start with a planned reassessment rather than pre-booking a year of appointments, which keeps the plan tied to your actual results.
For the mechanics of dosing, infusion rates, and session-by-session structure, we go deeper in our breakdown of how CRPS infusion dosing and protocols actually work.
What Does the Evidence Show, by CRPS Stage and Duration?
Randomized research on ketamine in CRPS has generally reported short-term reductions in pain scores, with the measured benefit diminishing over the following weeks. Trials have used both continuous multi-day infusions and repeated multi-hour sessions. Two honest caveats belong up front: individual results vary widely, and pain relief in these studies has consistently been easier to demonstrate than lasting improvement in physical function.
That gap between pain and function is the single most important thing patients aren't told often enough. It's the whole argument for pairing infusions with rehabilitation rather than treating them as a standalone fix.
Early CRPS (Under About 12 Months)
Earlier intervention is generally prioritized in pain-medicine practice, on the reasoning that central changes are less entrenched before the condition becomes long-standing. Clinicians often describe a "warm" phase — a limb that's swollen, red, and hot — and a later "cold" phase with a pale, cool, sometimes atrophic limb.
Patients in the earlier phase tend to be the ones specialists are most eager to get into aggressive multimodal care quickly, including movement-based therapy. That urgency is about preserving function while it's still preservable. It is not a promise of a particular outcome, and response still varies from person to person.
Long-Standing or Cold-Phase CRPS
Relief is still considered possible in long-duration CRPS, but expectations should be calibrated differently. In practice, clinicians treating established cases plan for smaller gains, shorter-lived benefit, and a maintenance schedule from the outset rather than a single curative series.
That doesn't make treatment pointless. For someone who has lived with a limb they can't tolerate touching, even a partial reduction in pain intensity that creates room for desensitization work can matter. The framing that helps most: ketamine may open a window; what you do inside that window determines how much of it sticks.
Why does function lag behind pain relief?
Because years of guarding, disuse, and fear of movement don't unwind chemically. A limb that hasn't borne weight or been touched in two years needs graded exposure, motor retraining, and time.
- Pain scores can change during and after an infusion series
- Strength, range of motion, and limb use change only with loaded, repeated practice
- Graded motor imagery and mirror therapy are the rehab tools most associated with CRPS-specific retraining
- Timing matters — rehab scheduled close to infusions is the standard coordination strategy
Key takeaway: Treat the evidence as supporting a time-limited reduction in pain for some patients — a window for rehabilitation, not a replacement for it.
How Does Ketamine Compare to Other CRPS Treatments?
Ketamine generally sits in the second- or third-line tier for CRPS — after physical therapy, graded motor imagery, and nerve-pain medications, and often considered alongside or before spinal cord stimulation. It isn't a substitute for movement-based rehab. It's a tool some clinicians use to make rehab tolerable.
| Option | How it works | Invasiveness | Typically suits |
|---|---|---|---|
| Physical therapy, graded motor imagery, mirror therapy | Retrains the brain's map of the limb and rebuilds tolerance to movement and touch | None | Everyone with CRPS; considered foundational at every stage |
| Gabapentin / pregabalin | Calms abnormal nerve signaling | Oral medication | Neuropathic features; those who tolerate sedation and dizziness |
| Bisphosphonates | Act on bone turnover, which is altered in some CRPS cases | Oral or IV | Often discussed in earlier-stage disease with bone changes |
| Sympathetic nerve blocks | Interrupt sympathetic nerve outflow to the limb | Injection procedure | Diagnostic and therapeutic use in sympathetically maintained pain |
| IV ketamine infusions | NMDA receptor antagonism targeting central sensitization | IV, monitored, off-label | Refractory cases after first-line care, with rehab planned |
| Spinal cord stimulation | Implanted device modulates dorsal column signaling | Surgical implant | Refractory cases after less invasive options are exhausted |
| Opioids | Act on opioid receptors | Oral or patch | Limited role; clinicians weigh hyperalgesia and dependence risks |
Where does ketamine fit in a realistic treatment sequence?
Most pain physicians escalate stepwise. You start with rehab and oral agents, add blocks if the picture fits, and reserve infusions and neuromodulation for cases that stay refractory. Jumping straight to infusions skips steps that are lower-risk and often lower-cost.
- Before ketamine: PT/GMI, neuropathic medications, topical agents, sympathetic blocks
- Alongside ketamine: continued PT, desensitization work, psychological support for pain coping
- After ketamine, if needed: spinal cord stimulation or other neuromodulation, evaluated by an interventional specialist
Does trying ketamine close off other options?
No. An infusion series doesn't disqualify you from later neuromodulation, blocks, or medication changes. Some patients use a ketamine series specifically to get functional enough to complete a stimulator trial or a rehab block they previously couldn't tolerate. Sequencing questions like these are worth raising directly in a chronic pain treatment consultation, where your full treatment history can be mapped out.
What Are the Risks and Side Effects?
In monitored clinical settings using low doses, the commonly reported effects are short-lived: dissociation (a floaty, detached feeling), nausea, dizziness, and elevated blood pressure and heart rate. These are expected, watched for, and generally resolve as the infusion wears off. The NCBI clinical monograph on ketamine details the adverse-effect profile and the monitoring that accompanies administration.

What monitoring should a clinic provide?
Ask directly. A CRPS infusion is a medical procedure, not a spa service. Reasonable standards include:
- Continuous vital sign monitoring — blood pressure, heart rate, pulse oximetry
- A licensed clinician present and trained in airway and cardiovascular management
- Emergency medications and equipment on site
- A structured recovery period before discharge
- A required driver — you cannot drive yourself home
How do clinical risks differ from recreational-use risks?
This distinction matters and most consumer articles blur it. The problems most associated with ketamine harm — bladder damage (ketamine-induced cystitis), cognitive complaints, and dependence — are reported in the context of frequent, high-dose, unsupervised use over extended periods. Supervised, intermittent, low-dose medical administration is a different exposure pattern entirely.
That's not a claim that clinical use is risk-free. It's the reason clinics track total exposure, space infusions out, screen for urinary symptoms, and reassess whether continued treatment is justified. If you develop urinary urgency, pain with urination, or memory changes, tell your provider rather than pushing through.
⚠️ Never combine ketamine treatment with unreported medications, alcohol, or recreational substances. Give your clinician a complete medication list, including supplements.
For a fuller breakdown of what to expect during and after a session, see our guide to the potential side effects of CRPS ketamine infusions.
What Does CRPS Ketamine Treatment Cost, and Will Insurance Cover It?
Because ketamine for CRPS is prescribed off-label, most US patients pay out of pocket. Coverage decisions vary by insurer and plan, and "off-label" is the usual reason a claim for the infusion itself is denied. The practical move is to get written pricing and a written explanation of what, if anything, may be billable in your specific case.
| Line item | What it covers | Coverage reality |
|---|---|---|
| Initial consultation | Diagnosis review, screening, protocol planning | Sometimes billable as an evaluation and management visit |
| Infusion sessions | Medication, administration, clinician time | Commonly self-pay for off-label pain indications |
| Monitoring and recovery | Vitals, nursing time, recovery period | Usually bundled into the session price |
| Booster infusions | Maintenance sessions after the initial series | Same self-pay expectation as the initial series |
| Physical therapy | Rehab that follows infusions | Often billable separately through your medical benefit |
Why is Spravato covered when IV ketamine usually isn't?
Because they're approved for different things. Spravato (esketamine) nasal spray is FDA-approved for treatment-resistant depression and for depressive symptoms in adults with major depressive disorder with acute suicidal ideation or behavior, administered under a restricted REMS program, according to the FDA prescribing information for SPRAVATO. It is not approved for CRPS or chronic pain. An FDA-approved indication is what creates a clear coverage pathway; off-label pain use does not have one.
What questions should you ask before paying?
- Is pricing per infusion or per package, and what happens if you stop mid-series?
- What exactly is included — monitoring, recovery time, follow-up visits, anti-nausea medication?
- Is a superbill provided so you can attempt out-of-network reimbursement?
- Are HSA or FSA funds accepted? Eligibility depends on your plan — confirm with your plan administrator.
- What's the booster cost, so you can budget for maintenance rather than just the first series?
Cost, safety, and process questions come up constantly, and we've collected the most common ones in our ketamine cost, safety and process FAQ.
How Do You Get Started With CRPS Ketamine Care in the Treasure Valley?
Start with a consultation that confirms the diagnosis, reviews everything you've already tried, screens your cardiovascular and psychiatric history, and produces a written plan with physical therapy coordinated around it. No reputable clinic should infuse you the same day you walk in with no records.
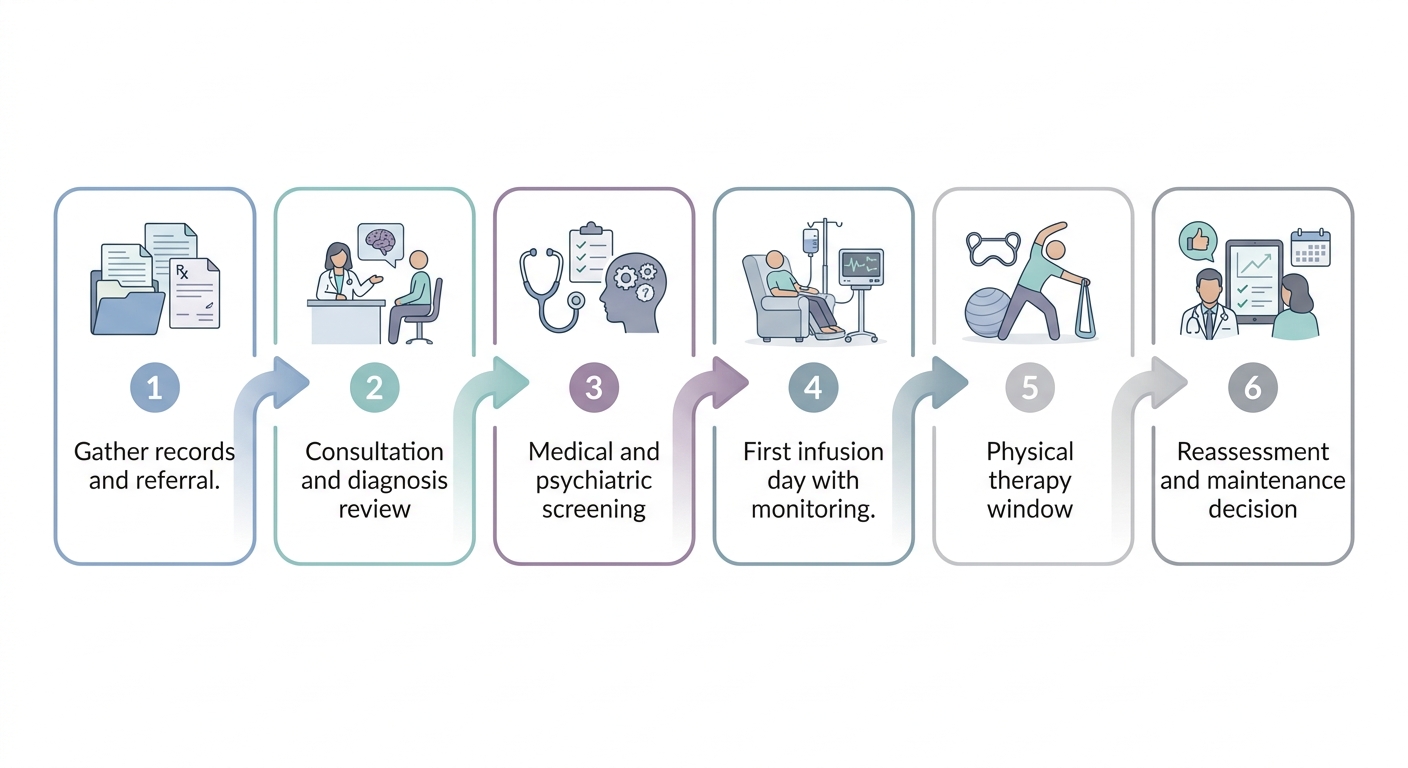
Here's how the sequence typically runs:
- Gather your records — imaging, specialist notes, prior sympathetic block results, and a current medication list
- Consultation — diagnosis confirmation against the Budapest Criteria and a review of prior treatments
- Medical screening — blood pressure, cardiac history, psychiatric history, substance use history, pregnancy status
- First infusion — monitored session with a driver arranged in advance
- Rehab window — physical therapy scheduled close to your infusions, not months later
- Reassessment — a structured check-in on pain, function, and side effects before any maintenance plan is set
What should Boise, Meridian, Nampa, and Kuna patients know about travel?
Eagle sits a short drive from most of the Treasure Valley, which makes a multi-session series logistically manageable for patients across Boise, Meridian, Nampa, and Kuna. Two planning points matter more than distance: you'll need a driver each infusion day, and you should schedule around your physical therapy rather than the other way around.
Patients searching for ketamine therapy in Boise often find that most local options are oriented toward mental health indications. CRPS is a different clinical problem with a different protocol, so ask specifically whether a clinic treats chronic pain conditions and how it coordinates with rehab providers.
A consultation is not a commitment. It's a conversation where a clinician looks at your history and tells you whether infusions make sense, whether something else should come first, or whether you're not a candidate at all — which is a legitimate and useful answer. You can book a CRPS treatment consultation in Eagle, Idaho to start that review.
Frequently Asked Questions
How many ketamine infusions are needed for CRPS?
Most CRPS programs begin with a clustered series of infusions over a short window rather than a single session, followed by booster infusions scheduled according to how long benefit lasts. The exact count depends on the protocol model your clinic uses and how you respond. Your clinician should give you the planned number in writing before you start.
How long does ketamine relief last for CRPS?
Duration varies substantially between individuals, and the research pattern in chronic pain has generally been temporary relief rather than permanent change. Some patients report benefit that fades over weeks and return for boosters; others notice little change. Expect your clinic to schedule a formal reassessment rather than assuming a fixed timeline.
Can ketamine cure CRPS?
No. It is not a cure, and any clinic suggesting otherwise is overpromising. The realistic framing is that infusions may reduce pain enough to create a window for rehabilitation, and sustained physical therapy during that window is what most clinicians associate with meaningful long-term progress. Results vary between individuals.
Is Spravato (esketamine) used for CRPS?
No. Spravato is FDA-approved for treatment-resistant depression and for depressive symptoms in adults with MDD with acute suicidal ideation or behavior, per the FDA prescribing information. CRPS protocols use intravenous ketamine off-label instead — a different drug formulation, route, and dosing approach.
Does ketamine work if sympathetic nerve blocks didn't?
Possibly, because the two target different mechanisms. Sympathetic blocks interrupt sympathetic nerve outflow to the limb, while ketamine acts centrally at the NMDA receptor. A poor response to blocks doesn't automatically predict a poor response to infusions, though it is one of the details your clinician will factor into the decision. More cost and process questions are answered in our ketamine cost, safety and process FAQ.
The Bottom Line on Ketamine for CRPS
Ketamine for CRPS treatment is a legitimate, mechanism-based option for refractory cases — and it is also frequently oversold. What the evidence supports is a time-limited reduction in pain for some patients, delivered through monitored low-dose infusions, with individual results varying widely. What it does not support is a cure, a guaranteed outcome, or a reason to stop rehabilitation.
The patients who tend to get the most out of it are the ones who treat it as a window-opener: confirmed diagnosis, realistic expectations, physical therapy scheduled around the infusions, and a clinician willing to reassess honestly rather than sell a package.
If you're in Boise, Eagle, Meridian, Nampa, or Kuna and you've already worked through first-line care without relief, the next step is a straightforward one — a CRPS treatment consultation in Eagle, Idaho where someone reviews your actual history and tells you what they'd recommend, infusions or not.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.