What the Research Says About Ketamine for Depression
Zora Neuro Spa Editorial · September 28, 2026

Depression that hasn't budged after two or more medications leaves people asking a fair, skeptical question: is there actual evidence behind ketamine treatment for depression, or is it hype with an IV pole? This guide walks through what the research base currently supports, what ketamine-assisted psychotherapy adds on top of the medicine, and — just as importantly — the questions the science hasn't answered yet.
Quick Answer
Ketamine treatment for depression is studied mainly in adults whose symptoms haven't improved with standard antidepressants. Ketamine works on the brain's glutamate system by blocking NMDA receptors, a different target than the serotonin pathway used by SSRIs (StatPearls). One form — esketamine nasal spray — is FDA-approved for treatment-resistant depression in adults when used with an oral antidepressant (SPRAVATO prescribing information). IV ketamine for depression is used off-label. Results vary between individuals, and suitability is decided in a clinical consultation.
TL;DR
- The strongest regulatory evidence sits with esketamine nasal spray, which carries an FDA-approved indication for treatment-resistant depression. See how the evidence base breaks down
- Ketamine's mechanism is pharmacologically different from SSRIs — it targets glutamate signaling, not serotonin reuptake. Read the mechanism in plain language
- Ketamine-assisted psychotherapy (KAP) adds structured preparation and integration sessions around the medicine session. Walk through the three phases
- Route matters: IV, nasal spray, and at-home oral differ in regulatory status, monitoring rules, and how thoroughly they've been studied. Compare the three routes side by side
- Candidacy is narrower than most marketing suggests, and several conditions are listed as contraindications on the FDA label. Check the candidacy criteria
In This Article
- What Does the Research Actually Show About Ketamine for Depression?
- Why Does Ketamine Act on a Different Brain System Than SSRIs?
- How Does Ketamine-Assisted Psychotherapy Work, Step by Step?
- IV Infusion, Esketamine, or KAP — Which Route Fits Which Patient?
- Who Qualifies for Ketamine Treatment for Depression?
- How Long Does Relief Last, and What Does Maintenance Look Like?
- What Are the Limits of the Evidence Right Now?
- Frequently Asked Questions
What Does the Research Actually Show About Ketamine for Depression?
The clearest, most verifiable evidence point is regulatory: the FDA approved esketamine nasal spray, sold as SPRAVATO, for treatment-resistant depression in adults in combination with an oral antidepressant, and its label also describes an indication for depressive symptoms in adults with major depressive disorder and acute suicidal ideation or behavior (SPRAVATO prescribing information). That approval means a regulator reviewed controlled trial data and found the evidence sufficient for a specific, narrow population.
Treatment-resistant depression (TRD) refers to depression that hasn't responded adequately to at least two antidepressant trials of adequate dose and duration. That definition matters because it is the population studied — not people trying a first antidepressant, and not everyday low mood. The National Institute of Mental Health's overview of depression describes the broader treatment landscape these patients have usually already worked through.
IV ketamine for depression sits in a different category. Ketamine itself is an FDA-approved anesthetic, and its use for mood disorders is off-label, meaning a licensed clinician prescribes an approved drug for a purpose outside the labeled indication (StatPearls). Off-label doesn't mean unstudied or improper — it means the sponsor never pursued that specific labeling.
Here's an honest map of where the different kinds of evidence sit:
| Line of evidence | What it establishes | What it does not settle |
|---|---|---|
| FDA approval of esketamine nasal spray | A regulator reviewed controlled data for a defined TRD population, plus administration and safety requirements | Whether it outperforms IV ketamine, or how well it works long-term for any individual |
| Peer-reviewed pharmacology (NMDA antagonism, dissociative effects, monitoring needs) | How the drug acts and what clinicians must watch for | How mechanism translates into durable symptom change |
| Published randomized trials of IV ketamine in depression | That the question has been studied in controlled conditions | Effect size across diverse real-world patients; most trials are small and short |
| Clinic-reported outcomes and case series | How protocols are run in practice | Anything generalizable — these are not controlled comparisons |
| Long-term follow-up data | Early signals about maintenance dosing | Multi-year safety and durability, which remain thin |
Two things follow from that table. First, anyone quoting a precise success percentage should be able to name the study, the population, the timepoint, and the comparison group. Second, the brain-level rationale — covered in more depth in how ketamine works on the brain — is genuinely different from older antidepressants, which is why researchers keep returning to it.
Key takeaway: The evidence is real and regulator-reviewed for esketamine in treatment-resistant depression, but it is narrower and younger than the marketing around ketamine often implies.
Why Does Ketamine Act on a Different Brain System Than SSRIs?
Ketamine is an NMDA receptor antagonist — it blocks a specific glutamate receptor in the brain (StatPearls). SSRIs act on serotonin reuptake. That's the whole reason ketamine entered depression research: it approaches the problem from an entirely separate pharmacological direction.
Glutamate is the brain's main excitatory messenger, involved in learning and memory. Researchers propose that blocking NMDA receptors triggers a temporary shift in glutamate signaling, which in turn engages other receptors and growth-related pathways. The downstream steps most often described in the literature involve AMPA receptor activation and growth factors associated with synapse formation. These are proposed mechanisms under active study, not settled facts about why any one person's symptoms change.
Neuroplasticity is the brain's ability to form and reshape synaptic connections between neurons. Clinicians and researchers frequently describe a post-dose "window of plasticity" in the days following a session, during which the brain may be more responsive to new learning. The exact length and reliability of that window haven't been pinned down.
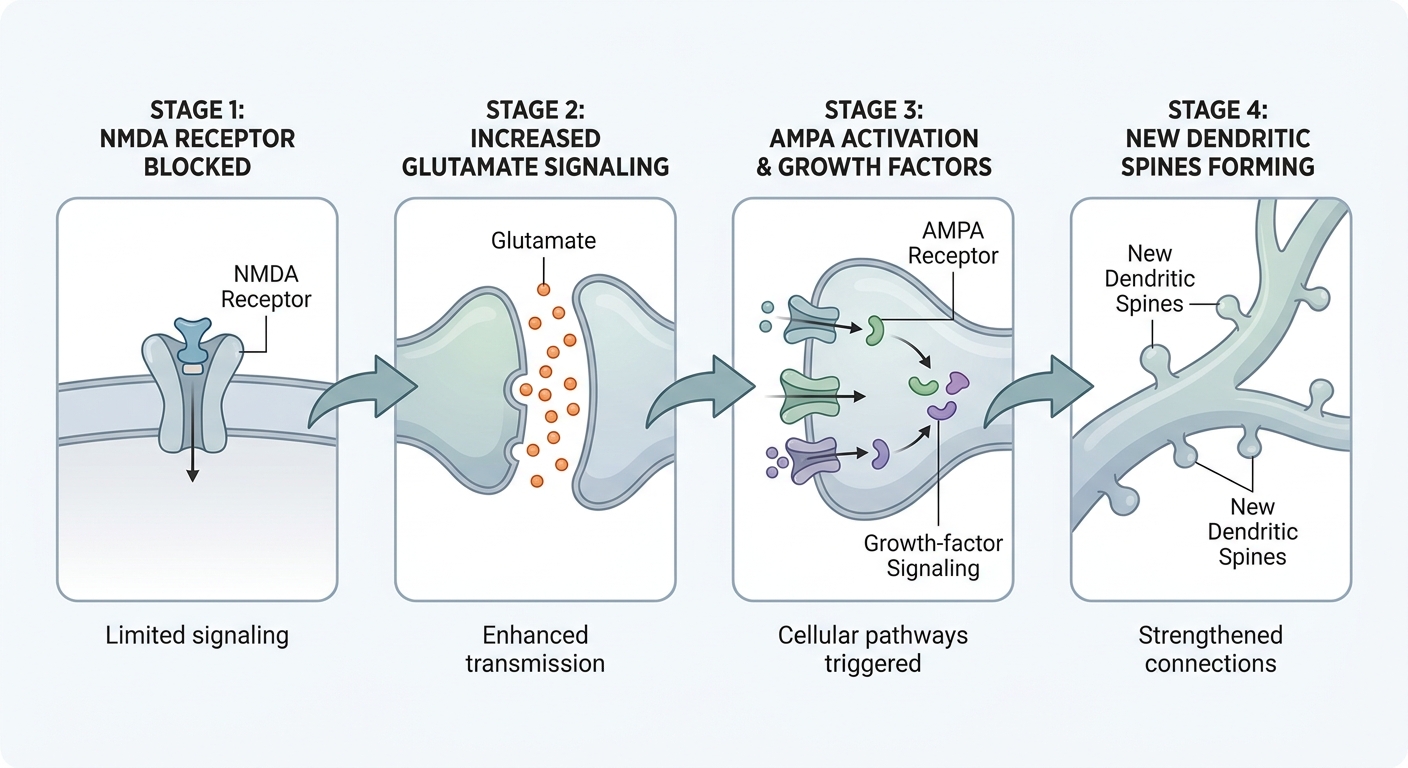
That proposed plasticity window is the entire intellectual argument for pairing medicine with therapy rather than delivering it alone. If the brain is temporarily more open to forming new patterns, the reasoning goes, structured psychological work during that period may be more useful than the same work done at a random time. It's a plausible and widely discussed rationale — and it's also why structured protocols schedule follow-up therapy rather than leaving patients to figure it out. For the session-level experience, see what a ketamine-assisted psychotherapy session involves step by step.
Two practical notes that follow from the mechanism:
- Dissociation is expected, not a malfunction. Perceptual and dissociative effects are documented features of ketamine's action and are part of why monitored settings are used (StatPearls).
- Blood pressure changes are monitored. Cardiovascular effects are a known consideration, which is why vitals are checked during and after dosing.
Key takeaway: Ketamine's glutamate-based mechanism is why researchers study it in people who didn't respond to serotonin-based drugs — but mechanism alone never guarantees an individual outcome.
How Does Ketamine-Assisted Psychotherapy Work, Step by Step?
Ketamine-assisted psychotherapy (KAP) is a structured protocol in which a trained therapist is involved before, during, or immediately after a supervised ketamine session, so the medicine and the psychological work are planned as one course of care rather than two separate services.
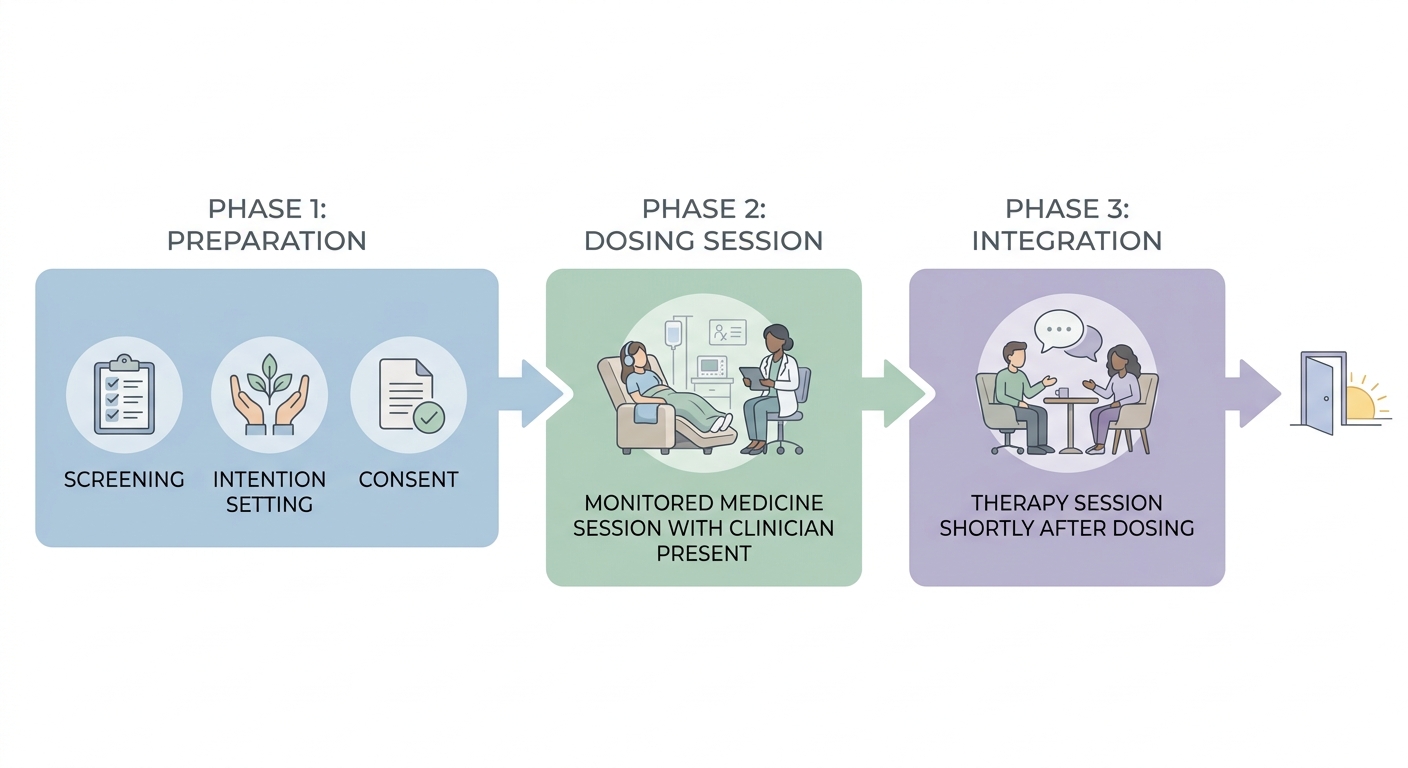
Most KAP programs follow three phases: preparation, dosing, and integration. The clinical argument for the structure is the plasticity window described above — the idea that therapy scheduled close to dosing makes use of a period when the brain may be more receptive. Head-to-head research comparing KAP against medicine alone is still limited, so treat this as a reasoned protocol rather than a proven upgrade.
Phase 1: Preparation — What Happens Before Dosing?
Preparation usually takes one or two appointments and covers medical screening, expectation-setting, and informed consent. It is where candidacy is actually decided.
A preparation visit commonly includes:
- Baseline symptom scoring — standardized scales such as the PHQ-9 for depression and GAD-7 for anxiety, so change can be tracked objectively rather than by memory.
- Vital signs and cardiovascular screening — blood pressure is checked because cardiovascular effects are a known consideration with ketamine.
- Full medication review — your clinician reviews everything you take, including sedatives and mood stabilizers, and decides whether anything should be adjusted. Never change a psychiatric medication on your own.
- Substance use and psychiatric history — active psychosis, mania, and untreated substance use disorders are screened for.
- Intention-setting and logistics — what you hope to work on, plus a confirmed ride home.
Practical readiness matters more than people expect. Our guide to preparing for your first ketamine session covers what to eat, what to bring, and how to set up the day so you aren't rushing afterward.
Phase 2: The Dosing Session — What Is the Therapist Doing?
During dosing, the therapist's job is mostly quiet, attentive presence rather than active conversation. Talking is generally minimized while effects peak, because the psychological work is scheduled for afterward.
A typical monitored medicine session involves:
- A private room with a reclining chair, blanket, and low lighting
- Eye shades and a curated music playlist, used in many protocols to keep attention inward
- Periodic blood pressure and vital sign checks throughout
- A clinician within arm's reach for the full session and the recovery period
Session length depends on the route and the protocol your clinician sets. For the FDA-approved esketamine nasal spray, the label requires administration under the direct observation of a healthcare provider, with monitoring of the patient for at least two hours afterward (SPRAVATO prescribing information). IV protocols use a weight-based dose infused over a set period, with a recovery window before discharge.

Phase 3: Integration — Why Is This the Part People Skip?
Integration is the therapy session held shortly after dosing, where whatever surfaced gets turned into something usable — a changed habit, a boundary, a conversation, a plan. It is also the phase people most often drop, usually because it costs extra time and money and doesn't feel as dramatic as the medicine session.
Integration refers to structured psychological work in the days following a dosing session, aimed at translating insight into concrete behavior change.
The rationale is straightforward: if the post-dose period is a window of increased plasticity, then leaving it empty wastes the part of the protocol that therapy was scheduled to use. Programs typically book integration within a few days of dosing while the material is fresh.
⚠️ Skipping integration is a common shortcut, and it removes the therapeutic half of ketamine-assisted psychotherapy. If budget is tight, discuss a reduced integration schedule with your clinician rather than dropping it entirely.
IV Infusion, Esketamine, or KAP — Which Route Fits Which Patient?
Route selection usually comes down to three practical factors: regulatory status, insurance, and how much dose control your clinician wants. KAP isn't a fourth route — it's a therapy structure layered onto either medicine route.
| IV ketamine infusion | Esketamine nasal spray (SPRAVATO) | At-home oral ketamine | |
|---|---|---|---|
| Regulatory status | Ketamine is FDA-approved as an anesthetic; use for depression is off-label | FDA-approved for treatment-resistant depression in adults with an oral antidepressant | Compounded and prescribed off-label |
| Where it's given | In-clinic, medically supervised | In a certified healthcare setting under direct observation of a provider | Self-administered at home |
| Monitoring requirement | Vitals monitored during infusion and recovery | Label requires observation and monitoring for at least two hours after dosing | No in-person clinical monitoring |
| Dose control | Precise, weight-based, adjustable mid-session | Fixed device doses per the label | Least controlled; absorption varies |
| Insurance | Commonly self-pay | Often billed to insurance, typically with prior authorization | Varies; usually self-pay |
| Depth of study for depression | Substantial published trial literature, mostly short-term | Reviewed by the FDA for its approved indication | Least studied of the three |
Sources: SPRAVATO prescribing information and StatPearls, as of September 2026.
A few honest distinctions worth holding onto:
- If insurance coverage is the deciding factor, esketamine is the route with an FDA-approved indication, which is why it's the one usually run through benefits. The full Spravato esketamine guide covers the certification and observation requirements in detail.
- If precise dosing control matters, IV allows a clinician to titrate during the session in a way a fixed-dose device cannot.
- If you want therapy built in, KAP can be structured around either route — that's a scheduling and staffing decision, not a pharmacological one.
Locally, both supervised infusion and esketamine pathways exist in the Treasure Valley, and our own ketamine for depression in Boise and Eagle service page outlines which conditions we evaluate and how the consultation works.
Key takeaway: IV offers dose control, esketamine offers FDA approval and an insurance pathway, and at-home oral offers convenience with the thinnest evidence and no in-person monitoring.
Who Qualifies for Ketamine Treatment for Depression?
Most programs evaluating ketamine treatment for depression screen for adults with major depressive disorder or bipolar depression who have already tried at least two antidepressants without adequate response — the treatment-resistant population reflected in the esketamine label (SPRAVATO prescribing information). Candidacy is always decided by a clinician in a consultation, never by a website.
Typical inclusion factors:
- Adult age — 18 or older for standard protocols
- A documented diagnosis — major depressive disorder or bipolar depression, not undifferentiated stress
- Prior antidepressant trials — at least two adequate trials, documented where possible
- Stable cardiovascular status — blood pressure within a range your clinician considers acceptable
- A concurrent care plan — a prescribing psychiatrist, therapist, or primary care provider who stays in the loop
Contraindication: a condition that makes a treatment inadvisable or unsafe for a specific person. The esketamine label lists contraindications including aneurysmal vascular disease, arteriovenous malformation, a history of intracerebral hemorrhage, and hypersensitivity to esketamine or ketamine (SPRAVATO prescribing information). Clinicians also screen carefully for conditions where sedation, dissociation, or blood pressure elevation pose added risk.
Relative cautions your clinician will weigh:
- Uncontrolled or poorly controlled high blood pressure
- Active psychosis or current manic symptoms
- Untreated substance use disorder, particularly involving ketamine or other dissociatives
- Pregnancy or breastfeeding
- Significant liver disease or complex cardiac history
⚠️ Being declined isn't a dead end. Screening exists to route people toward the treatment that fits their physiology and diagnosis. If you're mapping out what else exists locally, our overview of treatment-resistant depression options in Idaho walks through the alternatives.
If you take a benzodiazepine or lamotrigine, mention it early. Clinicians commonly review these during screening and may adjust timing — but only a prescriber should make that call.
How Long Does Relief Last, and What Does Maintenance Look Like?
Durability is where honest clinics and marketing copy part ways. Ketamine protocols are built around the expectation that an initial series is followed by ongoing monitoring, because change is not assumed to be permanent after one course. How long any individual's response lasts varies, and published follow-up data beyond the first year remains limited.
A conventional course looks like this in practice:
- Induction series — commonly around six supervised sessions across roughly two to three weeks, though protocols vary by clinic and diagnosis.
- Structured reassessment — repeat PHQ-9 or similar scoring at set points, compared against your baseline from the preparation phase.
- Maintenance or booster sessions — scheduled by symptom scores and clinician judgment rather than a fixed calendar, with intervals that differ widely between patients.
- Ongoing standard care — therapy, existing medications, sleep, and medical follow-up continue throughout. Ketamine protocols are additive, not a replacement.

Two habits make maintenance decisions less guesswork:
- Track scores, not vibes. Standardized scales catch drift that memory smooths over.
- Log what changed behaviorally. Sleep, appetite, work attendance, and social contact are observable; mood alone is slippery.
What the research cannot yet tell you is how many people sustain response over multiple years, or which maintenance interval is optimal. Our overview of the long-term effects of ketamine therapy covers what's known and what isn't in more depth.
Key takeaway: Plan for an induction series plus ongoing monitoring, not a one-time fix — and expect your clinician to make maintenance decisions from tracked symptom scores rather than a fixed schedule.
What Are the Limits of the Evidence Right Now?
The limitations are real, and no clinic should hide them. Anyone presenting ketamine as settled science is overselling a field that is still maturing.
The main caveats worth knowing:
- Trials are often small and short. Much of the depression literature involves modest sample sizes and follow-up windows measured in weeks, which limits how confidently results generalize.
- Blinding is genuinely hard. Ketamine produces noticeable dissociative and perceptual effects (StatPearls), so participants can often guess whether they received the drug. That complicates placebo comparison in ways researchers openly debate.
- Long-term data is thin. Multi-year safety and durability evidence for repeated dosing in psychiatric use is far less developed than for older antidepressants.
- At-home oral dosing is the least supported option. The FDA-approved esketamine product must be administered under a healthcare provider's direct observation with a post-dose monitoring period (SPRAVATO prescribing information) — a standard unsupervised home dosing doesn't meet.
- KAP-versus-medicine-alone comparisons are limited. The therapy-pairing rationale is sound and widely used, but rigorous head-to-head evidence is still developing.
None of this means the treatment lacks merit — a regulator reviewed controlled data and approved esketamine for a defined population. It means claims should be sized to the evidence. Known risks, including cardiovascular effects, dissociation, and bladder-related concerns with long-term heavy use, are documented in the clinical literature and belong in your consultation conversation. For a fuller treatment of that side of the ledger, see a closer look at ketamine safety and risk.
⚠️ Be skeptical of any provider quoting a precise success rate without naming the study, the population, and the timepoint. Ask for the citation.
Still weighing whether the evidence applies to you? Talk it through with our Boise and Eagle team — request a ketamine consultation and get a straight answer about candidacy, protocol, and cost. A consultation is also where you get a firm per-session quote and, for esketamine, a benefits check before you commit to anything — national cost ranges vary enough that only a direct quote is useful. Our fuller breakdown of ketamine therapy costs explains what typically drives the difference between routes.
Frequently Asked Questions
How many ketamine sessions are needed for depression?
Most protocols start with an induction series of roughly six supervised sessions over two to three weeks, followed by reassessment. After that, maintenance sessions are scheduled based on tracked symptom scores and clinician judgment rather than a fixed number. The exact count varies by diagnosis, route, and how you respond. Your clinician sets the plan at consultation and adjusts it as your scores change.
Can I drive after a ketamine session?
No — arrange a ride home in advance. For the FDA-approved esketamine nasal spray, the label instructs that patients should not drive or operate machinery until the next day following a restful sleep (SPRAVATO prescribing information). Supervised IV protocols apply the same caution. It's also standard advice to avoid signing legal or financial documents for the rest of the day.
Does ketamine work if SSRIs never did?
That's precisely the population studied. The esketamine indication covers adults with treatment-resistant depression, meaning inadequate response to prior antidepressants (SPRAVATO prescribing information), and ketamine acts on glutamate rather than serotonin (StatPearls). Whether it helps you specifically is decided in a clinical evaluation. Individual results vary, and no outcome is guaranteed.
Do I have to stop my current antidepressant?
Usually not. The FDA-approved esketamine indication is for use in combination with an oral antidepressant (SPRAVATO prescribing information), so continuing your regimen is often part of the plan. Some medications — benzodiazepines and certain mood stabilizers among them — get reviewed and sometimes adjusted. Never change a psychiatric medication without your prescriber directing it.
Is ketamine-assisted psychotherapy better than infusions alone?
The rationale for adding therapy is that the post-dose period may be a window of increased neuroplasticity, making structured psychological work more useful then. Rigorous head-to-head trials comparing KAP against medicine alone are still limited, so this is a reasoned clinical approach rather than a settled finding. Discuss with your clinician whether the added time and cost fit your goals.
Summary
Ketamine treatment for depression rests on a real but narrow evidence base: an FDA-approved esketamine nasal spray for treatment-resistant depression in adults, a well-described glutamate mechanism that differs fundamentally from SSRIs, and a body of off-label IV research that is meaningful but mostly short-term. Ketamine-assisted psychotherapy layers preparation and integration around the medicine session on the reasoning that plasticity shouldn't go unused. Candidacy is decided by screening, durability requires maintenance planning, and the honest caveats — small trials, difficult blinding, thin long-term data — belong in the conversation alongside the promise. If you're in Boise or Eagle and want to know whether any of this applies to your situation, a consultation is where that gets answered specifically.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.