Ketamine Side Effects After 6 Months of Treatment
Zora Neuro Spa Editorial · September 17, 2026

Most of what you'll read online about long-term ketamine side effects describes recreational use, not supervised medical treatment — and the two look nothing alike. That distinction matters if you live in Boise, Eagle, or Caldwell and you're weighing six months or more of care. This guide separates the abuse-pattern data from the clinical data, and shows what responsible monitoring should catch.
Quick Answer: Does Long-Term Ketamine Therapy Cause Lasting Side Effects?
At sub-anesthetic doses given in a clinic, the effects patients feel — dissociation, nausea, dizziness, a brief rise in blood pressure — are short-lived and monitored until they settle. The serious long-term harms in the literature, including bladder damage and cognitive problems, are documented mainly in frequent high-dose recreational use, not in spaced therapeutic series (StatPearls). Maintenance patients still need ongoing checks.
Ketamine maintenance therapy is the phase after an initial induction series, when doses are spaced out over weeks or months and adjusted based on symptom scores, vital signs, and side effect reports.
TL;DR
- The scary long-term data comes from a completely different dosing pattern than clinical care. Compare recreational, at-home, and clinical dosing
- Bladder problems are real and well documented, but they cluster in heavy frequent users — and the warning signs are easy to catch early. Read the bladder evidence
- Memory concerns trace to chronic abuse studies; short-term dissociation during a session is a different thing entirely. See what the cognition research separates
- Spacing doses is the main structural defense against tolerance and escalation. Understand tolerance and dependence risk
- Good clinics track four things on a schedule: symptoms, blood pressure, urinary health, and dose intervals. See what monitoring should include
In This Article
- Why Do Recreational and Clinical Ketamine Data Get Confused?
- What Happens in the First 24 Hours After an Infusion?
- How Real Is the Bladder Risk With Long-Term Ketamine?
- Does Long-Term Ketamine Affect Memory or Cognition?
- Can You Build Tolerance or Become Dependent?
- Which Ketamine Side Effects Should Prompt a Call to Your Clinic?
- What Does Responsible Long-Term Monitoring Look Like?
- How Do Long-Term Risks Compare to Long-Term Antidepressants?
Why Do Recreational and Clinical Ketamine Data Get Confused?
Because the most widely circulated warnings describe people who use ketamine repeatedly, in uncontrolled amounts, without medical oversight — and those warnings rarely mention dose at all. The DEA's public ketamine fact sheet, accessed September 2026, lists effects including agitation, cognitive difficulties, unconsciousness, and amnesia. It presents those effects in the context of drug abuse, without clinical dosing detail or citations.
That framing is accurate for what it covers. It just doesn't describe a monitored infusion appointment.
Sub-anesthetic dosing refers to ketamine given at levels well below those used to induce surgical anesthesia. In depression protocols, the drug is infused slowly over roughly 40 minutes rather than taken in repeated self-administered doses (StatPearls). A therapeutic course involves a handful of separated sessions over a few weeks — an entirely different exposure pattern from daily use.
The exposure pattern is what drives long-term risk. Here's how the four common routes compare.
| Recreational use | At-home oral ketamine | Esketamine nasal spray | Supervised IV infusion | |
|---|---|---|---|---|
| Dose control | None — self-determined | Prescribed, but self-administered | Fixed device doses, per FDA label | Weight-based, clinician-controlled |
| Frequency | Can be daily or repeated in a session | Set by prescriber, unsupervised in practice | Scheduled clinic visits | Scheduled clinic visits |
| Setting | Unregulated | Home | Certified healthcare setting | Clinic treatment room |
| Monitoring | None | Remote check-ins | On-site observation required under REMS (FDA label) | Vitals and observation throughout |
| Where serious long-term harm is documented | Yes — bladder and cognitive effects reported with chronic abuse (StatPearls) | Escalation risk is the concern | Class-related risks monitored per label | Rare in published therapeutic reports |
The Oxford Health NHS Interventional Psychiatry Service's patient page on risks and benefits, accessed September 2026, takes a similar approach — telling treatment patients which symptoms to report rather than describing abuse outcomes.
Key takeaway: Long-term risk tracks with how often and how much ketamine is taken, not simply with whether it's taken at all.
If you're still mapping out the basics of cost, screening, and appointment structure, our ketamine safety and process FAQ answers those separately.
What Happens in the First 24 Hours After an Infusion?
The effects you feel are concentrated in the session itself and the observation window right after. Dissociation, nausea, dizziness, blurred vision, and a temporary rise in blood pressure are the commonly listed reactions (StatPearls). For esketamine, the FDA label reports that dissociative and sedative effects generally resolve within about 1.5 hours after dosing, which is why on-site observation is required (FDA label).
Mild grogginess or fatigue can carry into the evening. That's the main reason for the no-driving rule.
Same-day aftercare checklist:
- No driving — the FDA label instructs esketamine patients not to drive until the next day after restful sleep; infusion clinics apply the same caution (FDA label)
- Arrange a ride — plan this before the appointment, especially if you're traveling in from Caldwell or Nampa
- Follow fasting instructions — your clinic will give you a pre-treatment window to reduce nausea risk
- Keep the evening light — no major decisions, no machinery, no alcohol
- Write down what you felt — short notes help your provider adjust the next session
Every one of these is about the hours around treatment, not the months after. For a detailed breakdown of how long each side effect actually lasts, we cover the minute-by-minute timeline separately.
How Real Is the Bladder Risk With Long-Term Ketamine?
Ketamine-induced bladder injury is a genuine, documented complication — and it is strongly associated with frequent, heavy use. Urinary tract and bladder toxicity appears in the clinical literature on chronic ketamine exposure (StatPearls). The FDA's SPRAVATO label also directs prescribers to monitor patients for urinary tract and bladder symptoms during treatment (FDA label).
Ketamine-induced uropathy refers to inflammation and damage to the bladder lining linked to chronic ketamine exposure, producing pain and disruptive changes in urination.
Two things are worth holding at once. The risk is real enough that regulators require monitoring. And it has been reported overwhelmingly in patterns of use far more frequent than a spaced clinical series.
What are the early warning signs?
The Oxford Health NHS Interventional Psychiatry Service patient page, accessed September 2026, tells patients that the main symptoms of ketamine-related bladder damage are lower abdominal pain, pain passing urine, and needing to pass urine more often — and to report them.
⚠️ Report these immediately, don't wait for your next appointment: lower abdominal or pelvic pain, burning or pain when urinating, urinating far more often than usual, sudden urgency, or any blood in the urine. Early reporting is what allows a clinician to pause or adjust treatment before symptoms progress.
This is also where dosing structure matters most. A monitored series has a clinician recording every dose and every interval. Unsupervised access — refilling on your own schedule, or increasing the amount because a dose felt weaker — removes exactly the control that keeps cumulative exposure low.
Why does supervision change the picture?
Three structural reasons:
- Total exposure stays low and documented — doses are spaced, and the log is written down rather than remembered
- Symptoms get asked about, not just reported — a scheduled urinary check-in catches what patients often dismiss as a minor bladder infection
- Escalation isn't possible between visits — the clinic controls the supply and the interval
That's the core argument for supervised IV ketamine therapy over informal arrangements: not that infusions are risk-free, but that the specific behavior most linked to bladder harm — frequent self-directed dosing — is structurally prevented.
Key takeaway: Bladder toxicity is the most credible long-term concern with ketamine, and the most preventable, because the early symptoms are obvious and treatment can be paused.
Does Long-Term Ketamine Affect Memory or Cognition?
Cognitive concerns in the ketamine literature come overwhelmingly from studies of chronic recreational use, where repeated high-dose exposure has been associated with memory and attention problems (StatPearls). The DEA fact sheet, accessed September 2026, similarly lists cognitive difficulties and amnesia among effects of abuse. Neither describes a spaced therapeutic protocol.
What patients in treatment actually experience during a session is a different phenomenon.
Dissociation is a temporary change in perception during and shortly after dosing — a sense of distance from your body, altered time, or a dreamlike quality. The FDA label reports that these effects generally resolve within about 1.5 hours of dosing (FDA label). Feeling foggy for an hour is not the same as lasting cognitive change.

How do clinicians actually check for this?
Cognition isn't assumed to be fine — it's assessed. The FDA label for esketamine includes cognitive impairment among the warnings prescribers must consider, which means cognitive status is part of ongoing evaluation rather than a one-time question (FDA label).
In practice, a thorough long-term program will:
- Ask about memory and concentration at review appointments, not only at intake
- Separate treatment effects from depression itself — concentration difficulty is a documented symptom of depression (NIMH)
- Track changes over time using consistent questions rather than impressions
- Reassess if anything worsens, including pausing or spacing doses further apart
That second point gets missed a lot. Brain fog is common in untreated depression, so attributing it automatically to the medication can send you down the wrong path. Results and experiences vary between individuals, and whether cognition is stable enough to continue is a clinical judgment made with your provider.
Key takeaway: The cognitive evidence that worries people comes from chronic abuse research; at clinical doses, transient dissociation and lasting impairment are separate questions that should be tracked separately.
Can You Build Tolerance or Become Dependent?
Ketamine has recognized abuse and misuse potential, which is why esketamine is dispensed under a Risk Evaluation and Mitigation Strategy (REMS) program with required on-site observation (FDA label). Spacing doses and keeping administration inside a clinic is the primary structural safeguard.
Three different things often get collapsed into one worry:
- Physiological tolerance — needing more of a drug for the same physical effect, which is associated with frequent repeated dosing
- Psychological craving — wanting the experience itself rather than the clinical outcome
- Escalation — quietly increasing frequency or amount outside the agreed plan
A booster infusion is a single maintenance dose given after an induction series, scheduled at an interval your clinician sets and revises based on how you're doing.
The interval is the whole point. Boosters are deliberately spaced weeks or months apart, and that spacing is what distinguishes maintenance therapy from the daily patterns associated with harm. Your provider individualizes it — there is no universal number, and the plan should be reassessed rather than set once and forgotten.
⚠️ Where escalation risk concentrates: unsupervised oral dosing at home. When the medication is in your cabinet and the schedule is self-managed, there is no external check on frequency. If you're comparing formats, read our breakdown of at-home versus in-clinic ketamine dosing before deciding.
What should you tell your clinician?
Be direct about all of it. Say so if you find yourself counting days to the next session, if you've wondered about getting ketamine elsewhere, or if a dose felt weaker than before. None of these end your treatment automatically. They change how it's structured — usually through longer intervals, a revised dose, or added psychotherapy support.
Anyone with a personal or family history of substance use disorder should raise it at screening, in Boise, Eagle, Caldwell, or anywhere else. It informs the plan rather than disqualifying you.
Which Ketamine Side Effects Should Prompt a Call to Your Clinic?
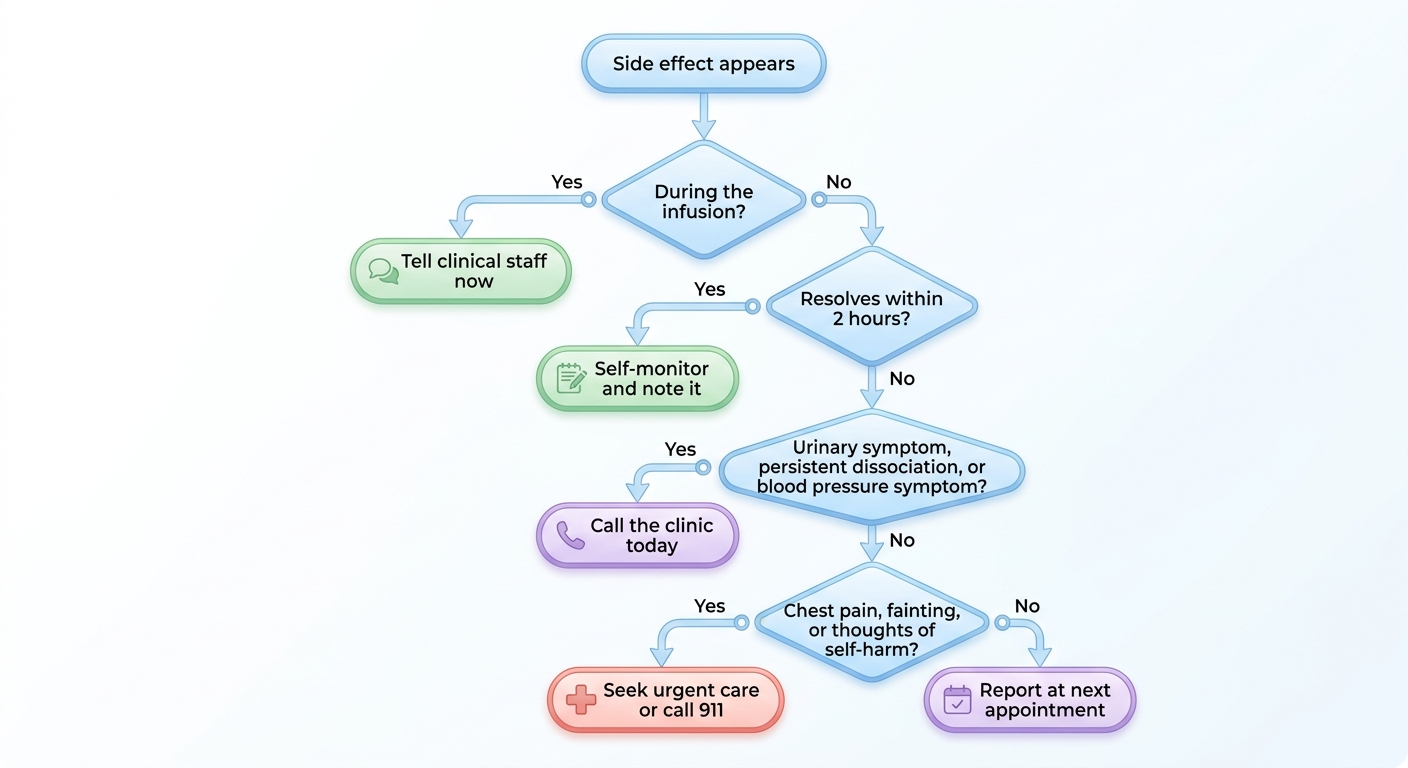
Call promptly for any urinary symptom, any blood pressure symptom lasting past treatment day, worsening mood or thoughts of self-harm, or dissociation that hasn't cleared by the next morning. Most ketamine side effects resolve during the observation period — the ones that don't are the ones worth a phone call.
Use time thresholds, not guesswork:
- During the infusion — tell your nurse immediately about chest discomfort, severe nausea, or distressing anxiety; these are managed in the room
- Within 2 hours after — dissociation, dizziness, and grogginess easing in this window is expected; report it if they aren't easing
- Same evening — persistent vomiting, headache with visual changes, or a racing heart warrants a call
- Next morning — still foggy, still dissociated, or unable to function normally? Call before your next appointment
- Any time — burning urination, urinary urgency or frequency, pelvic pain, or blood in urine
- Urgent care or 911 — chest pain, trouble breathing, fainting, or a thought of harming yourself
One more thing patients under-report: mood getting worse. Depression can shift during any course of treatment, and clinicians want to know early (NIMH). It is not a sign that you've failed the treatment.
If you're unsure whether something counts, it counts. Talk to the Boise and Eagle care team rather than waiting it out.
What Does Responsible Long-Term Monitoring Look Like?
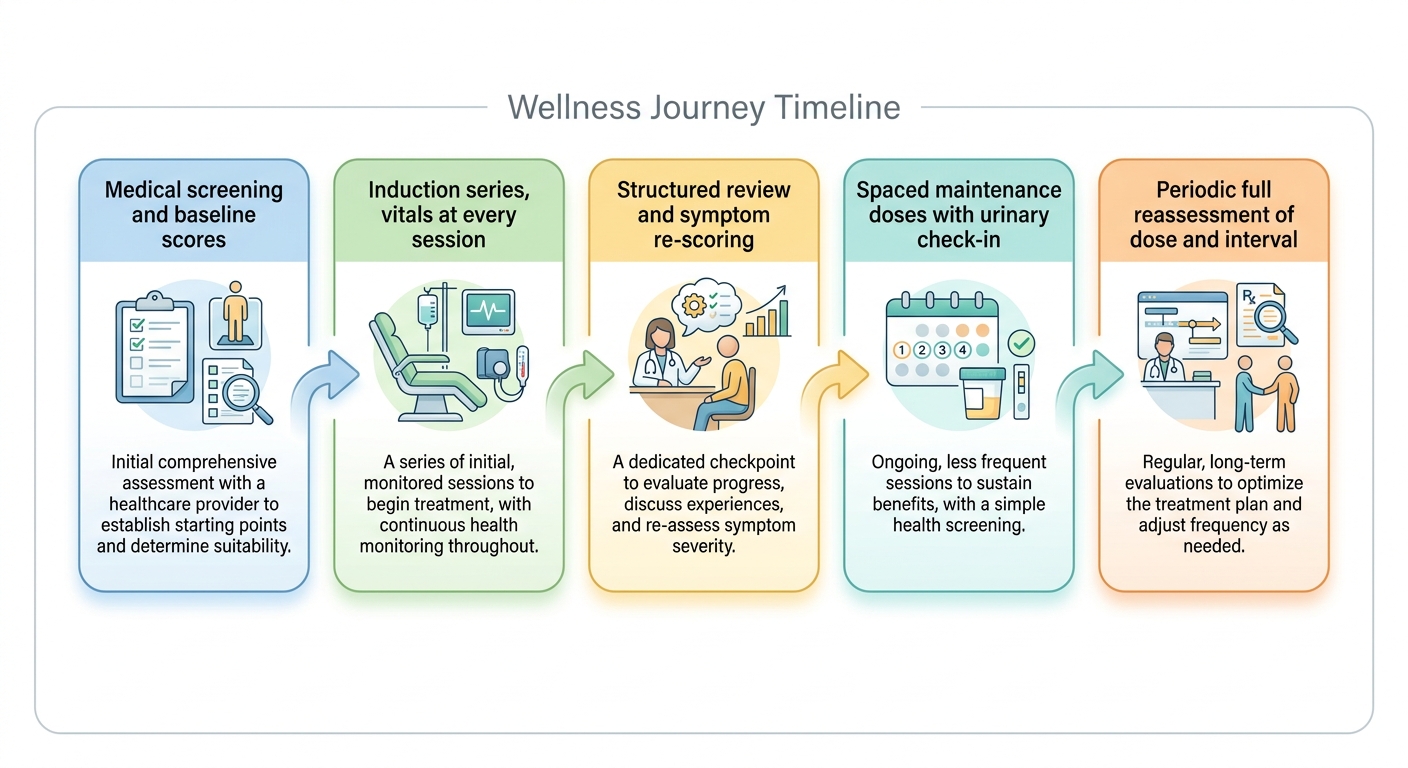
A serious maintenance program tracks four things on a fixed schedule: validated symptom scores, blood pressure at every visit, a urinary symptom check-in at regular intervals, and a written dose-and-interval log. If a clinic can't describe all four, ask why.
Here's what each one does:
- Symptom scores — instruments like the PHQ-9, GAD-7, and PCL-5 give a consistent measure across months instead of relying on memory
- Blood pressure and vitals — checked before, during, and after dosing, since transient blood pressure increases are a known effect (StatPearls)
- Urinary check-in — a direct question at scheduled reviews, because patients rarely volunteer these symptoms
- Dose and interval log — the record that makes cumulative exposure visible rather than approximate
What questions should you ask a clinic?
Bring these to any consultation, whether you're in Eagle, Boise, or driving in from Caldwell:
- Who is physically present during my infusion, and what are their credentials?
- What vitals do you record, and how often?
- How do you screen for bladder and urinary symptoms over time?
- How do you decide when to space boosters further apart or stop?
- What happens if I report a side effect between appointments?
A program that answers all five specifically is doing the work. One that answers vaguely is asking you to trust an outcome instead of a process. You can see how our own structure is organized across ketamine therapy services in Boise and Eagle.
Key takeaway: Long-term safety is a monitoring practice, not a property of the drug — the questions above tell you whether a clinic has one.
How Do Long-Term Risks Compare to Long-Term Antidepressants?
The trade-off is different in shape, not uniformly better. Oral antidepressants involve continuous daily exposure over years; ketamine involves intermittent exposure with its own monitoring requirements. NIMH notes that antidepressants can cause side effects, and that people respond differently to different medications (NIMH).
| SSRIs / SNRIs | Esketamine nasal spray | IV ketamine | |
|---|---|---|---|
| Exposure pattern | Daily, continuous, often years | Scheduled clinic doses | Scheduled clinic doses |
| Commonly reported persistent effects | Weight, sexual, and sleep effects are commonly reported by patients | Dissociation and sedation around dosing; label-directed bladder monitoring (FDA label) | Dissociation and blood pressure changes around dosing; bladder monitoring over time |
| Stopping | Tapering is typically planned with a prescriber | Discussed with prescriber; dosing already intermittent | Dosing already intermittent |
| Monitoring burden | Periodic prescriber visits | On-site observation required at every dose under REMS (FDA label) | Vitals and observation at every session |
The honest summary: daily medication trades a lower per-dose intensity for a much longer total exposure. Ketamine trades a more involved appointment for far fewer exposure days per year. Neither profile is automatically safer, and which one fits depends on your medical history, prior responses, and preferences — a decision for a clinical consultation, not an article.
If you're currently on an antidepressant and considering a change, our guide to weighing antidepressant side effects covers that comparison in more depth.
Summary
The long term effects of ketamine therapy look very different depending on whose data you're reading. Chronic high-frequency recreational use is genuinely associated with bladder damage and cognitive problems (StatPearls). Supervised sub-anesthetic dosing is a different exposure pattern, with side effects concentrated in the session and observation window.
That doesn't make monitoring optional — the FDA requires observation and bladder symptom checks for esketamine for good reason (FDA label). The practical takeaway is that most ketamine side effects worth worrying about over six months announce themselves early and clearly, if someone is asking the right questions on a schedule. Results and suitability vary from person to person and are determined in a medical consultation.
Frequently Asked Questions
How many ketamine infusions are considered safe over a year?
There's no universal number. Most programs begin with an induction series of several sessions over a few weeks, then move to spaced maintenance doses at an interval set individually. The right total depends on your response, your medical history, and ongoing monitoring — it should be reassessed at review appointments rather than fixed in advance.
Does ketamine therapy cause permanent brain changes?
The brain changes discussed in ketamine research are synaptic, and they are the reason researchers study the drug for mood disorders in the first place. Lasting cognitive impairment is documented in chronic abuse contexts, not at clinical doses (StatPearls). For the mechanism, see our explainer on how ketamine drives neuroplasticity.
Can I drink alcohol during a course of ketamine therapy?
Clinics generally advise avoiding alcohol around treatment days and limiting it during an induction series. Two reasons: alcohol interacts with sedation, and it makes side effects harder to attribute accurately. If you notice grogginess the day after a session, your provider needs to know whether alcohol was involved. Discuss your specific situation at screening.
Are long-term side effects different with Spravato than IV ketamine?
The main structural difference is supervision requirements. Esketamine is administered under a REMS program with required on-site observation after each dose, per the FDA label (FDA label). The bladder and dissociation considerations are class-related and monitored with both routes. Which format suits you is a consultation decision.
What if side effects make me want to stop treatment?
Tell your clinician before you stop. Tolerability issues are frequently addressed by adjusting the dose, slowing the infusion rate, or adding anti-nausea premedication. Stopping is always your choice, but many ketamine infusion side effects that feel intolerable at one dose are manageable at another. Individual responses vary.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.