Ketamine Side Effects: What Lasts Minutes vs Months
Zora Neuro Spa Editorial · September 2, 2026
If you're researching ketamine side effects before a first infusion, the real question underneath is usually simpler: how long will this feel strange, and could anything stick around? This guide sorts side effects by duration — what fades in minutes, what lingers hours, and what long-term risks the evidence actually supports. It's written for people in the Boise and Eagle area weighing monitored ketamine therapy for depression, PTSD, chronic pain, or migraine.
Quick Answer: How Long Do Ketamine Side Effects Last?
Most side effects from a monitored infusion — dissociation, dizziness, nausea, blurred vision, and a temporary blood pressure rise — peak during the drip and settle within roughly 30 to 90 minutes after it ends. Mild grogginess or a dull headache can linger the rest of the day. Serious long-term concerns are documented mainly in frequent, high-dose, non-medical use rather than spaced clinical dosing.
Sub-anesthetic ketamine is a dose far below what's used to induce surgical anesthesia, delivered by slow IV drip with continuous vital-sign monitoring. For depression, doses around 0.5 mg/kg infused over about 40 minutes are described in the clinical literature (StatPearls).
TL;DR
- Short-term effects are same-day events. The strange, floaty part is measured in minutes, not days. See the four-phase side effect timeline
- Route changes the experience. IV, intranasal esketamine, and oral dosing differ in peak window and monitoring requirements. Compare side effects by delivery method
- Effects often ease across a treatment series. Many patients describe the first one or two sessions as the most disorienting. Read what a depression series involves
- Long-term harms track with misuse, not monitored care. Bladder damage and cognitive concerns come overwhelmingly from frequent high-dose exposure. Review the long-term evidence
- A few symptoms warrant a same-day phone call. Urinary pain, chest pain, or confusion past 24 hours are not "wait and see" items. Check the red-flag symptom table
In This Article
- What Does the Ketamine Side Effect Timeline Actually Look Like?
- Which Side Effects Are Specific to IV Ketamine Infusions?
- What Side Effects Show Up During a Depression Treatment Series?
- Are There Long-Term Effects of Ketamine Therapy?
- Who Is at Higher Risk for Ketamine Side Effects?
- How Do Clinics Actually Reduce Side Effects?
- What Symptoms Should You Report Right Away?
- Frequently Asked Questions
What Does the Ketamine Side Effect Timeline Actually Look Like?
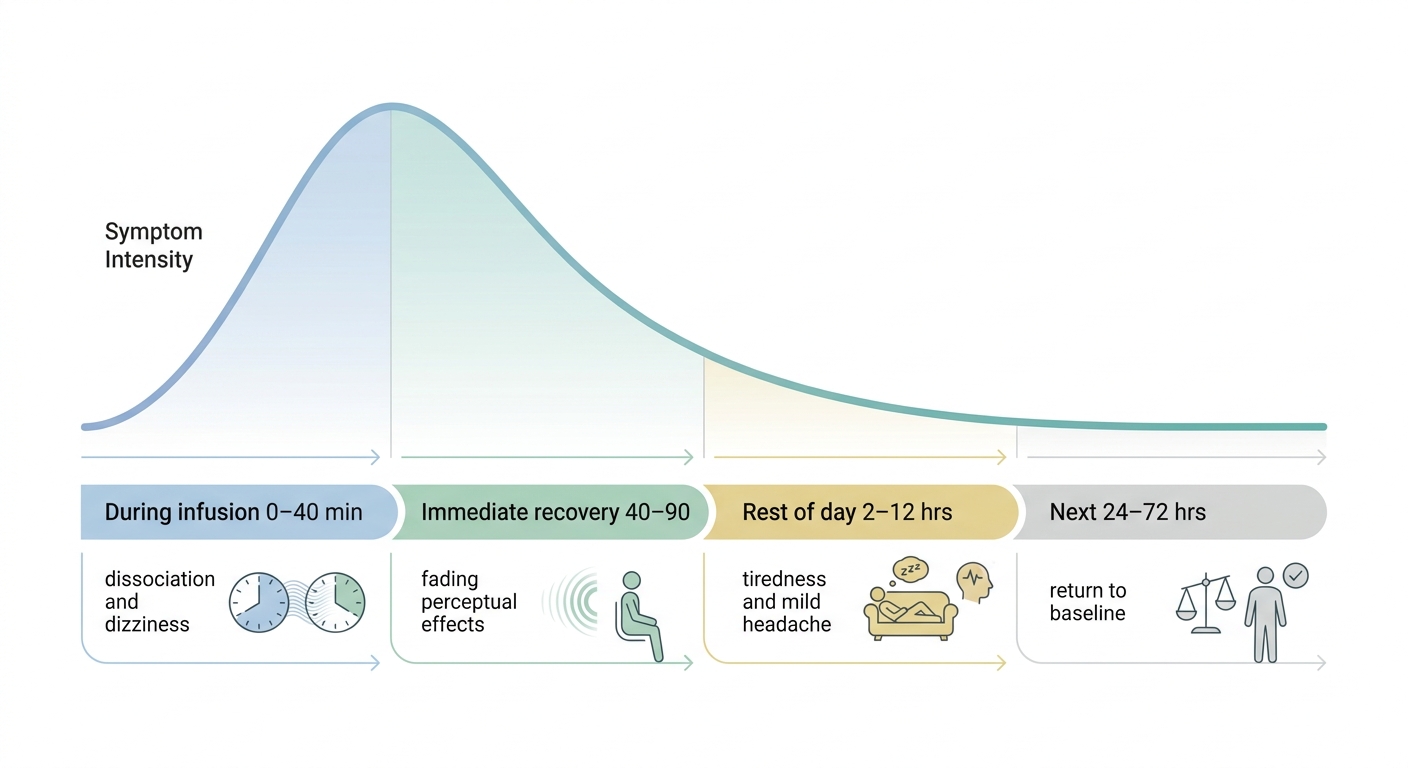
Side effects follow a fairly predictable curve: they rise with the drug level, peak near the end of dosing, then fall off as the body clears it. Thinking in phases is more useful than reading an alphabetical list of symptoms.
Phase 1 — During the infusion (roughly 0–40 minutes). This is where the dissociative effects live. Dissociation refers to a temporary sense of distance from your body, thoughts, or surroundings — time may feel stretched, and sounds or colors may seem altered. Dizziness, blurred or double vision, and a mild rise in blood pressure and heart rate also cluster here. The esketamine prescribing information notes that blood pressure increases tend to peak around 40 minutes after dosing (FDA label).
Phase 2 — Immediate recovery (about 40–90 minutes). The drip stops and the drug clears quickly. Most people describe the odd perceptual effects fading first, followed by steadier balance. Nausea, if it appears, is usually managed here.
Phase 3 — Rest of the day (2–12 hours). What remains is typically mild: tiredness, a heavy-limbed feeling, a low-grade headache, or a slightly "off" sense of coordination. This is why driving is off the table for the remainder of the day.
Phase 4 — Next 24–72 hours. Most people report feeling physically back to baseline by the next morning. Some describe vivid dreams or unusually light sleep the first night.
If you want a fuller picture of the subjective experience rather than the symptom list, our guide to what a ketamine infusion actually feels like walks through it session by session. Frequency varies between individuals — not everyone experiences every effect, and intensity depends on dose, body weight, and personal sensitivity.
Key takeaway: Acute ketamine side effects are front-loaded into the infusion itself and taper within about an hour and a half of the drip ending.
Which Side Effects Are Specific to IV Ketamine Infusions?
Intravenous delivery produces the most controllable drug levels, because it bypasses the absorption variability that comes with swallowing or absorbing a medication through tissue (StatPearls). That predictability cuts both ways: effects during the drip can feel more pronounced, but a clinician can slow or stop the infusion in real time.
Effects most tied to the IV route include:
- Transient cardiovascular changes — a temporary rise in blood pressure and heart rate, which is why cuff readings are taken throughout.
- Nystagmus — Nystagmus is brief involuntary rapid eye movement that resolves as the drug clears. It looks alarming to a bystander and is usually unnoticed by the patient.
- Infusion-site discomfort — mild stinging or tenderness where the catheter sits.
- Dose-dependent dissociation — the higher the level in the bloodstream, the more pronounced the perceptual shift.
Here's how the common delivery routes compare on the practical points that shape your day:
| Factor | IV infusion | Intranasal esketamine (SPRAVATO) | Oral / sublingual ketamine |
|---|---|---|---|
| Delivery | Slow drip in-clinic, commonly ~40 min for depression protocols (StatPearls) | Self-administered nasal spray under supervision (FDA label) | Taken by mouth; absorption varies by individual |
| Route-specific effects | Infusion-site discomfort; dose adjusted mid-session | Nasal discomfort, taste changes, vertigo listed among adverse reactions (FDA label) | Bitterness and nausea are commonly discussed; less predictable levels |
| In-office observation | Continuous monitoring through recovery | At least 2 hours post-dose, per the label (FDA label) | Varies by program |
| Driving | Not for the remainder of the day | Not until the next day after restful sleep (FDA label) | Follow prescriber instruction |
| Dose control mid-session | Yes — rate can be changed | Fixed per-device dosing | No |
The tradeoff most people care about: with IV ketamine therapy, a clinician is watching vitals and can respond while you're still in the chair. That's the practical difference between an effect being managed and an effect being endured.
Key takeaway: IV infusions concentrate side effects into a supervised window where dose and rate can be adjusted on the spot.
What Side Effects Show Up During a Depression Treatment Series?
Across a standard induction series of multiple infusions spaced over a few weeks, patients frequently describe the first one or two sessions as the most disorienting, with subsequent sessions feeling more familiar., with subsequent sessions feeling more familiar. Nothing about that pattern is guaranteed; response and tolerance vary between individuals, and your clinician calibrates dose accordingly.

Beyond the physical effects already covered, a depression series brings a few experiences worth naming in advance:
- Emotional rawness after a session. Some patients describe feeling unusually open or tearful in the hours afterward.
- Vivid dreams or altered sleep on the night of treatment.
- Transient anxiety spikes. Anxiety is listed among adverse reactions in the esketamine prescribing information (FDA label).
- A dip a few days later. Some people report a low stretch several days after a session. Discuss this pattern with your provider rather than interpreting it alone.
- Dissociation intolerance. A small number of people find the dissociative experience unpleasant enough that they and their clinician change the plan.
Depression itself is a serious medical condition with several established treatment paths, and ketamine is one option a clinician may consider when others haven't worked (NIMH). Suitability is determined in a clinical consultation, not from an article.
For how a series is structured locally — screening, spacing, and follow-up — see our page on ketamine for depression in Boise and Eagle.
Are There Long-Term Effects of Ketamine Therapy?
The well-documented long-term harms — bladder injury, cognitive changes, and dependence — appear overwhelmingly in the context of frequent, high-dose, non-medical ketamine use rather than spaced medical dosing. That distinction is the single most important thing to understand when you read alarming headlines. Our deeper breakdown of the long-term effects of ketamine therapy covers the wellness-journey side of this question.
Can Ketamine Damage the Bladder?
Yes — bladder injury is a recognized risk of long-term ketamine exposure. The esketamine prescribing information notes that cases of interstitial or ulcerative cystitis have been reported with long-term off-label use or misuse of ketamine, and advises monitoring for urinary tract and bladder symptoms (FDA label). StatPearls likewise lists urinary tract and bladder effects among ketamine's documented adverse effects (StatPearls).
The practical signals are lower abdominal pain, pain when passing urine, and needing to urinate more often. Reporting these early is what allows a provider to act rather than react.
Does Ketamine Affect Memory Long-Term?
Cognitive effects are documented with sustained heavy exposure. The esketamine label references impaired cognition reported in individuals with long-term ketamine abuse and advises monitoring for cognitive impairment (FDA label). Short-term memory fuzziness during and shortly after a session is a separate, expected acute effect that clears with the drug.
What remains genuinely unknown is the picture beyond a few years of ongoing maintenance dosing. Long-horizon data on repeated therapeutic use is limited, and honest clinics say so.
Is Ketamine Therapy Addictive?
Ketamine carries real potential for abuse and misuse, which is why it is a controlled substance and why esketamine is dispensed only through a restricted program with in-clinic administration (FDA label). The structural safeguards matter: no take-home supply, fixed appointment spacing, and prescriber oversight.
⚠️ Important distinction: The frequency and dose patterns behind reported bladder and cognitive harms look nothing like a spaced, clinically supervised protocol. Do not use recreational-use data to estimate your own risk — and do not use that distinction to skip monitoring.
Anyone with a history of substance use disorder should raise it directly during screening. It doesn't automatically rule out treatment, but it changes how a plan is built and watched.
Key takeaway: Long-term risk is driven by cumulative exposure and frequency, which is exactly what a monitored protocol is designed to limit.
Who Is at Higher Risk for Ketamine Side Effects?
Risk rises with uncontrolled high blood pressure, certain cardiovascular conditions, a history of psychosis, active substance use disorder, and pregnancy. The esketamine label lists aneurysmal vascular disease, arteriovenous malformation, intracerebral hemorrhage history, and hypersensitivity among its contraindications, and notes it is not recommended in pregnancy (FDA label).
A thorough screening conversation typically covers:
- Blood pressure reading taken at consultation, plus your history of hypertension.
- Cardiac and vascular history, including any prior aneurysm or hemorrhage.
- Psychiatric history — psychosis, mania, and bipolar diagnoses shape the plan. See our notes on screening considerations for bipolar disorder.
- Full medication review, including benzodiazepines and lamotrigine, which clinicians commonly discuss when planning ketamine treatment.
- Substance use history, honestly reported.
- Liver and thyroid status, and pregnancy status where relevant.
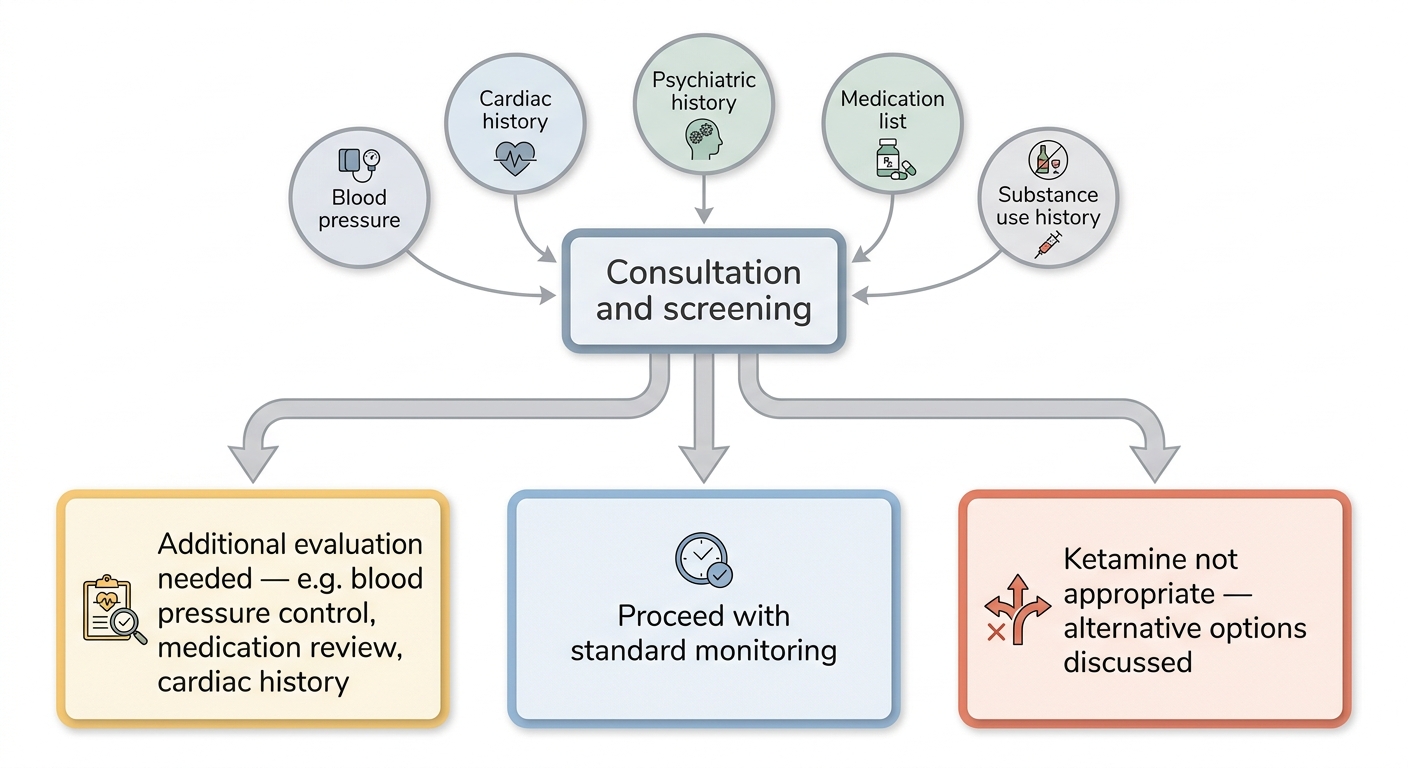
None of these items is a simple yes/no gate. Someone with well-controlled hypertension may be a straightforward candidate, while uncontrolled readings usually mean addressing blood pressure first. That judgment belongs to a clinician who has your full history in front of them.
How Do Clinics Actually Reduce Side Effects?
Most acute ketamine infusion side effects are managed through four levers: dose, infusion rate, pre-medication, and environment. These are not optional extras — they're the reason a monitored session looks different from an unsupervised one.

Standard side-effect management includes:
- Anti-nausea medication before the drip — agents such as ondansetron are commonly given pre-infusion to reduce nausea risk.
- Slow, adjustable infusion rate — the rate can be reduced if dissociation feels overwhelming.
- Vital-sign checks throughout, with blood pressure monitored during and after dosing. The esketamine label directs assessment of blood pressure before dosing and about 40 minutes after (FDA label).
- Sensory calming — dimmed lighting, an eye mask, and quiet music reduce the sensory load that can amplify disorientation.
- A required ride home and no driving or operating machinery for the rest of the day, mirroring the precaution stated on the esketamine label (FDA label).
- Structured recovery time before discharge, rather than a rushed exit.
That combination — continuous monitoring, real-time dose adjustment, and a controlled room — is the part that at-home oral protocols cannot replicate. If you're mapping out logistics, our page on what to expect from an IV ketamine session covers arrival, monitoring, and aftercare rules in order.
Key takeaway: Side-effect management is mostly a design problem, and a clinic solves it with dosing control, pre-medication, monitoring, and a calm environment.
What Symptoms Should You Report Right Away?
Contact your provider promptly for urinary pain or blood in the urine, chest pain, confusion persisting more than a day, worsening suicidal thoughts, or nausea and vomiting that continue past treatment day. Everything else on the common list is usually self-limiting.
Ketamine-induced cystitis is bladder inflammation associated with frequent high-dose exposure, signaled by urinary urgency, pain when passing urine, and lower abdominal pain.
| Expected and self-limiting | Call the clinic |
|---|---|
| Dissociation during the infusion | Confusion or disorientation lasting more than 24 hours |
| Dizziness or unsteadiness for an hour or two | Chest pain, pounding heartbeat, or severe headache |
| Nausea on treatment day | Vomiting continuing past treatment day |
| Mild headache or tiredness that evening | Painful or unusually frequent urination, or blood in urine |
| Vivid dreams the first night | Worsening depression or suicidal thoughts |
| Blurred vision during the session | Vision changes that persist the next day |
⚠️ If you are having thoughts of harming yourself, do not wait for your next appointment. Call 988 (Suicide & Crisis Lifeline) or 911, or go to your nearest emergency department.
Write down what you notice and when. Timing detail — "started two hours after the third session" — is far more useful to a clinician than "I felt off." For cost, safety, and logistics questions beyond symptoms, our ketamine safety and process FAQ is the next stop.
Frequently Asked Questions
How long does dissociation last after a ketamine infusion?
Dissociation typically fades within a short period after the infusion ends, with most people describing mental clarity returning within a few hours. Individual experiences vary, and your recovery time is observed in-clinic before discharge. It is dose-dependent, so a clinician can adjust future sessions if the experience felt too intense. Individual experiences vary, and your recovery time is observed in-clinic before discharge.
Can you drive after a ketamine infusion?
No. Arrange a ride home and avoid driving or operating machinery for the remainder of the day. The esketamine prescribing information instructs patients not to drive or operate machinery until the next day following a restful sleep (FDA label). Clinics apply comparable precautions after IV infusions.
Do ketamine side effects get worse with more sessions?
Usually the opposite. Many patients report that the disorienting effects feel milder by the third or fourth session, as the experience becomes familiar and dosing is calibrated to them. This pattern is not universal — if effects intensify instead, tell your provider, since that changes the plan.
Are ketamine infusion side effects different from Spravato side effects?
Yes. Intranasal esketamine adds route-specific effects such as nasal discomfort and taste changes, and its label requires at least two hours of in-office observation after dosing (FDA label). For a fuller side-by-side, see how Spravato and IV ketamine compare.
Are ketamine side effects different for chronic pain than for depression?
The acute effects — dissociation, dizziness, nausea, blood pressure changes — come from the drug and the dose, not the diagnosis. What differs is protocol design: infusion length and spacing are often set differently for pain conditions than for mood conditions. Your clinician determines the protocol during consultation.
Bringing It Together: Side Effects in Perspective
Sorted by duration, the picture gets much less frightening. The acute ketamine side effects people worry most about — feeling floaty, dizzy, or nauseated — are concentrated in the infusion window and taper within about 30 to 90 minutes of the drip ending. Grogginess may follow you through the evening. By the next morning, most people are back to baseline.
The serious risks — bladder injury, cognitive changes, dependence — are real, documented, and tied overwhelmingly to frequent high-dose exposure rather than spaced clinical dosing. Screening, dose control, and monitoring are precisely what separate those two worlds. That's also why the questions worth asking a clinic are about protocol and oversight, not just price.
Results and experiences vary between individuals, and whether ketamine therapy is appropriate for you is a decision made in a clinical consultation with your full medical history in view. If you're in the Boise or Eagle area and still weighing it, a conversation costs you nothing but an hour.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.