Ketamine Side Effects in Nampa: Clinic vs Street Use
Zora Neuro Spa Editorial · September 29, 2026

Two people can take the same drug and end up with completely different outcomes — and with ketamine, the difference usually comes down to dose, frequency, and whether anyone is watching the monitor. If you're researching ketamine side effects from Nampa, Caldwell, or anywhere in the Treasure Valley, most of what you'll find online blends supervised medical infusions with recreational use into one scary list. This guide separates the two clearly, so you know what actually applies to a clinical setting.
Quick Answer: What Side Effects Does Ketamine Actually Cause?
At supervised sub-anesthetic doses, the most commonly reported effects are dissociation (a floaty, detached feeling), mild nausea, dizziness, and a temporary rise in blood pressure and heart rate — most of which fade within the recovery period after the infusion ends. The bladder damage and memory problems that dominate headlines are linked to frequent, high-dose recreational use over months, not to a standard monitored series. Dose and frequency are the dividing line.
TL;DR
- Dose is the whole story. Therapeutic infusions use sub-anesthetic amounts with continuous vitals monitoring; recreational use involves far larger, repeated doses with none. See the dose and setting comparison
- In-session effects are short-lived. Dissociation, visual drift, and heaviness generally resolve during the monitored recovery window. Read the hour-by-hour recovery timeline
- Bladder and cognitive harms are a frequency story. These are documented largely in chronic heavy users, not standard clinical series. Review the rare-but-serious effects
- Screening prevents most problems. Blood pressure, cardiac history, pregnancy, and psychosis history all change candidacy. Check the screening exclusions
- Route changes the side effect profile. IV, nasal esketamine, and at-home oral dosing differ in intensity and required observation. Compare IV, Spravato, and oral
In This Article
- How Do Clinic Doses Differ From Recreational Doses?
- What Happens to Your Body During the Infusion?
- How Long Do Ketamine Side Effects Last After a Session?
- Which Side Effects Are Rare but Serious?
- Who Should Not Get Ketamine Infusions?
- How Do Clinics Prevent and Manage Side Effects?
- IV Ketamine vs Spravato vs At-Home Oral
- Frequently Asked Questions
How Do Clinic Doses Differ From Recreational Doses?
A supervised psychiatric infusion uses a small fraction of an anesthetic dose, delivered slowly through an IV while a clinician watches your blood pressure, heart rate, and oxygen saturation. Recreational use involves much larger amounts, usually snorted, often repeated across a single night and across many nights — with no vitals check, no known purity, and no one trained to intervene.
Sub-anesthetic ketamine is a dose low enough to preserve breathing, airway reflexes, and consciousness while still acting on NMDA receptors in the brain. Clinical monographs describe sub-anesthetic infusions for mood indications in the range of 0.5 mg/kg given slowly over roughly 40 minutes, according to the StatPearls ketamine monograph.
| Supervised clinical infusion | Recreational / street use | |
|---|---|---|
| Dose | Sub-anesthetic, weight-calculated | Much higher, self-estimated, often repeated |
| Route | IV, slow controlled drip | Usually insufflated (snorted) |
| Setting | Private clinical room | Uncontrolled |
| Monitoring | Continuous vitals, clinician present | None |
| Purity | Pharmaceutical grade | Unknown; may be adulterated |
| Frequency | Scheduled, limited series | Can escalate to frequent, heavy use |
| Typical effects | Dissociation, nausea, dizziness, transient BP rise | Same acute effects at greater intensity, plus risks tied to repeated heavy exposure |
That difference matters when you're reading a general drug-information page. Those pages describe the molecule across every context it's used in — anesthesia, psychiatry, and misuse — so the side effect list reads far more alarming than what a monitored patient actually signs up for.
For Treasure Valley readers weighing the practical side of care, our guide to ketamine infusion therapy in Nampa covers clinic logistics, costs, and how a series is typically structured.
Key takeaway: The risks attached to ketamine in public health literature are largely dose-and-frequency risks, and a monitored clinical series sits at the opposite end of that spectrum from street use.
What Happens to Your Body During the Infusion?
Most people start noticing something within the first several minutes: a floaty or dreamlike quality, colors or shapes that seem to drift, and a sense that time is stretching. Limbs can feel pleasantly heavy. Speech often feels like too much effort, which is why clinics keep the room quiet.
Here's what's happening physiologically:
- Dissociation is a temporary sense of detachment from your body, surroundings, or sense of time. It is expected at these doses rather than a sign something has gone wrong.
- Cardiovascular stimulation — ketamine tends to raise blood pressure and heart rate rather than depress them, which is why vitals are checked throughout (StatPearls).
- Nausea is among the more frequently reported ketamine infusion side effects, which is why many clinics address it before it starts.
- Nystagmus — small involuntary eye movements — is common and harmless, though it can make reading or focusing difficult during the session.
- Dizziness and unsteadiness typically peak near the end of the drip and are the main reason you don't stand up unassisted.
What you won't typically experience is respiratory depression. Preserving spontaneous breathing and airway reflexes is one of the defining features of sub-anesthetic dosing, and it's a key reason this dose range is used outside an operating room.
Emotional effects vary widely. Some people describe the session as calm and introspective; others find parts of it uncomfortable or disorienting. Neither response predicts anything about your treatment, and clinicians can adjust the infusion rate if the experience feels like too much.
⚠️ Feeling anxious mid-session is not a reason to tough it out silently. Tell the clinician — slowing the drip or adding a grounding cue is routine, not a failure.
How Long Do Ketamine Side Effects Last After a Session?
For a standard monitored infusion, the acute effects are measured in minutes to hours, not days. Dissociation fades soon after the drip stops, unsteadiness resolves over the recovery period, and any residual grogginess, mild headache, or appetite change usually clears by the end of the day.
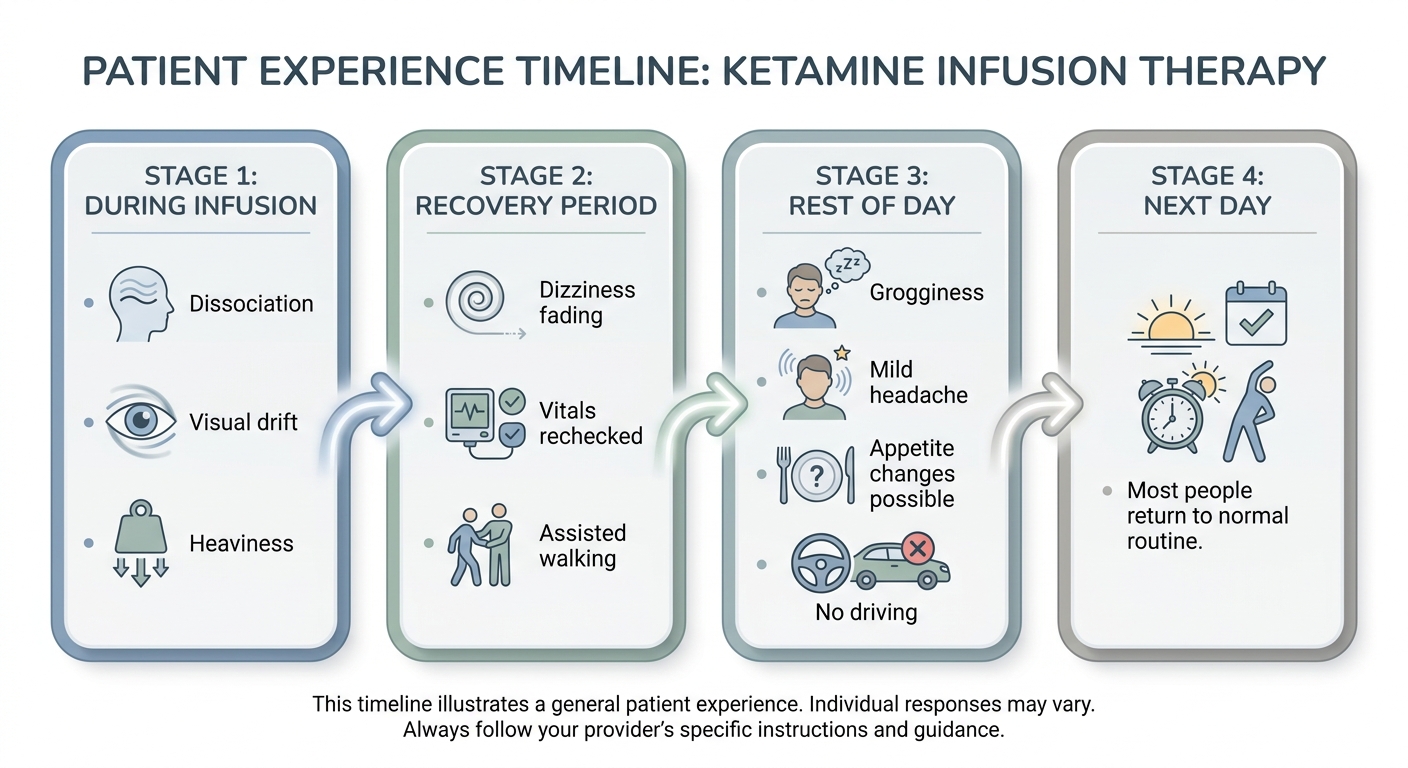
A plain-language version of the same timeline:
- During the infusion — the strongest dissociative and perceptual effects.
- Immediately after — effects taper quickly; you stay seated while vitals are rechecked.
- Monitored recovery — dizziness and unsteadiness resolve enough for discharge with a driver.
- Rest of the day — tiredness, mild headache, or feeling "soft around the edges" is common.
- Next day — most people resume their normal routine.
If your experience falls outside that pattern — dissociation that lingers into the next day, a headache that won't quit, or mood changes that feel unfamiliar — that's information your provider needs before the next session, not something to wait out.
The question of what persists beyond a single day is genuinely different from what happens in the chair. For that longer view, see our breakdown of which ketamine side effects last minutes versus months.
Key takeaway: In a standard supervised protocol, nothing in the expected side effect profile should still be present 24 hours later — and if it is, that's a conversation with your clinician.
Which Side Effects Are Rare but Serious?
Serious events are uncommon in monitored settings, but they exist and deserve plain description. The main ones clinicians watch for:
- A hypertensive response — a blood pressure rise large enough that the infusion is slowed, paused, or stopped. This is precisely what continuous monitoring exists to catch.
- Emergence phenomena — agitation, confusion, or distressing imagery as the drug wears off. StatPearls describes these emergence reactions as a recognized feature of ketamine's profile (StatPearls).
- Vomiting rather than mild nausea, which is one reason patients are asked to limit food and drink beforehand.
- Ketamine-induced uropathy — bladder wall inflammation and reduced bladder capacity, documented primarily in people using ketamine frequently and heavily over extended periods.
Ketamine-induced uropathy refers to damage to the bladder lining associated with chronic, high-frequency ketamine exposure. It is the harm most often cited in drug-education material, and it is also the one least applicable to a limited, supervised series — because the exposure pattern is fundamentally different.
Cognitive complaints follow the same logic. Concerns about memory and thinking are most often documented in populations using ketamine repeatedly and in large amounts, according to the StatPearls ketamine monograph, a different exposure pattern from spaced, weight-calculated doses under supervision.
⚠️ The single biggest safety variable is sourcing. Ketamine obtained outside a licensed clinical channel carries unknown potency and unknown contaminants, and no one is checking your blood pressure. If you take nothing else from this article, take that.
This is also why "ketamine is ketamine" is a misleading statement. The molecule is the same; the exposure, the dose control, and the supervision are not.
Who Should Not Get Ketamine Infusions?
Some conditions make ketamine a poor fit, and others simply require closer screening before a clinician will proceed. A thorough intake should surface all of them before you ever sit in the chair.
Standard reasons a provider may decline or delay treatment:
- Uncontrolled or poorly managed high blood pressure — given ketamine's tendency to raise blood pressure.
- Unstable cardiac disease — including recent cardiac events or unstable angina.
- Active psychosis or a history of psychotic disorder.
- Pregnancy or breastfeeding.
- Untreated substance use disorder, particularly involving dissociatives or stimulants.
- Increased intracranial pressure or certain vascular conditions.
Conditions requiring extra care rather than automatic exclusion include bipolar disorder, a history of distressing dissociative experiences, significant liver disease, and certain interacting medications. For esketamine specifically, the FDA label lists contraindications including aneurysmal vascular disease, arteriovenous malformation, and a history of intracerebral hemorrhage (SPRAVATO prescribing information).
Screening is the part of ketamine therapy that a supervised clinic takes off your plate entirely. You don't have to self-assess your cardiac risk or interpret your own medication list — that evaluation is the clinician's job, and it happens before any dose is calculated. Our ketamine therapy safety and screening FAQ walks through what that intake covers.
How Do Clinics Prevent and Manage Side Effects?
Most ketamine side effects are prevented rather than treated. The infusion rate, the room, the pre-medication, and the recovery protocol are all levers clinicians use before anything uncomfortable starts.

Typical measures include:
- Baseline vitals — blood pressure, heart rate, and oxygen saturation recorded before starting and rechecked throughout.
- Anti-nausea medication — many clinics offer an antiemetic such as ondansetron before or during the infusion rather than waiting for nausea to appear.
- Infusion rate adjustment — slowing the drip is a first-line response to intense dissociation, anxiety, or a rising blood pressure reading.
- A low-stimulus environment — dim lighting, eye mask, headphones, and minimal conversation, which reduces sensory overwhelm during peak effects.
- A monitored recovery period — you stay until you're steady, oriented, and cleared by staff.
- A required driver — you should not drive, operate machinery, or make significant decisions for the rest of the day.
Recovery is also where clinics catch the things you might not mention. Someone checking on you twice during the wind-down period will notice lingering unsteadiness or a slow-to-settle blood pressure that you'd likely shrug off at home.
For a fuller picture of monitoring standards and what distinguishes a well-run program, see our explainer on how clinics monitor ketamine safety.
Key takeaway: Ask a prospective clinic three things — who monitors you, what they do if your blood pressure rises, and how long you stay before discharge. The answers tell you most of what you need to know.
IV Ketamine vs Spravato vs At-Home Oral: How Do Side Effects Compare?
The route changes both how intense the experience feels and how much oversight is built in. IV delivery produces the most controlled and typically the most intense dissociation under direct monitoring. Esketamine nasal spray operates under a federally required safety program. At-home oral dosing has the lowest peak intensity and the least supervision.
| IV ketamine infusion | Spravato (esketamine) nasal spray | At-home oral/sublingual | |
|---|---|---|---|
| Route | Intravenous, rate-controlled | Nasal spray, self-administered under supervision | Lozenge or tablet, taken at home |
| Setting | Clinic, clinician present | Certified healthcare setting under a REMS program | Home, typically via telehealth program |
| Monitoring | Continuous vitals throughout | Post-dose observation of at least 2 hours, per the FDA label | Varies by program; no in-person vitals |
| Commonly reported effects | Dissociation, nausea, dizziness, transient BP rise | Dissociation, dizziness, nausea, sedation, vertigo, and blood pressure increase are listed among adverse reactions in the FDA label | Generally milder peak effects; nausea and grogginess still reported |
| Driving | Not the same day; arrange a ride | The FDA label instructs patients not to drive until the next day after restful sleep | Same-day driving should be avoided |
Esketamine's observation requirement and its Risk Evaluation and Mitigation Strategy (REMS) are set by the FDA, not by individual clinics — the SPRAVATO prescribing information spells out the monitoring, contraindications, and dispensing rules. If you're comparing the two formats, our Spravato esketamine treatment guide goes deeper on eligibility and insurance.
The trade-off with unsupervised at-home dosing isn't intensity — it's that a blood pressure change or a difficult emergence has no one nearby to respond to it.
Frequently Asked Questions
Can ketamine damage your bladder after a few infusions?
Bladder injury is associated with frequent, high-dose ketamine use sustained over long periods — a very different exposure pattern from a limited, spaced series of supervised infusions. Urinary symptoms are still worth reporting to your provider if they appear, because they change the risk conversation. Tell your clinician about any urgency, frequency, or pain with urination at any point in treatment.
Will I remember my ketamine session?
Most people remember the session, though details can feel dreamlike, out of order, or hard to put into words afterward. Some moments may blur entirely while others stay vivid. Many patients jot notes or voice-record impressions during the recovery period, while the material is still close to the surface. Memory of the session is not a measure of whether anything worked.
Can I drive home after a ketamine infusion?
No. Arrange a ride before your appointment and plan to skip driving for the rest of the day. Coordination, judgment, and reaction time can be affected after effects seem to have faded. The same standard applies to esketamine — the FDA label instructs patients not to drive until the day after dosing, following restful sleep.
Do side effects get worse with more sessions?
Many patients report that dissociation feels less startling and nausea less bothersome after they've had a few sessions and know what to expect., partly because they know what to expect and partly because dosing and pre-medication get tuned to them. That said, responses vary between individuals, and any session that feels worse than the last should be reported. Your clinician can adjust rate, dose, or supportive medication.
Summary: Talking to a Provider About Your Risk
Bring three things to a consultation: your complete medication and supplement list, your blood pressure history, and an honest account of any past dissociative or dosing experiences, recreational ones included. None of that is used to judge you — it's used to decide whether ketamine therapy is appropriate and how to dose it safely if it is.
The practical summary of ketamine side effects looks like this: in a monitored setting, most effects are short, expected, and manageable with simple adjustments. The serious harms that dominate search results track with heavy recreational patterns, unknown sourcing, and zero supervision. Those are risks of a behavior, not of the molecule alone.
If you're weighing a first appointment anywhere in the Treasure Valley — Nampa, Caldwell, Boise, or Eagle — our guide to preparing for your first ketamine session covers what to eat, what to bring, and how to set up the day.
Key takeaway: Dose, frequency, sourcing, and supervision decide your risk profile far more than ketamine itself does. Individual suitability and results vary and are determined in a clinical consultation.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.