Ketamine Side Effects by Severity: Mild to Rare
Zora Neuro Spa Editorial · October 5, 2026

Side effects are usually the first thing people ask about before booking a ketamine appointment — and the information online swings wildly between "totally harmless" and "this drug will destroy your bladder." Neither extreme is useful. This guide sorts ketamine side effects into clear severity tiers, explains how long each one typically lasts, and shows why the risks tied to misuse look very different from those seen in a monitored clinical infusion.
Quick Answer: How Serious Are Ketamine Side Effects?
Clinical literature indicates that side effects at sub-anesthetic clinical doses are commonly mild, dose-related, and short-lived, according to the StatPearls ketamine monograph. The common ones — dissociation, dizziness, nausea, drowsiness, and a temporary rise in blood pressure and heart rate — begin during the infusion and fade during the monitored recovery window. Serious problems such as bladder injury and dependence are documented mainly in people using ketamine frequently, at high doses, outside medical supervision, per the ketamine pain-management review. Your individual risk depends on your health history and is decided in a screening consultation.
TL;DR
- Side effects sort into three practical tiers — mild and self-limiting, moderate and managed in-clinic, and rare but serious. See the severity tier table
- Dissociation is the effect people fear most and the one that resolves most predictably, tracking the dose window rather than lingering. Read the hour-by-hour timeline
- Ketamine-induced bladder damage is concentrated in frequent high-dose misuse, not in spaced, supervised infusions. Compare clinical and recreational patterns
- Urinary pain or blood, confusion lasting past bedtime, or chest pain warrant a same-day call. Check the red-flag list
- Screening, premedication, titration, and vital-sign monitoring are how clinics shorten or prevent most effects. See what good prevention looks like
In This Article
- What Counts as a Mild, Moderate, or Serious Side Effect?
- Which Side Effects Are Most Common During an Infusion?
- How Long Do Ketamine Side Effects Last?
- What Are the Rare but Serious Side Effects?
- Clinical Infusion vs Recreational Use
- What Do People Actually Report on Reddit and Patient Forums?
- How Do Clinics Reduce Side Effects Before They Happen?
- When Should You Call Your Provider?
What Counts as a Mild, Moderate, or Serious Side Effect?
Clinicians grade side effects by two things: how much they interfere with what you can do, and how long they last. A sensation that feels strange but passes on its own sits in a different category from one that needs treatment or stops the session.
Severity grading refers to sorting an effect by its impact on function and its duration, not by how unpleasant it feels in the moment. That distinction matters, because the effect patients describe as most alarming — dissociation — is usually graded mild.
Dissociation is a temporary altered sense of your body, time, and surroundings. It is an expected, dose-related effect of ketamine rather than a complication, and the FDA prescribing information for SPRAVATO (esketamine) nasal spray lists dissociative and perceptual changes among the most commonly reported adverse reactions in treatment.
| Severity tier | Example effects | How often reported | Usual duration | What it calls for |
|---|---|---|---|---|
| Mild | Dissociation, dizziness, blurred vision, drowsiness, mild nausea, odd taste | Commonly reported in trials and clinical use | Minutes to a few hours | Reassurance, rest, monitoring |
| Moderate | Vomiting, meaningful blood pressure or heart-rate rise, anxiety or agitation during dosing, headache | Less common | Minutes to hours, managed in-clinic | Medication, slowing or pausing the infusion |
| Rare / serious | Airway spasm, sustained hypertension, bladder injury with heavy cumulative exposure, liver changes with repeated high dosing | Uncommon in supervised dosing; more associated with misuse | Variable; needs evaluation | Immediate clinical response and follow-up |
Three things change where you land in this table: your dose, how fast it is given, and your own medical history. Blood pressure history, heart conditions, liver disease, and a history of psychosis all influence whether ketamine is appropriate at all — which is why screening comes before any booking.
If you are weighing the overall picture rather than a single symptom, our guide to how clinics assess overall ketamine safety walks through the risk–benefit conversation in more detail.
Key takeaway: Severity is about interference and duration — and the effect that frightens people most, dissociation, is usually the one that resolves most predictably.
Which Side Effects Are Most Common During an Infusion?
A small cluster of effects accounts for most of what patients report. Dissociation and perceptual changes lead the list, followed by dizziness, nausea, sedation or drowsiness, and a temporary rise in blood pressure and heart rate.
The clinical monograph on ketamine in StatPearls describes the drug's cardiovascular stimulation — increases in blood pressure and heart rate — along with emergence reactions, nausea and vomiting, and increased secretions as recognized adverse effects of ketamine administration. Those are the effects your clinical team is watching for while you are in the chair.
Here is roughly how they sequence during a sub-anesthetic infusion:
- First several minutes — a floating or heavy-limbed feeling, sometimes mild dizziness or changes in vision.
- Middle of the infusion — dissociation is typically at its strongest. Sound and time can feel distorted.
- Toward the end — effects begin tapering as the infusion rate drops or stops.
- Recovery period — grogginess, unsteadiness on standing, and occasional nausea are the usual residue.
Nausea deserves its own note, because it is both common and largely preventable. Many clinics give an anti-nausea medication before the drip starts rather than waiting to treat it.
Anxiety during dosing is also worth naming honestly. Some people find the dissociative state unsettling, particularly the first time. Room setup, a staff member nearby, and knowing in advance what the sensation feels like all reduce that distress — which is why preparation is part of the protocol, not an afterthought.
Cardiovascular effects are usually transient but are the reason blood pressure is checked repeatedly during the session. People with uncontrolled hypertension or significant cardiac history may not be candidates, and that is determined before treatment, not during it.
Key takeaway: Four effects — dissociation, dizziness, nausea, and a temporary cardiovascular bump — account for the large majority of what patients experience, and all four are anticipated and monitored.
How Long Do Ketamine Side Effects Last?
Acute effects track the dosing window closely. They build over the first minutes, peak partway through, and taper as the drug clears — which is exactly why monitoring periods are structured around that curve. The FDA prescribing information for SPRAVATO (esketamine) nasal spray requires a period of post-dose observation with blood pressure monitoring, as described in the FDA label.
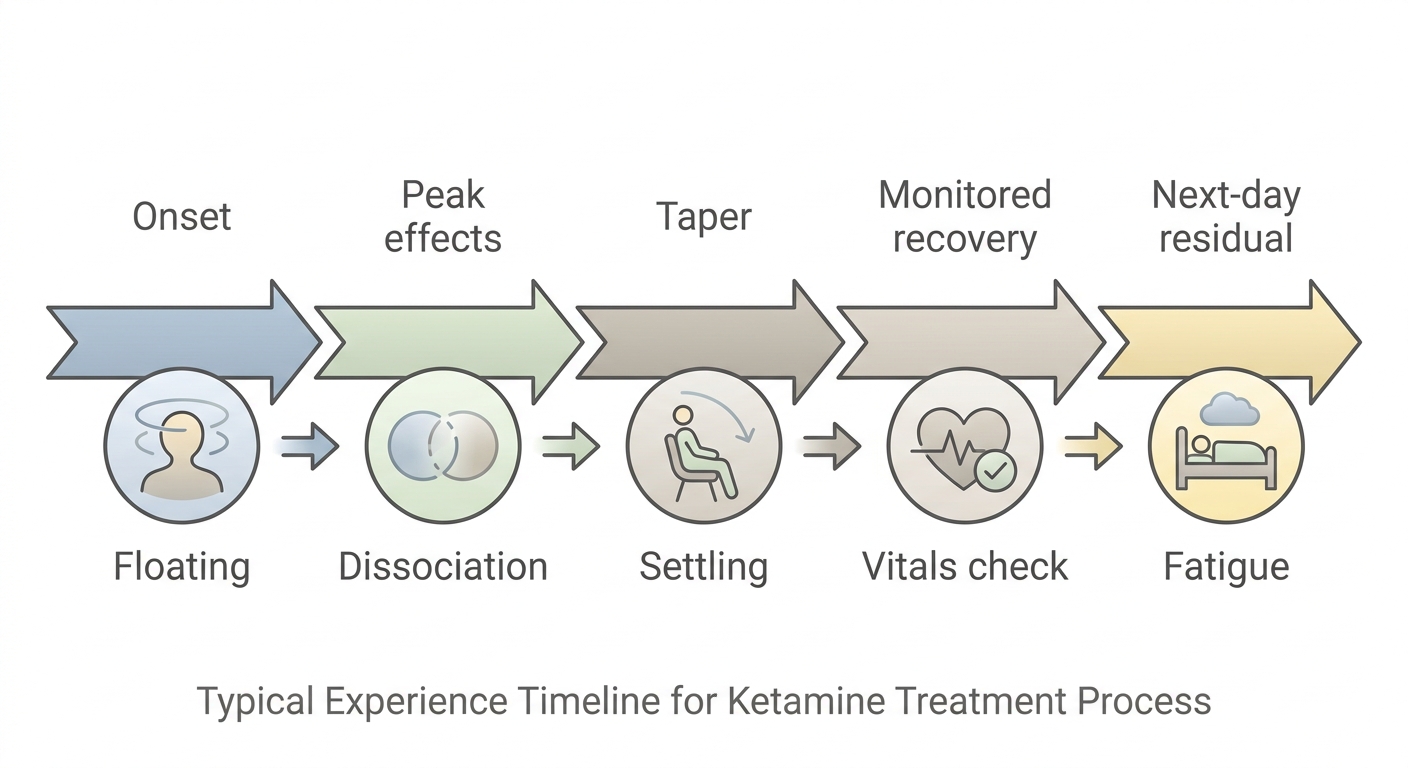
What people most often notice afterward is not dissociation but tiredness. Grogginess, mild fatigue, or a slightly foggy feeling can linger into the evening. A full night's sleep is the usual reset.
Anything that persists past the next day is not typical and should be reported. That includes confusion, ongoing nausea, or urinary symptoms of any kind.
How long ketamine side effects last also depends on the route. Nasal esketamine, IV infusion, and oral dosing have different absorption curves and therefore different recovery windows. For a side-by-side look at what resolves quickly versus what warrants longer attention, see the full minutes-versus-months breakdown.
Practical consequences of that timeline for anyone considering ketamine therapy in Boise, Eagle, or Kuna:
- Plan a ride home. Driving is off the table for the rest of the day.
- Keep the afternoon light. No major decisions, no demanding work.
- Expect to be tired, not impaired, by evening. Most people describe it as a long-nap feeling.
- Track anything that outlasts 24 hours. That is the threshold for a call.
What Are the Rare but Serious Side Effects?
Serious events are uncommon with supervised sub-anesthetic dosing, but they are real and worth naming plainly. StatPearls documents laryngospasm — a spasm of the vocal cords affecting the airway — as a rare but recognized risk of ketamine administration, alongside emergence reactions and cardiovascular stimulation. These are among the reasons ketamine is given in a setting with trained staff and resuscitation capability rather than at a kitchen table.
Ketamine-induced cystitis is inflammation and thickening of the bladder wall linked to frequent, high cumulative exposure. The medical literature describing it comes overwhelmingly from heavy, long-term recreational use rather than from spaced therapeutic infusions.
The serious-end list, in plain terms:
- Airway events — rare, time-limited, and a core reason for clinical monitoring.
- Sustained blood pressure elevation — the reason vitals are checked throughout and why cardiac history is screened.
- Emergence agitation — distress or confusion as effects wear off, managed by environment and, when needed, medication.
- Urinary and bladder injury — associated with high cumulative dosing over long periods.
- Liver enzyme changes — reported with repeated high-dose exposure, which is one reason treatment courses are structured and reviewed rather than open-ended.
⚠️ Any new urinary urgency, pain with urination, or blood in the urine during or after a treatment course should be reported to your provider the same day. Do not wait for the next session to mention it.
Ketamine side effects long term are the hardest category to read about online, because coverage rarely separates cumulative misuse from a defined clinical course. If you are considering ongoing maintenance, what six months of treatment actually looks like addresses cumulative exposure specifically.
It is also worth understanding why federal drug-education materials read so alarmingly. The DEA's public ketamine fact sheet is written for a drug-misuse audience, and its framing reflects anesthetic and abuse-level doses. That context is accurate for its purpose. Applied to a monitored, weight-based infusion in a clinic, it describes a different exposure entirely.
Clinical Infusion vs Recreational Use: Why the Risk Profiles Differ
Four variables separate the two: dose, frequency, product purity, and monitoring. Nearly every frightening outcome people encounter online traces back to a combination of all four going wrong at once.
StatPearls describes the sub-anesthetic dosing used for depression indications as substantially lower than anesthetic dosing, given as a slow infusion over roughly forty minutes under observation. Recreational patterns — repeated redosing, unknown purity, no vitals, no screening — bear no resemblance to that.
| Variable | Monitored clinical infusion | Recreational misuse |
|---|---|---|
| Dose | Weight-based, sub-anesthetic, calculated per patient | Unmeasured, self-selected, often escalating |
| Frequency | Spaced sessions in a defined, reviewed course | Can be daily or multiple times daily |
| Product | Pharmaceutical-grade, pharmacy-sourced | Unknown purity and adulterants |
| Setting | Clinical room, trained staff, emergency equipment | Unsupervised |
| Monitoring | Blood pressure, heart rate, oxygen, direct observation | None |
| Bladder risk | Low exposure; symptoms screened at follow-up | Primary population in the cystitis literature |
| Dependence risk | Access controlled by the clinic; no take-home supply | Self-administered and unrestricted |
Purity is the variable people underestimate. A clinic administers a pharmacy-supplied medication of known concentration. Street supply offers no such guarantee, and that uncertainty compounds every other risk.

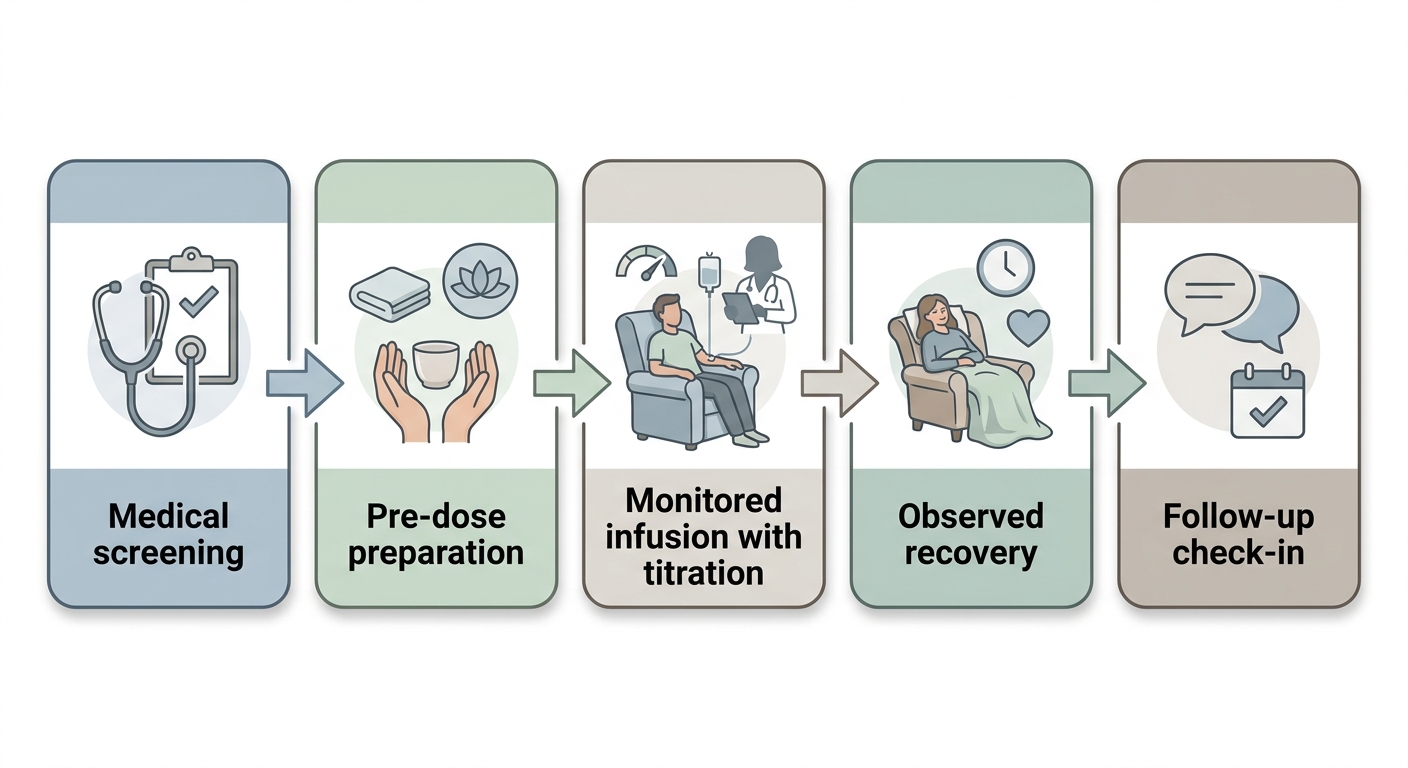
This is also the practical difference in how a session is built. IV ketamine therapy in Boise and Eagle involves intake screening, a calculated dose, continuous observation, and a monitored recovery period before you leave. For a deeper comparison of the two exposure patterns, see clinic-supervised versus street ketamine.
Key takeaway: Most ketamine abuse side effects described online are the product of dose and frequency, not of the molecule itself — which is why a supervised infusion and recreational use carry different risk profiles.
What Do People Actually Report on Reddit and Patient Forums?
Patient communities surface themes that clinical papers rarely capture — but they are anecdotal, self-selected, and unverified. Treat them as a source of questions to raise with a provider, never as evidence.
The recurring themes people describe in ketamine side effects Reddit threads and similar forums include:
- Next-day tiredness — far more commonly discussed than dissociation itself.
- Nausea planning — fasting beforehand and pre-dose anti-nausea medication come up constantly.
- Anxiety about the dissociation — especially before a first session, easing with familiarity.
- Variation between sessions — the same person describing very different experiences session to session.
- Logistics frustration — the ride-home requirement and the half-day it consumes.

⚠️ Forum posts skew toward people with something notable to report. They cannot tell you how common an effect is, whether it applies to your health history, or whether a symptom needs attention. Bring what you read to a clinician instead of acting on it.
The useful move is to turn forum themes into specific questions. If next-day fatigue dominates the threads you are reading, ask how patients typically schedule the day after. If nausea does, ask whether premedication is standard. A good clinic will answer both without hesitation.
How Do Clinics Reduce Side Effects Before They Happen?
Prevention happens mostly before the IV is placed. Screening rules out people for whom the risk is too high, dosing is calculated rather than assumed, and the environment is built to reduce stimulation.
Titration is adjusting the infusion rate in small increments based on your real-time response rather than pushing a fixed dose regardless of how you are doing. It is one of the key tools clinics use to help keep effects in the mild tier.
Questions worth asking any ketamine clinic in Boise, Eagle, or the wider Treasure Valley before booking:
- Who screens me, and what is reviewed? Blood pressure history, cardiac and liver history, psychiatric history, and current medications should all be covered.
- How is my dose determined? It should be weight-based and adjustable, not one-size-fits-all.
- How often are vitals checked during the session? Ask for the interval.
- Is anti-nausea medication offered before dosing?
- Who is in the building during my infusion, and what training do they have?
- How long will I be observed before discharge, and is a ride home required?
- How do you want me to report symptoms between sessions?
At Zora Neuro Spa, treatment begins with a consultation that reviews your health history and determines whether ketamine or esketamine is appropriate for you at all. Suitability is a clinical decision, and not everyone who asks will be a candidate. IV ketamine for depression is administered off-label, while esketamine (SPRAVATO) is FDA-approved for specific treatment-resistant depression indications.
For a closer look at how monitoring protocols map to specific effects, see the prevention protocols clinics use.
When Should You Call Your Provider?
Call the same day for any of the following, and call 911 for breathing difficulty or chest pressure.
Same-day call:
- New urinary urgency, frequency, pain with urination, or blood in the urine
- Confusion, disorientation, or unusual speech that is still present at bedtime
- Nausea or vomiting that has not settled several hours after the session
- A headache that is severe or unlike your usual pattern
- Worsening mood, agitation, or any thoughts of self-harm
Emergency — call 911:
- Chest pain or pressure
- Difficulty breathing
- Fainting or inability to stay awake
⚠️ If you are experiencing a mental health crisis or thoughts of suicide, call or text 988 (the Suicide and Crisis Lifeline) or go to your nearest emergency department. Do not wait for a scheduled appointment.
Keeping a short note after each session — what you felt, when it started, when it stopped — makes these conversations faster and more accurate. If something concerns you between appointments, talk to the Zora Neuro Spa care team rather than waiting it out.
Key takeaway: Urinary symptoms, next-day confusion, and worsening mood are the three categories that should never be left until the next scheduled visit.
Frequently Asked Questions
Short answers to the questions that come up most often. Our full ketamine safety and process FAQ covers cost, scheduling, and candidacy in more depth.
Do ketamine side effects get worse with more sessions?
Not typically. Some patients describe the experience becoming more familiar across a series, though individual responses vary and should be discussed with your provider. That said, responses vary between individuals, and any new or worsening symptom should be reported rather than assumed to be normal adaptation.
Can ketamine cause permanent memory problems?
Cognitive changes documented in heavy, long-term recreational users are not the same exposure as a supervised sub-anesthetic course, and findings from one population do not automatically transfer to the other. Short-term memory and attention can feel fuzzy during and shortly after a session. If fogginess persists beyond the day of treatment, tell your provider so it can be evaluated.
Is nausea during a ketamine infusion normal?
Yes — nausea and vomiting are recognized adverse effects of ketamine, as noted in the StatPearls clinical monograph. Many clinics give an anti-nausea medication before the infusion begins rather than treating nausea after it appears. Fasting guidance before your appointment is given by your provider and is worth following precisely, since it reduces the likelihood and severity of stomach upset.
How does bladder damage from ketamine actually happen?
Bladder injury is associated with cumulative exposure — high doses repeated frequently over long periods, which irritates the bladder lining. The published case literature is concentrated in people using ketamine recreationally at high frequency, not in patients receiving a spaced, supervised course. Reporting urinary symptoms early is the practical safeguard in any treatment course.
What Side Effects Should Shape Your Decision?
For most people weighing treatment, the deciding factors are logistical rather than medical: the monitored recovery window, the required ride home, and losing most of a day. Those are the predictable costs.
The severity picture is simpler than the internet suggests. Ketamine side effects at clinical doses cluster in the mild tier — dissociation, dizziness, nausea, drowsiness, and a temporary cardiovascular bump — and resolve on a schedule the clinical team is built around. Moderate effects are managed during the session. Rare serious events are uncommon with supervision and are concentrated, in the published literature, among patterns of frequent high-dose misuse.
What you cannot determine from an article is whether any of this applies to you. Blood pressure history, cardiac and liver conditions, psychiatric history, and current medications all change the calculation, and background on treatment-resistant depression from the National Institute of Mental Health is a useful starting point before that conversation.
The next step is a screening consultation, not a decision. Bring your list of questions, your medication list, and whatever you read that worried you.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.