Ketamine Therapy Side Effects: Short-Term vs Long-Term
Zora Neuro Spa Editorial · October 8, 2026

Ketamine therapy side effects fall into two very different buckets: the things you feel in the chair, and the things people worry about years down the road. Those two conversations get blended together constantly — usually by mixing clinical infusion data with recreational-use data. Here's a plain-language breakdown of what fades in hours, what the long-term evidence actually shows, and when a symptom is worth a phone call.
Quick Answer
Most ketamine therapy side effects are short-term. Dissociation (a temporary altered sense of body and time), nausea, dizziness, sedation, and a brief rise in blood pressure typically peak during the infusion and ease afterward as the medication clears. The FDA prescribing information for esketamine lists dissociation, sedation, nausea, dizziness and blood pressure increase among the effects monitored in clinic (SPRAVATO label). Long-term concerns — bladder irritation, dependence, cognitive change — are documented mainly in frequent, high-dose, unsupervised use rather than spaced clinical dosing (StatPearls).
TL;DR
- The intense part is the short part. Dissociation and perceptual changes happen during the session and settle as the drug wears off. See what happens during the infusion
- Nausea and blood pressure are the two effects clinics actively manage. Both are addressed with pre-medication and repeated vitals checks. Review the body-system breakdown
- Long-term harm signals come from a very different exposure pattern — frequent, high-dose, unmonitored use, not spaced supervised infusions. Read what the long-term data shows
- The side effect shape differs from antidepressants: brief and episodic versus mild and continuous. Compare the two profiles side by side
- Screening and monitoring are the real safety mechanism. See what screening covers
In This Article
- What Side Effects Happen During the Infusion?
- Which Side Effects Last the Rest of the Day?
- Ketamine Side Effects by Body System
- What Does Long-Term Ketamine Therapy Data Actually Show?
- Why Clinical Dosing Changes the Risk Picture
- How Do Ketamine Therapy Side Effects Compare to Antidepressant Side Effects?
- When Should You Call Your Clinic?
- What Monitoring and Screening Reduce Risk?
- Frequently Asked Questions
What Side Effects Happen During the Infusion?
The effects you notice during a ketamine infusion are dose-dependent and largely expected — not a sign something has gone wrong. A subanesthetic infusion is designed to produce a mild altered state, and your care team watches your vitals the whole time.
Dissociation is a temporary altered sense of your body, surroundings and the passage of time. It is listed among the adverse reactions in the FDA esketamine prescribing information, and it resolves as the medication clears.
Commonly reported in-session effects include:
- Perceptual drift — colors, sound or body weight feeling different than usual
- Sedation and drowsiness — both listed in FDA labeling for esketamine
- Dizziness or vertigo — usually most noticeable when sitting up
- Nausea — often pre-treated with an anti-nausea medication before dosing begins
- A transient rise in blood pressure and heart rate — ketamine's cardiovascular stimulation is described in the StatPearls ketamine monograph
- Anxiety at onset — some people feel a brief surge of unease as the effects begin
Practical management is unglamorous and effective: an automated blood pressure cuff cycling at set intervals, an anti-emetic given beforehand, dim lighting, eye shades, and a clinician in the room. If blood pressure climbs or anxiety spikes, the infusion rate can be slowed or paused.

If you want the full minute-by-minute picture of what happens during an IV ketamine session, that walkthrough covers the setup, the dosing window and recovery.
⚠️ Dissociation can feel strange or disorienting the first time. Tell your clinician the moment it feels like too much — dose and infusion rate are adjustable, and that feedback shapes your next session.
Which Side Effects Last the Rest of the Day?
Some people feel tired, foggy or slightly unsteady for a few hours after leaving the clinic. That's the main reason driving is off the table for the rest of the day. The FDA label for esketamine instructs patients not to drive or operate machinery until the next day following restful sleep (SPRAVATO label), and IV clinics apply a comparable precaution.
Same-day effects people describe most often:
- Grogginess or mental fog that fades with rest
- Mild headache
- Appetite changes — food may sound unappealing for a few hours
- Emotional rawness — feeling open, tender or unusually reflective
- Vivid dreams that night
Your post-infusion checklist:
- Arrange a ride home before you arrive. A rideshare is acceptable at many clinics; confirm your clinic's policy.
- Eat something light once nausea has passed.
- Skip alcohol for the rest of the day.
- Postpone big decisions and hard conversations until tomorrow.
- Write down anything that surfaced — it's useful material for integration or therapy.
Planning for this is easier when you know it's coming. Our guide to preparing for your first ketamine session covers logistics, fasting instructions and mindset in more detail.
Key takeaway: Build your treatment day around an easy evening — a ride, a light meal and no obligations — and most same-day effects pass quietly.
Ketamine Side Effects by Body System
Sorting side effects by body system is more useful than a flat severity list, because it tells you where a symptom is coming from and who handles it. The table below groups the effects most often discussed in clinical sources.
| Body system | Common effect | Typical pattern | What the clinic does |
|---|---|---|---|
| Neurologic / psychiatric | Dissociation, perceptual change, transient anxiety | Peaks during dosing, settles after | Dose titration, calm setting, clinician present |
| Cardiovascular | Rise in blood pressure and heart rate | Transient, during and shortly after infusion | Repeat vitals checks; screening for uncontrolled hypertension |
| Gastrointestinal | Nausea, occasional vomiting | During or shortly after infusion | Anti-nausea medication before dosing |
| Vestibular | Dizziness, vertigo, unsteadiness | Short-lived; worst on standing | Slow transition from recliner, assisted walking, no driving |
| Cognitive | Short-term attention and memory dip | Hours, not days, at clinical doses | Driving restriction; schedule light tasks |
| Urologic | Urinary urgency or discomfort | Uncommon at clinical infusion doses | Symptom screening at each visit; prompt evaluation |
Cardiovascular stimulation, emergence phenomena and nausea are all described as recognized ketamine effects in the StatPearls clinical monograph. Dissociation, sedation, dizziness, nausea and blood pressure increase appear in FDA labeling for esketamine.
The urologic row deserves its own note. Bladder symptoms are the one category where "mention it next time" isn't good enough — report it the same day. Our ketamine safety and process FAQ covers what intake screening asks about before your first appointment.
What Does Long-Term Ketamine Therapy Data Actually Show?
Long-term safety is where honesty matters more than reassurance. The serious harms people have read about — bladder damage, liver strain, lasting cognitive change — appear in the literature overwhelmingly in the context of frequent, high-dose, unsupervised use.
Ketamine-induced uropathy refers to inflammation and damage to the bladder lining associated with chronic, heavy ketamine exposure. It is described in the clinical literature in connection with long-term ketamine abuse (StatPearls), not with spaced therapeutic infusions.
Two other long-term considerations are explicitly flagged by regulators for the esketamine formulation:
- Abuse and misuse potential. The FDA label addresses risk of abuse and misuse, which is why esketamine is dispensed only through a restricted program with in-clinic administration and observation (SPRAVATO label).
- Cognitive effects. Labeling addresses impairment of attention, judgment, thinking, reaction speed and motor skills around dosing — the basis for the driving restriction.
Here's the part competing pages often skip: long-term clinical data for repeated ketamine therapy is thinner than the decades of data behind SSRIs. Depression treatment is still an evolving field, and the National Institute of Mental Health describes an ongoing landscape of treatment research rather than a settled one. A clinic that tells you long-term risk is zero is overstating what the evidence supports. A clinic that tells you supervised, spaced dosing looks very different from daily heavy use is describing what the literature actually distinguishes.
What that means practically for anyone considering ketamine therapy in Boise or Eagle:
- Ask how often you'd be dosed and for how long — exposure frequency matters more than any single session
- Expect bladder and mood symptom screening at every visit, not just at intake
- Expect maintenance spacing to be reassessed rather than set and forgotten
- Expect results and tolerability to vary between individuals
For a deeper look at the maintenance phase, see our evidence review on the long-term effects of ketamine therapy.
Key takeaway: The long-term risk conversation is really a dose-and-frequency conversation — and supervised therapy sits at the opposite end of that spectrum from the use patterns behind the scary headlines.
Why Clinical Dosing Changes the Risk Picture
Risk from ketamine isn't set by dose alone. It's set by three variables multiplied together: dose × frequency × duration of exposure. A subanesthetic infusion given every few days for a short series, then spaced out, produces a fundamentally different total exposure than heavy daily use.
Clinical infusion protocols for depression use low, subanesthetic doses given slowly under monitoring — a range well below anesthetic dosing, as described in the StatPearls ketamine monograph. Recreational use typically involves far larger amounts, taken repeatedly, with no vitals checks, no screening and no one watching for early warning signs.
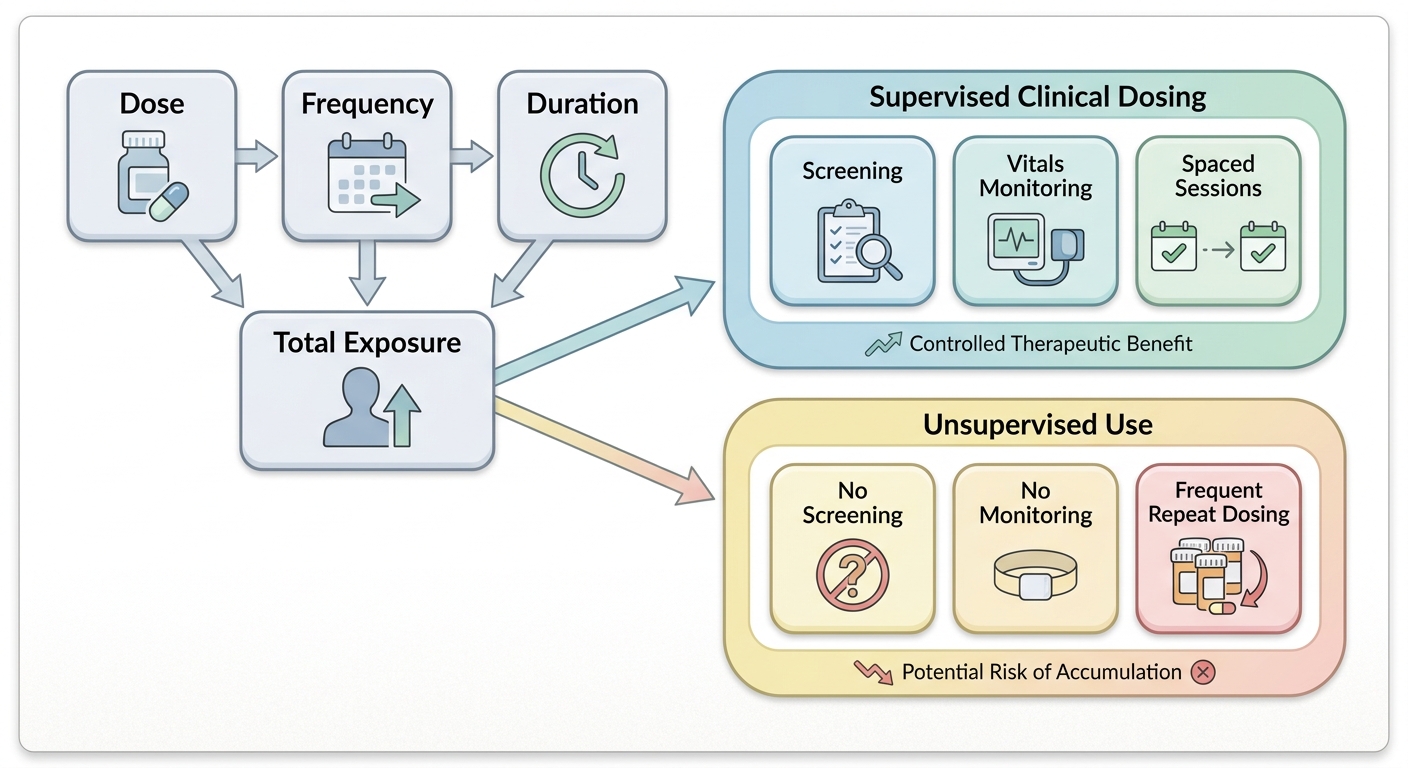
Supervision adds a second layer the math doesn't capture: early detection. A monitored patient who mentions urinary urgency gets evaluated that week. An unmonitored user may not connect the symptom to anything until it's advanced.
This is also why the delivery route shapes the experience. Our overview of IV ketamine therapy in Boise and Eagle explains how an infusion allows the dose to be slowed, paused or adjusted in real time — a level of control that at-home or unsupervised dosing doesn't offer.
How Do Ketamine Therapy Side Effects Compare to Antidepressant Side Effects?
The two profiles differ in shape more than in severity. Ketamine therapy side effects tend to be noticeable but brief and tied to dosing days. Oral antidepressant effects tend to be milder in any given moment but continuous, because you take the medication daily.
| Factor | Supervised ketamine therapy | Daily oral antidepressants (e.g. SSRIs like sertraline, SNRIs like venlafaxine) |
|---|---|---|
| When effects occur | During and shortly after dosing sessions | Ongoing, any day you take the medication |
| Duration pattern | Episodic — tied to treatment days | Continuous while on the medication |
| Intensity | More noticeable in the moment (dissociation, dizziness) | Usually milder moment to moment |
| Weight changes | Not a commonly discussed feature of episodic dosing | Weight change is a frequently discussed concern with some agents |
| Sexual side effects | Not a commonly discussed feature of episodic dosing | Commonly raised with prescribers for this drug class |
| Stopping the medication | No daily dose to taper | Discontinuation symptoms are a recognized reason to taper under supervision |
| Driving restriction | Yes, on treatment days | Generally no, though sedation can occur |
| Monitoring required | Yes — vitals and clinician supervision | Periodic prescriber follow-up |
Neither column is "better." They're different trade-offs, and individual responses vary. Some people find a few hours of post-infusion fog easier to plan around than a daily side effect; others prefer no clinic visits at all.
If you're actively weighing a change, our guide to weighing antidepressant side effects before switching walks through the questions to bring to your prescriber. Never stop a prescribed antidepressant on your own — tapering decisions belong with the clinician who prescribed it.
When Should You Call Your Clinic?
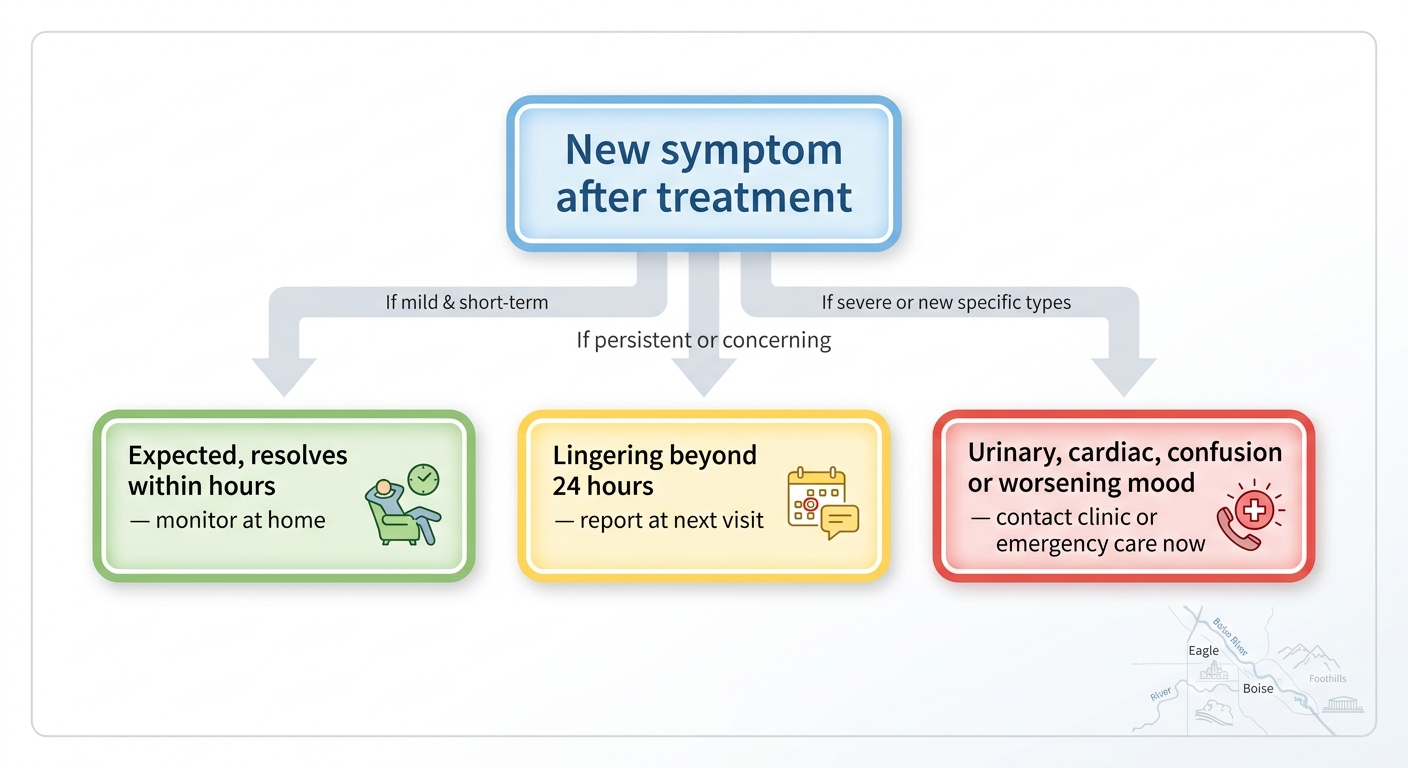
Call if a symptom is new, persistent past 24 hours, or involves your bladder. A simple three-tier triage keeps the decision easy when you're tired and second-guessing yourself.
Green — expected, self-resolving:
- Dissociation during the session
- Dizziness, nausea or fogginess that fades within hours
- Feeling emotionally open or tired that evening
- Vivid dreams the first night
Yellow — mention it at your next visit or during follow-up:
- Fatigue still lingering the next day
- A mood dip two to four days after a session
- Mild headache recurring after each infusion
- Trouble sleeping the night of treatment
Red — call now, or seek emergency care:
- Burning with urination, urinary urgency, or blood in the urine
- Chest pain, severe headache, or symptoms of very high blood pressure
- Confusion or disorientation that hasn't cleared by the next morning
- Worsening suicidal thoughts
If you are in crisis or having thoughts of suicide, call or text 988, the Suicide & Crisis Lifeline, available 24/7 in the United States. For a medical emergency, call 911.
For the clinic-side view of this — how dosing, pre-medication and vitals cadence are used to head off problems before they start — see how clinics prevent ketamine side effects.
Key takeaway: Urologic symptoms, cardiac symptoms and worsening mood never wait for the next appointment. Everything else usually can.
What Monitoring and Screening Reduce Risk?
Most of the safety work happens before and during treatment, not after. Screening decides whether ketamine is appropriate at all; in-session monitoring catches the things screening can't predict.
Screening is the pre-treatment review of your medical and psychiatric history that determines candidacy. FDA labeling for esketamine identifies conditions where treatment is contraindicated, including aneurysmal vascular disease and a history of intracerebral hemorrhage (SPRAVATO label). Blood pressure control, psychiatric history, substance use history, pregnancy status and baseline bladder symptoms are all standard review areas.
What a thorough intake typically covers:
- Cardiovascular history — including blood pressure control and any vascular disease
- Psychiatric history — including psychosis and mania risk
- Substance use history — relevant to abuse and misuse risk noted in FDA labeling
- Current medications — to review interactions with your prescriber
- Baseline urinary symptoms — so any later change is recognizable
- Pregnancy status

During treatment, monitoring means repeated blood pressure and heart rate checks, a clinician present throughout, and observation until you're steady on your feet. Esketamine carries an additional requirement: FDA labeling specifies administration in a certified healthcare setting with patient observation, under a restricted distribution program.
Whether you're researching a ketamine clinic in Boise, comparing esketamine and Spravato options, or asking about ketamine for PTSD, these are fair questions to ask any provider: who is in the room, how often are vitals taken, and what triggers stopping an infusion. You can review our ketamine therapy providers and the ketamine safety and process FAQ for how we handle each of those.
Frequently Asked Questions
Do ketamine therapy side effects get worse with more sessions?
There's no established pattern that supervised, spaced sessions produce escalating side effects. Many people say the experience feels more manageable once they know what dissociation feels like, and clinics commonly adjust dose, infusion rate and anti-nausea support based on how earlier sessions went. Responses vary between individuals, so report anything that feels worse rather than assuming it's expected.
Can ketamine therapy damage your bladder?
Bladder injury — ketamine-induced uropathy — is documented in the literature in connection with chronic, heavy ketamine abuse (StatPearls), not with spaced clinical infusions. That said, urinary burning, urgency, or blood in the urine should be reported to your clinic the same day, regardless of how mild it seems. Early evaluation is the entire point of symptom screening at each visit.
Is it normal to feel low a few days after an infusion?
Some patients describe a temporary mood dip in the days between sessions, and it often settles before the next appointment. It's worth reporting either way, because it may influence session spacing. Persistent or worsening low mood — especially any increase in suicidal thoughts — warrants a call right away, or 988 for immediate crisis support. Integration therapy can help process what comes up between sessions.
Does nasal esketamine have fewer side effects than IV ketamine?
Not fewer — differently shaped. Esketamine is administered in a certified healthcare setting with in-office observation, per FDA labeling, and taste disturbance and nasal discomfort are part of its profile. IV administration allows the dose to be titrated or paused during the infusion. Which route suits you depends on your history, insurance and schedule — a consultation question, not a web-search one.
Can you drive after a ketamine infusion?
No. Arrange a ride before your appointment, and avoid driving until the next day after a full night's sleep. FDA labeling for esketamine instructs patients not to drive or operate machinery until the following day after restful sleep, and IV ketamine clinics apply the same precaution. Rideshares are generally acceptable, but confirm with your clinic — some require an adult companion.
Summary
Ketamine therapy side effects split cleanly along a time axis. The in-session effects — dissociation, dizziness, nausea, a brief blood pressure rise — are expected, monitored, and short-lived. Same-day effects like fog and fatigue are the reason you don't drive. The long-term concerns that dominate headlines are tied to frequent, high-dose, unsupervised exposure, and the clinical literature draws that distinction clearly.
What keeps risk low is unglamorous and consistent: honest screening before the first session, vitals during every one, and a low bar for reporting anything new — especially urinary symptoms or worsening mood. If you're researching ketamine therapy in Boise, Eagle, Caldwell or Nampa for depression, PTSD, OCD, migraines or chronic pain management, bring these questions to a consultation. Individual results and tolerability vary, and suitability is a clinical decision made with a provider who knows your history.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.