Spravato in Boise & Eagle: How It Works, Who Qualifies
Zora Neuro Spa Editorial · October 6, 2026

Finding straight answers about Spravato in the Treasure Valley is harder than it should be — most of what ranks locally is a directory listing with a phone number and no explanation. This guide covers how esketamine works, who actually qualifies, what Spravato side effects look like during a supervised session, and how to confirm a provider near Boise or Eagle is certified to give it.
Quick Answer
Spravato (esketamine) is an FDA-approved nasal spray for treatment-resistant depression in adults, used together with an oral antidepressant. It acts on the brain's glutamate/NMDA system rather than serotonin, and under its FDA risk program it can only be given at a certified treatment center with at least two hours of on-site monitoring afterward. You cannot fill it at a pharmacy or take it at home. In the Boise–Eagle area, certified sites are limited, so "Spravato near me" usually means a short Treasure Valley drive.
TL;DR
- Different chemistry than an SSRI. Esketamine blocks NMDA receptors instead of adjusting serotonin reuptake. See how esketamine works in the brain
- Eligibility is specific. FDA labeling covers adults with treatment-resistant depression, and adults with depressive symptoms in major depressive disorder with acute suicidal ideation or behavior. Check the eligibility criteria and exclusions
- Most side effects are short-lived and supervised. Dissociation, dizziness, nausea, sedation and a temporary blood pressure rise are the ones clinics watch for. Review the side effect table
- You can't drive yourself home — ever. Every session, including maintenance, needs a ride. See what the monitoring window involves
- Certification, not a directory listing, is the thing to verify. Use the seven provider vetting questions
In This Article
Here's where we're headed — jump to whatever you need first.
- How Does Spravato Actually Work in the Brain?
- Who Qualifies for Spravato for Treatment-Resistant Depression?
- What Are the Most Common Spravato Side Effects?
- What Happens During the Two-Hour Monitoring Window?
- Spravato vs IV Ketamine: Which Makes More Sense for You?
- How Do You Find a Certified Spravato Provider Near You?
- What Does Spravato Cost Near Boise, and Will Insurance Cover It?
- What Does the Treatment Schedule Look Like Over Time?
- What Should You Ask Before Your First Appointment?
How Does Spravato Actually Work in the Brain?
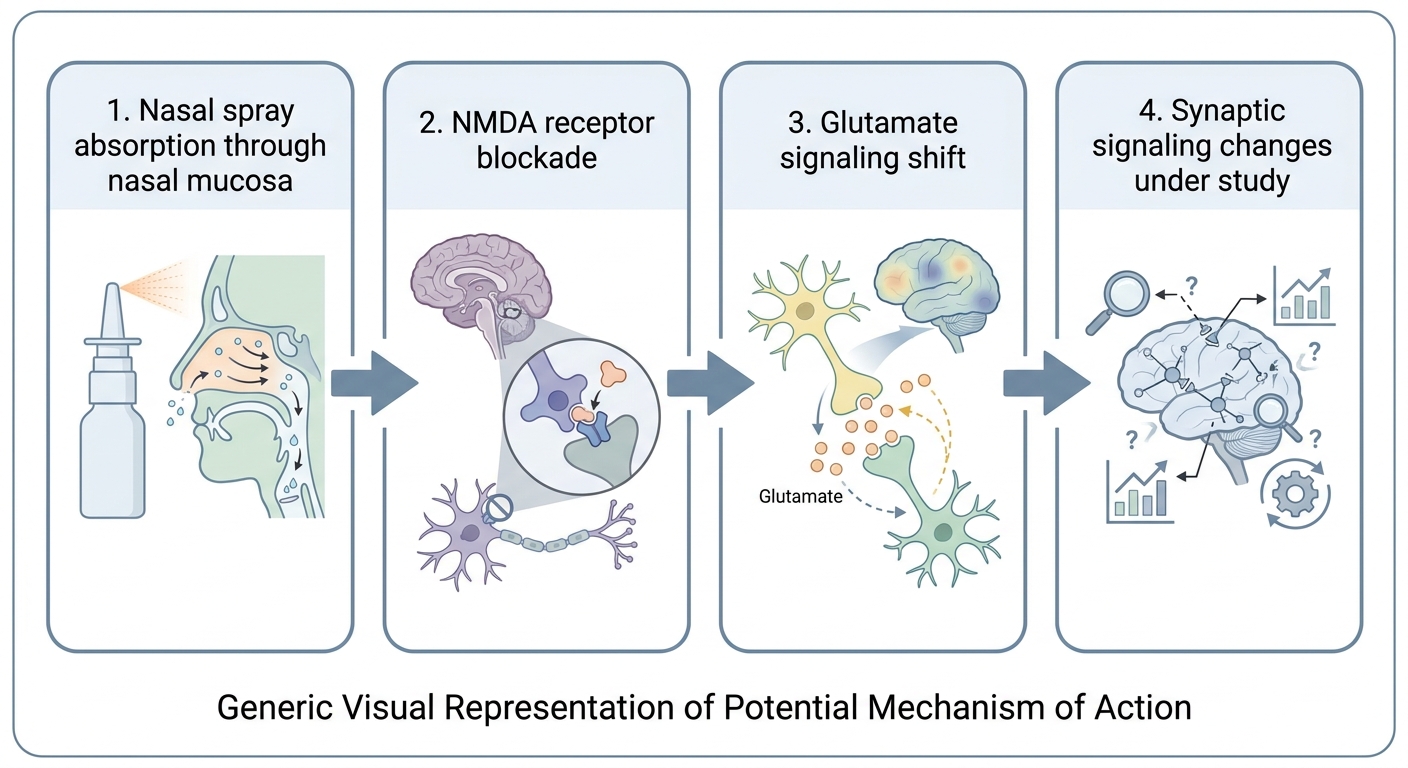
Spravato works through the glutamate system, not the serotonin system most antidepressants target. Esketamine is the S-enantiomer — one mirror-image half — of the ketamine molecule, formulated as a nasal spray device and approved by the FDA in 2019 for treatment-resistant depression in adults, per the FDA prescribing information for SPRAVATO.
Mechanically, esketamine is an NMDA receptor antagonist. Blocking those receptors changes how glutamate — the brain's main excitatory messenger — moves through cortical circuits, which researchers describe as the starting point for the downstream synaptic effects studied in the clinical pharmacology of ketamine. The FDA label notes that the precise mechanism behind its antidepressant effect is not fully established.
That pathway is genuinely different from the serotonin-reuptake mechanism behind most first-line medications described by the National Institute of Mental Health's overview of depression treatment. It's the reason esketamine is considered after other options rather than instead of them.
Practical details worth knowing:
- Device format — each single-use device delivers 28 mg across two sprays, one per nostril.
- Typical dose strengths — 56 mg and 84 mg, using multiple devices spaced apart.
- Always combined — labeling is for use alongside an oral antidepressant, not as a standalone.
If you're weighing routes of delivery, our overview of Spravato and IV ketamine in Boise and Eagle breaks down how the two formats differ in practice.
Key takeaway: Spravato targets a different neurochemical pathway than SSRIs, which is why it's positioned for depression that hasn't responded to standard medications.
Who Qualifies for Spravato for Treatment-Resistant Depression?
You may qualify if you're an adult with major depressive disorder that hasn't responded adequately to prior antidepressant trials in the current episode. The FDA label lists two indications: treatment-resistant depression in adults, and depressive symptoms in adults with MDD who have acute suicidal ideation or behavior — both in combination with an oral antidepressant.
Treatment-resistant depression (TRD) refers to major depressive disorder that has not responded adequately to two or more antidepressant trials taken at a sufficient dose for a sufficient length of time during the current episode.
Am I likely eligible? A quick checklist
- Adult diagnosis of MDD confirmed by a prescriber
- Two or more documented antidepressant trials with drug name, dose, and duration
- Currently taking — or willing to start — an oral antidepressant
- No contraindicated vascular conditions (see below)
- Able to arrange transportation home after every session
- Screened for bipolar disorder, psychosis, and substance use concerns
The label lists contraindications including aneurysmal vascular disease of the brain, chest or abdomen, arteriovenous malformation, a history of intracerebral hemorrhage, and hypersensitivity to esketamine or ketamine. Clinicians also evaluate blood pressure control, cardiovascular and respiratory history, pregnancy and breastfeeding status, and any history of psychosis or substance misuse before approving treatment.
Screening for bipolar disorder matters because the diagnosis changes the risk conversation entirely. A prescriber will review your mood history in detail rather than relying on a depression questionnaire alone.
Response and remission figures from the registration trials are often quoted loosely online — if you want the actual trial outcomes laid out, see our breakdown of published Spravato response and remission rates. Results vary between individuals, and suitability is determined in a clinical consultation, not by a checklist.
For a local view of how this plays out in the Treasure Valley, our guide to esketamine for treatment-resistant depression in Boise covers the evaluation process in more depth.
⚠️ Important: Being "tired of your antidepressant" is not the same as a documented inadequate response. Prior authorization usually hinges on dated records of dose and duration, so gather them early.
What Are the Most Common Spravato Side Effects?
The adverse reactions most frequently reported in clinical trials, according to the FDA prescribing information, are dissociation, dizziness, nausea, sedation, vertigo, decreased sensation, anxiety, lethargy, increased blood pressure, vomiting, and feeling drunk. Most are time-limited and occur during the supervised session — which is exactly why the monitoring period exists.
Spravato side effects differ from IV ketamine side effects in one practical way: they're tied to a fixed, observed window in a clinic chair rather than an infusion you can slow down mid-stream.
| Side effect | Reporting frequency | Typical timing | Typical course | What the clinic does |
|---|---|---|---|---|
| Dissociation (feeling detached from body or surroundings) | Among the most commonly reported | Begins shortly after dosing | Usually eases during the monitoring period | Quiet room, low stimulation, reassurance, observation |
| Dizziness / vertigo | Commonly reported | Early in the session | Generally resolves before discharge | You stay reclined; assisted walking before discharge |
| Nausea or vomiting | Commonly reported | During the session | Usually short-lived | Pre-dose fasting guidance; anti-nausea medication if prescribed |
| Sedation | Commonly reported | During the session | Resolves before discharge check | Continuous observation; no unsupervised movement |
| Blood pressure increase | Commonly reported | Peaks within the first hour after dosing | Generally resolves the same day | Pre-dose and post-dose BP checks; extended monitoring if elevated |
Which Spravato side effects are considered serious?
The FDA label carries a boxed warning covering sedation, dissociation, the potential for abuse and misuse, and suicidal thoughts and behaviors. It also addresses the risk of sustained blood pressure elevation, and the added risk of sedation or respiratory depression when combined with other central nervous system depressants such as benzodiazepines, opioids, or alcohol.
Rare but important considerations include:
- Sustained hypertension requiring medical attention beyond the standard window
- Respiratory depression when CNS depressants are taken alongside esketamine
- Misuse potential, which the REMS program is partly designed to limit
- Cognitive or bladder effects associated with long-term, high-frequency ketamine use in the broader literature, as summarized in the StatPearls ketamine monograph
Tell your prescriber about every medication and supplement you take — including sleep aids and anything prescribed by another clinician.
Key takeaway: Most Spravato side effects are expected, observed, and managed on site; the supervision requirement is a safety design, not a sign of unusual danger.
What Happens During the Two-Hour Monitoring Window?
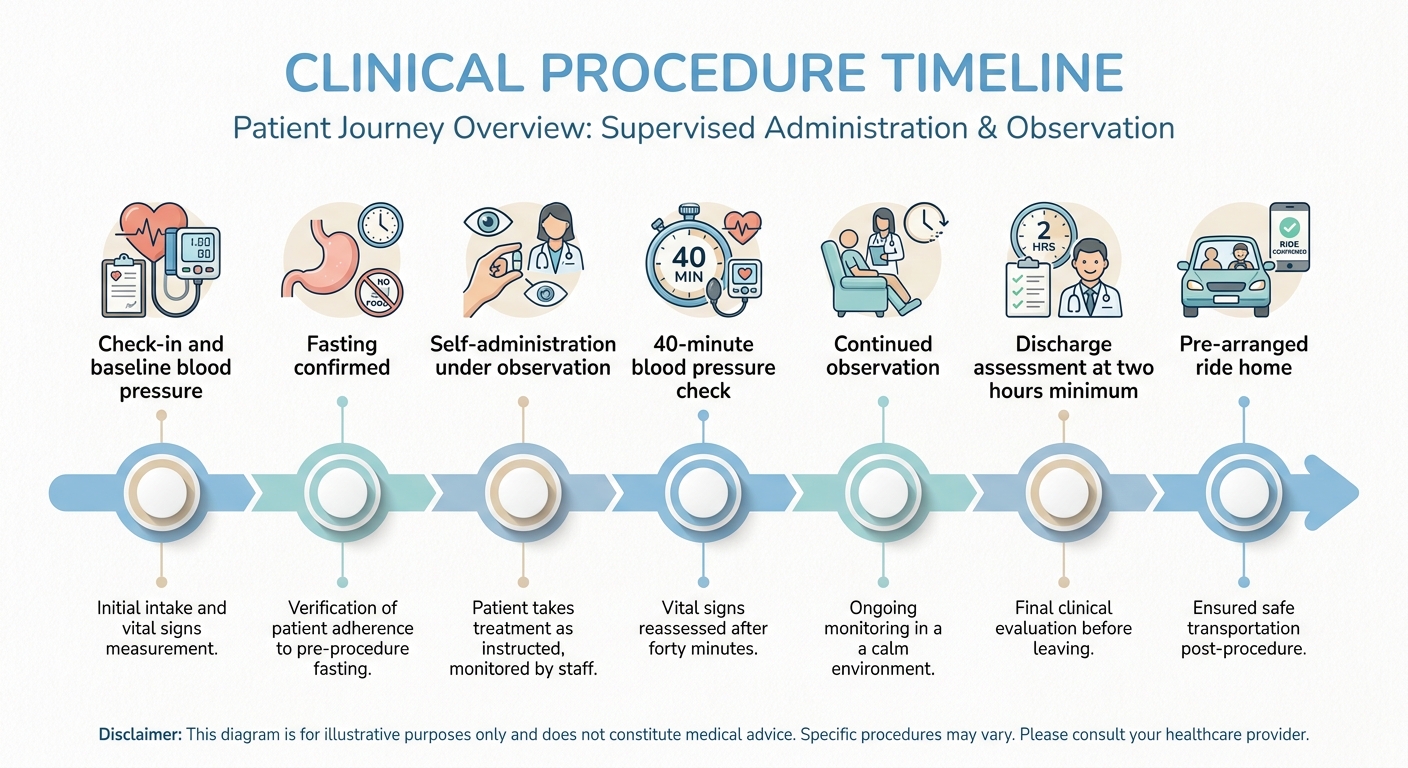
You self-administer the nasal spray under direct observation, then remain at the treatment center for at least two hours while a clinician checks your blood pressure and alertness. The FDA label specifies blood pressure assessment before dosing, approximately 40 minutes after dosing, and further checks as clinically indicated before discharge.

A typical visit runs like this:
- Check-in and vitals — blood pressure and a brief symptom review before anything is administered.
- Fasting confirmation — the label advises avoiding food for two hours before dosing and liquids for 30 minutes before.
- Self-administration — you hold the device yourself; a clinician confirms correct technique and timing between devices.
- Observation — you recline in a quiet room; most people prefer low light and minimal conversation.
- Mid-session check — blood pressure reassessed around the 40-minute mark.
- Discharge assessment — a clinician confirms you're stable and alert enough to leave, no earlier than two hours.
- Ride home — arranged in advance, every time.
For a minute-by-minute walkthrough including what the experience tends to feel like, read our companion piece on what a two-hour Spravato session actually looks like.
Spravato vs IV Ketamine: Which Makes More Sense for You?
Spravato is usually the stronger fit when FDA-approved status and insurance billing matter most. IV ketamine is often chosen when a clinician wants finer control over dose delivery, or when the target condition falls outside esketamine's approved indications.
| Factor | Spravato (esketamine) | IV ketamine |
|---|---|---|
| Route | Nasal spray, self-administered under observation | Intravenous infusion, clinician-administered |
| FDA status | Approved for TRD and for MDD with acute suicidal ideation or behavior | Approved as an anesthetic; used off-label for mood and pain indications |
| Where it can be given | REMS-certified treatment centers only | Clinic settings per state and practice requirements |
| Dose control mid-session | Fixed device doses | Infusion rate can be adjusted by the clinician |
| Oral antidepressant required | Yes, per FDA labeling | Not required by labeling |
| Insurance billing | Commonly billed to insurance with prior authorization | More often self-pay |
| Conditions commonly treated | Treatment-resistant depression | Depression plus off-label uses such as chronic pain conditions |
Neither route is universally better. The decision usually comes down to your diagnosis, your insurance situation, and whether a prescriber judges that a fixed-dose nasal format or an adjustable infusion suits your clinical picture. Our full side-by-side on Spravato and IV ketamine in Boise and Eagle covers the trade-offs in more detail.
Key takeaway: Choose based on diagnosis, coverage, and clinician judgment — not on which format sounds more advanced.
How Do You Find a Certified Spravato Provider Near You?
Start with certification, not a search directory. REMS (Risk Evaluation and Mitigation Strategy) is an FDA-required safety program that restricts where a medication may be dispensed and administered, and requires patient enrollment plus documented monitoring. Per the FDA label, Spravato is available only through a restricted program and must be administered in a certified healthcare setting with on-site monitoring.
That single requirement is why general practitioner directories are a weak starting point. Directory profiles such as those on Psychology Today and Zocdoc are largely self-submitted practitioner descriptions — as of October 2026, listings in the Idaho and Meridian results for this topic present clinician bios and contact details rather than verification that a site is REMS-certified. Treat a directory mention as a lead to verify, not proof.

Seven questions to ask before you book
- Is this specific location REMS-certified to administer Spravato? Ask for confirmation, not a general "yes, we do ketamine."
- Who monitors me during the two hours, and what are their credentials?
- What's your discharge policy? How do you decide when I can leave?
- Do you bill my insurance, or is this self-pay? Which plans are you in-network with?
- Is an oral antidepressant required, and who prescribes it — you, or my current prescriber?
- What's your cancellation and rescheduling policy during the twice-weekly induction phase?
- Do you offer integration or talk therapy alongside treatment?
Geography matters more than usual here, because you can't drive yourself home. Within the Treasure Valley, a session in Eagle is a short drive from Boise, Meridian, Star, Nampa, or Caldwell — but every one of those trips needs a driver during the twice-weekly induction phase. Factor the round trip and your driver's schedule into the decision before you commit.
If you'd like to start with a conversation rather than a booking, our depression treatment consultation in Eagle covers eligibility screening and what care would look like for your situation.
What Does Spravato Cost Near Boise, and Will Insurance Cover It?
Coverage is common but conditional. Most major commercial plans and Medicare cover esketamine for treatment-resistant depression with prior authorization, and you're typically billed for two separate things: the medication itself and the in-office administration and monitoring time. That split is the main reason quoted prices differ so widely between clinics.
Before you accept any quote, confirm these three points:
- Does the price include both the drug and the monitoring time, or only one?
- What is the expected total across the full induction phase, not just per session?
- What is your out-of-pocket responsibility after prior authorization — copay, coinsurance, or deductible?
⚠️ Watch for this: A low per-session figure that excludes the medication or the observation charge can look dramatically cheaper than it is. Ask for the all-in estimate in writing.
Prior authorization mechanics, documentation requirements, and what insurers typically ask for are covered in depth in our guide to Spravato insurance coverage and cost in Idaho.
What Does the Treatment Schedule Look Like Over Time?
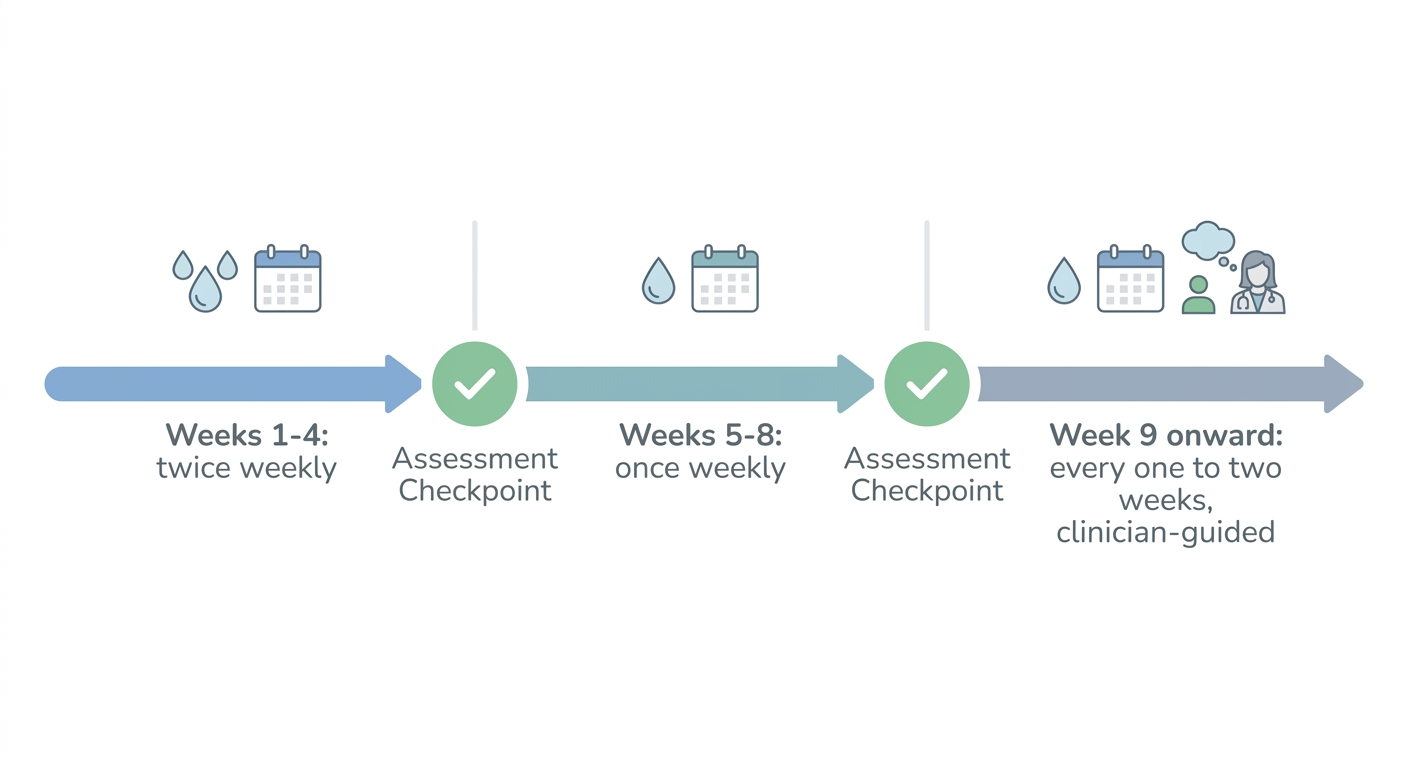
The FDA-labeled schedule for treatment-resistant depression begins with an induction phase of twice-weekly dosing for the first four weeks, followed by once-weekly dosing in weeks five through eight, then maintenance dosing every one or two weeks based on the clinician's assessment, per the prescribing information.
Clinicians typically track progress with a standardized depression scale such as the PHQ-9 or MADRS, administered at set intervals rather than asked informally. A roughly 50% reduction in score is a commonly used research threshold for "response," though how your own prescriber interprets your trajectory depends on your baseline, your other medications, and side effect tolerance.
Three practical scheduling realities to plan around:
- Eight visits in four weeks is a real logistical commitment, including eight rides home.
- Week four is a natural review point — expect a structured reassessment rather than an automatic continuation.
- Maintenance frequency is individualized, and the label directs clinicians to use the lowest frequency that maintains benefit.
If the week-four review shows no meaningful change, a prescriber may adjust dose, reconsider the oral antidepressant, or discuss stopping. That conversation is a normal part of the protocol, not a failure.
Key takeaway: Build your calendar around the induction phase first — it's the part people most often underestimate.
What Should You Ask Before Your First Appointment?
Bring three things: a complete written medication history, your documented antidepressant trial record, and confirmation of your ride home. Prior authorization almost always requires the trial record, so list each prior antidepressant with its drug name, dose, and the dates you took it.
Prep checklist:
- Current medications, supplements, and doses
- Two or more prior antidepressant trials with dates and doses
- Blood pressure history and any cardiovascular diagnoses
- Insurance card and plan details
- Name and availability of your driver
Three questions worth asking the prescriber:
- Based on my history, do you think I meet the labeled criteria — and if not, what's missing?
- Which of my current medications could interact with esketamine?
- What would make you recommend stopping treatment?
Frequently Asked Questions
Is Spravato the same thing as ketamine?
No. Spravato is esketamine, the S-enantiomer — one mirror-image half — of the ketamine molecule, delivered as a nasal spray and FDA-approved for treatment-resistant depression. The ketamine used in infusion clinics is racemic ketamine, approved as an anesthetic and given off-label by IV or intramuscular injection for mood conditions.
How long does it take Spravato to work?
That varies by person, and no responsible clinic will promise a timeline. The labeled protocol builds in structured reassessment: twice-weekly dosing through week four, then a clinical review before continuing. Your prescriber will typically use a standardized depression scale at set checkpoints to decide whether to continue, adjust, or stop.
Can I drive home after a Spravato session?
No. The FDA label instructs patients not to drive or operate machinery until the day after the session, following a restful sleep. Arrange a driver or rideshare for every visit, including maintenance appointments — this requirement doesn't ease up once induction ends.
Do I have to keep taking my antidepressant?
Yes. Spravato is FDA-approved for use in combination with an oral antidepressant, not as a replacement for one. Stopping your oral medication without your prescriber's guidance can jeopardize both your treatment plan and your insurance authorization. Any change should be a shared decision with the clinician managing your care.
Is Spravato available in Eagle and Boise, Idaho?
Yes — certified treatment centers operate in the Treasure Valley serving Boise, Eagle, Meridian, Nampa, and Caldwell. The practical constraint is usually appointment availability during the twice-weekly induction phase rather than distance. Reach out to our Eagle team to check current scheduling and eligibility.
Next Steps if Spravato Sounds Like a Fit
Three things decide whether Spravato is realistic for you: a documented treatment-resistant depression diagnosis, no contraindications on screening, and access to a REMS-certified center with a reliable ride home. Everything else — cost, scheduling, which oral antidepressant you pair it with — gets worked out in the consultation.
Spravato side effects are real but largely predictable, which is why the two-hour monitoring window and certified-site requirement exist in the first place. Knowing what to expect turns an unfamiliar protocol into a manageable one.
If you're in Boise, Eagle, Meridian, or anywhere else in the Treasure Valley and you've already tried two or more antidepressants without adequate relief, the next step is a conversation with a prescriber who can review your records and tell you plainly whether you qualify. Individual results vary, and suitability is always determined through clinical evaluation.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.