Spravato Success Rates and Side Effects, by the Numbers
Zora Neuro Spa Editorial · October 2, 2026
If you have typed "Spravato treatment near me" into a search bar from Boise or Eagle, you have probably found plenty of hope and very few numbers. This guide does the opposite: it walks through what the registration trials actually measured, how often each side effect showed up, who gets screened out, and what a certified clinic visit requires — so you can judge the odds for yourself.
Quick Answer
Spravato (esketamine) nasal spray is FDA-approved as an add-on to an oral antidepressant for treatment-resistant depression, and its short-term efficacy was measured at four weeks, not four days. In the key adult trial described in the FDA prescribing information, the esketamine group improved by roughly four more points on the standard depression rating scale than the placebo spray group at day 28. The most frequently reported side effects in those trials were dissociation, dizziness, nausea and sedation — effects the label manages with a minimum two-hour in-clinic monitoring period. Anyone searching for Spravato treatment near me should know it can only be given at a REMS-certified site.
TL;DR
- "Success rate" is two different numbers. Clinics quoting a high figure are usually quoting response, not remission — and the difference matters. See how response and remission are defined
- The trial endpoint was day 28. Plan your schedule around four weeks of twice-weekly dosing, not a single visit. Review the dosing timeline
- Four side effects dominate the label. Dissociation, dizziness, nausea and sedation were each reported in roughly a quarter to 40% of patients in short-term trials. Check the side effect incidence table
- A Boxed Warning drives the whole protocol. Sedation, dissociation, misuse potential and suicidality are why the spray is never dispensed to take home. Read what the Boxed Warning covers
- Some people are screened out before dosing. Certain vascular conditions are listed contraindications. Go through the eligibility checklist
In This Article
- What Does a Spravato Success Rate Actually Measure?
- What Do the Clinical Trials Show?
- How Fast Does Spravato Work Compared to Antidepressants?
- What Are the Most Common Spravato Side Effects?
- What Are the Rare but Serious Risks?
- Who Qualifies for Spravato, and Who Gets Disqualified?
- Searching "Spravato Treatment Near Me"? How to Vet a Clinic
- Spravato vs IV Ketamine: Which Has Better Odds?
What Does a Spravato Success Rate Actually Measure?
"Success" in esketamine research means one of two very different things, and the gap between them explains most of the confusing numbers you'll see online.
Response is a 50% or greater drop in a person's depression severity score from where they started. Remission is a score low enough to indicate near-absence of symptoms — a much higher bar. A clinic quoting an impressive percentage is almost always quoting response.
MADRS refers to the Montgomery-Åsberg Depression Rating Scale, the clinician-rated instrument used as the primary measure in the esketamine registration trials. Scores move with symptoms like sadness, sleep disruption, appetite change and inner tension.
Three things are worth holding onto when you read any figure:
- The population was narrow. Participants had treatment-resistant depression — meaning an inadequate response to multiple prior antidepressants. Results from that group don't automatically transfer to someone on their first medication.
- Everyone got an antidepressant. Spravato was studied alongside a newly started oral antidepressant, not instead of one, per the FDA label.
- The comparison was an active placebo. The control group used a placebo nasal spray, so the measured advantage is on top of whatever the oral medication and the clinic routine contributed.
⚠️ Watch for this: a percentage with no definition attached to it — response or remission, at what week, in which trial — isn't a usable number. Ask any clinic which measure they're citing.
What Do the Clinical Trials Show?
The evidence base behind FDA approval rests on a set of Janssen-sponsored trials: three four-week studies (TRANSFORM-1, TRANSFORM-2, TRANSFORM-3) and a relapse-prevention study (SUSTAIN-1).
| Trial | Population | Design | What it addressed |
|---|---|---|---|
| TRANSFORM-1 | Adults 18–64 with treatment-resistant depression | Fixed doses plus a newly started oral antidepressant, 4 weeks | Evaluated the fixed 56 mg and 84 mg dose levels |
| TRANSFORM-2 | Adults 18–64 with treatment-resistant depression | Flexible dosing vs placebo nasal spray, 4 weeks | The short-term efficacy study described in the FDA label |
| TRANSFORM-3 | Adults 65 and older | Flexible dosing vs placebo nasal spray, 4 weeks | Results in older adults were less clear-cut than in younger adults |
| SUSTAIN-1 | Adults who had already improved on esketamine | Continue vs switch to placebo spray | Whether continued dosing delayed relapse |
According to the FDA prescribing information, the short-term adult study showed a roughly four-point greater improvement on MADRS at day 28 for esketamine plus an oral antidepressant compared with placebo spray plus an oral antidepressant. That is a statistically meaningful difference at the group level — and a modest one at the individual level, which is exactly why honest framing matters.
The maintenance picture is arguably the more practical finding. The label describes a longer-term study in which patients who had already improved and then continued esketamine experienced a longer time to relapse than those switched to the oral antidepressant alone. In plain terms: the research supports continuing treatment for people who improve, rather than stopping at week four.
What the trials do not tell you is how any single person will respond. Group averages hide wide variation, and individual results differ. Clinics offering Spravato in Boise and Eagle follow the same label-based protocol, so the variable isn't the medication — it's your history, your dosing tolerance, and whether you complete the full induction course.
Key takeaway: The registration trials support a real but moderate group-level advantage over an oral antidepressant alone, with the strongest practical signal coming from continued dosing after an initial improvement.
How Fast Does Spravato Work Compared to Antidepressants?
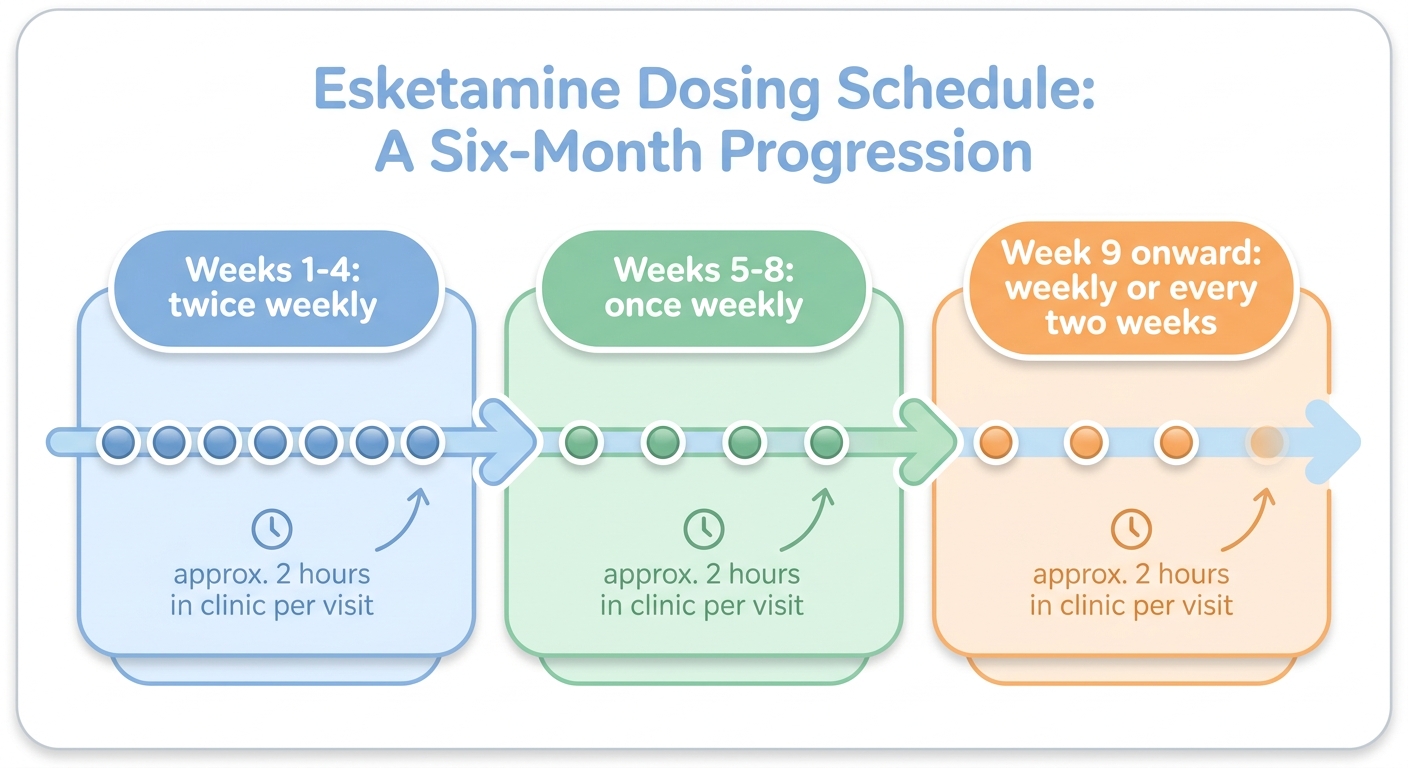
Plan for four weeks, not four days. The primary endpoints in the short-term trials were measured at day 28, after eight dosing sessions — so the schedule, not a single visit, is the unit of evaluation.
The label-described dosing structure looks like this:
- Weeks 1–4 (induction): twice weekly
- Weeks 5–8: once weekly
- Week 9 onward (maintenance): once weekly or once every two weeks, based on clinical judgment
Every one of those visits runs about two hours, because the label requires monitoring for at least two hours after dosing. If you want the minute-by-minute version, our walkthrough of what happens in a Spravato session covers check-in, self-administration, vitals and discharge.
For comparison, the National Institute of Mental Health notes that antidepressant medications generally take several weeks to take effect. Researchers have studied ketamine and its enantiomers partly because of interest in faster-acting mechanisms — the StatPearls clinical monograph on ketamine reviews that pharmacology — but no timeline should be promised to you in advance. What your clinician can tell you is the schedule. What happens on that schedule varies between individuals and is assessed at follow-up.
The honest planning question isn't "how fast," it's "can I get here twice a week for a month with a ride home each time?"
What Are the Most Common Spravato Side Effects?
A handful of predictable, short-lived effects account for most of what patients report. Dissociation is a temporary altered sense of self, body or surroundings — things may feel dreamlike, distant or distorted. It was the single most frequently reported adverse reaction in the short-term trials.
| Side effect | Approximate incidence in short-term trials | Typical pattern | How a clinic handles it |
|---|---|---|---|
| Dissociation | ~41% | Begins shortly after dosing, resolves during monitoring | Quiet room, dim light, staff nearby, no stimulation |
| Dizziness | ~29% | Short-lived post-dose | Stay reclined; assisted walking before discharge |
| Nausea | ~28% | Post-dose | Fasting guidance beforehand; anti-nausea options |
| Sedation | ~23% | Post-dose drowsiness | Monitoring until alert; no driving that day |
| Vertigo | ~23% | Post-dose | Positioning and observation |
| Blood pressure increase | ~10% | Peaks within the monitoring window | BP checked before dosing, ~40 minutes after, then as warranted |
Incidence figures above are drawn from the adverse reactions section of the FDA prescribing information, which reports reactions observed in short-term studies of esketamine plus an oral antidepressant. Other reactions listed at lower frequencies include reduced sensation, anxiety, lethargy, vomiting and increased blood pressure readings.
Two practical notes most pages skip:
- The monitoring window is sized to the side effects, not to bureaucracy. The label's two-hour minimum and its blood-pressure checkpoints line up with when these effects typically appear and recede.
- Side effects can shift over a course. Many people find the first one or two sessions the most disorienting simply because the experience is unfamiliar. That is an observation clinicians commonly discuss, not a guarantee.
For a longer discussion of trade-offs, see our deeper look at esketamine benefits and side effects.
Key takeaway: The two-hour monitoring period exists precisely because the most common effects are predictable and time-limited — the protocol is built around them, not surprised by them.
What Are the Rare but Serious Risks?
The FDA label for Spravato carries a Boxed Warning — the agency's most serious warning format. According to the prescribing information, it covers:
- Sedation and dissociation following administration
- Potential for abuse and misuse
- Risk of suicidal thoughts and behaviors, consistent with the class warning applied to antidepressants
Those warnings are the reason esketamine is dispensed only through a Risk Evaluation and Mitigation Strategy (REMS) program. REMS is an FDA-required safety framework that restricts where a medication can be given and what monitoring must happen. In practice that means the spray is self-administered under supervision at a certified healthcare setting, is never sent home with you, and requires observation by a healthcare provider for at least two hours.
Other risks the label addresses include a transient rise in blood pressure after dosing — which is why certain vascular conditions are contraindications — and impaired ability to drive or operate machinery.
⚠️ Driving rule: The label instructs patients not to drive or operate machinery until the next day following a restful night's sleep. Arrange transportation for every single session, including the ones that feel easy.
Long-term bladder and urinary problems are frequently raised in discussions of ketamine. That evidence base comes largely from prolonged, high-dose recreational ketamine use, as reviewed in the StatPearls monograph — it is extrapolated context, not a finding from the supervised esketamine trials. Still, it's a fair thing to raise with your prescriber, especially if you have an existing urologic condition or expect to be on maintenance dosing for an extended period.
Who Qualifies for Spravato, and Who Gets Disqualified?
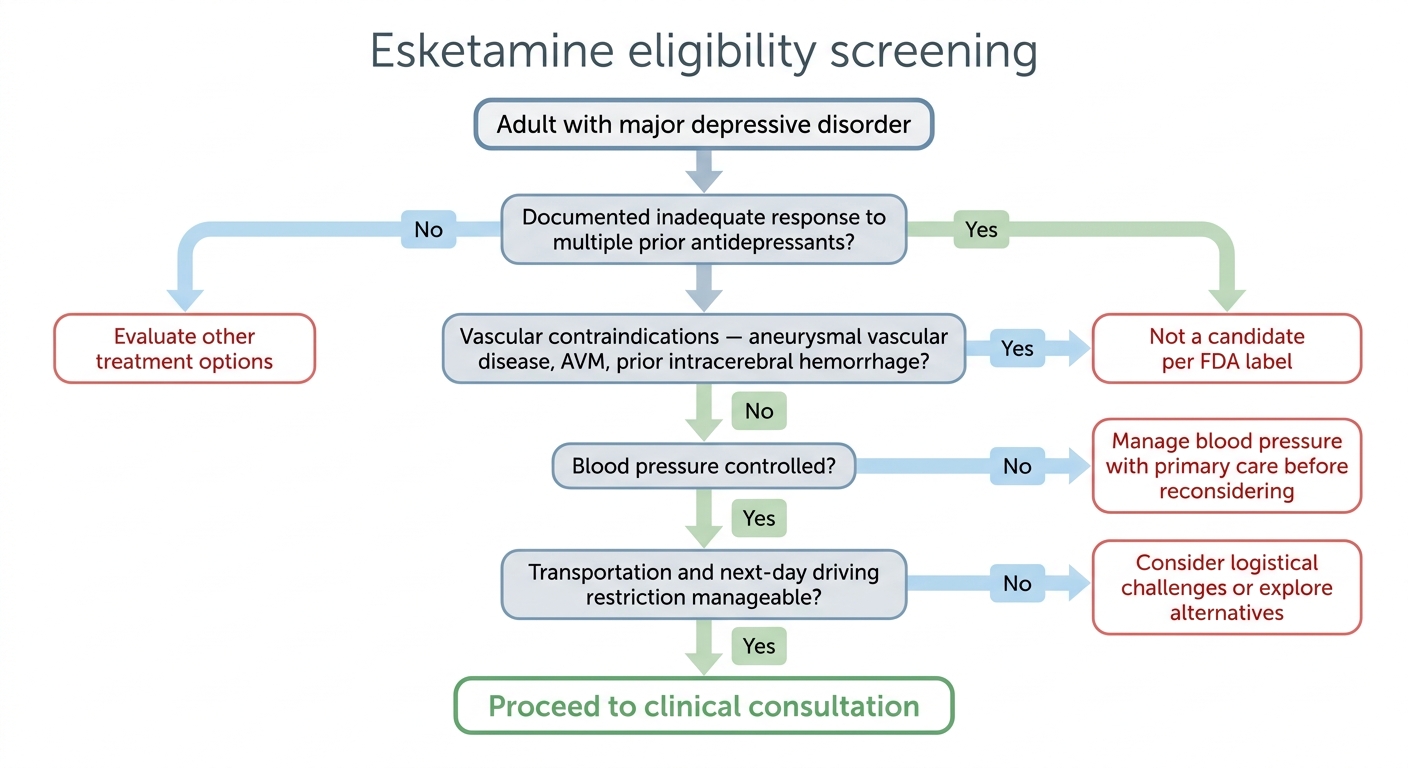
The best-documented candidates are adults with major depressive disorder who have not responded adequately to multiple prior antidepressant trials, and who can commit to supervised in-clinic dosing with a ride home.
Disqualification usually comes from the contraindications and cautions in the label. Bring this checklist to your consultation:
- Vascular history — aneurysmal vascular disease (of the brain, chest or abdomen), arteriovenous malformation, or a history of intracerebral hemorrhage are listed contraindications in the FDA label.
- Blood pressure control — uncontrolled or poorly controlled hypertension is a safety concern given the post-dose BP rise.
- Psychiatric history — a history of psychosis is something clinicians screen for carefully before considering dissociative treatment.
- Pregnancy or breastfeeding — the label addresses use in pregnancy and lactation; discuss plans openly.
- Substance use history — relevant to the Boxed Warning on abuse and misuse.
- Documented medication trials — insurers typically want evidence of prior antidepressant trials at adequate dose and duration.
- Transportation and supervision — no driving until the next day after restful sleep, every session.
Most denials are paperwork problems rather than clinical ones — incomplete medication history is a common stumbling block. Our breakdown of who qualifies for Spravato covers the insurance and prior-authorization side in detail.
Eligibility is decided in a clinical consultation, not by an article. Nothing here substitutes for a prescriber reviewing your full history.
Searching "Spravato Treatment Near Me"? How to Vet a Clinic
Because esketamine can only be dispensed at REMS-certified healthcare settings, your search isn't "any psychiatrist" — it's the short list of certified sites within driving distance. In the Treasure Valley, that generally means Boise, Eagle and Meridian.

Ask these five questions before you book:
- Is this site REMS-certified for esketamine? If the answer is anything other than a clear yes, the medication cannot be given there.
- Who stays with me during the two-hour monitoring window? Ask specifically who checks vitals and who is physically present.
- Do you run a benefits check before my first session, or bill afterward? A surprise bill after session three is the most common complaint in this category.
- Do you also offer IV ketamine if esketamine isn't a fit? Clinics with both routes can pivot without sending you to start over elsewhere.
- What happens between sessions? Ask how symptom tracking, medication coordination and integration support are handled.
That last question separates a dosing site from a treatment program. Twice-weekly visits for a month is a real commitment, and the clinic you choose should make the logistics — scheduling, rides, insurance, communication with your existing prescriber — the easy part rather than another obstacle.
Our Eagle clinic serves patients across Boise, Meridian and the surrounding Treasure Valley, and the consultation is free specifically so you can ask all five questions before spending anything.
Key takeaway: Certification narrows your options to a handful of sites — so the deciding factors become monitoring staffing, billing transparency, and what support exists between sessions.
Spravato vs IV Ketamine: Which Has Better Odds?
Neither route "wins" outright. Spravato carries the stronger regulatory credential — FDA approval for treatment-resistant depression backed by a formal trial program — while IV ketamine offers dose flexibility and a broader set of off-label applications. Direct head-to-head comparisons are limited, so the practical decision usually turns on insurance and route tolerance.
| Factor | Spravato (esketamine nasal spray) | IV ketamine |
|---|---|---|
| Regulatory status | FDA-approved for treatment-resistant depression with an oral antidepressant | Used off-label for psychiatric and pain indications |
| Where it's given | REMS-certified sites only | Medical clinic settings |
| Insurance | Commonly billed through medical benefits with prior authorization | More often self-pay |
| Dose control | Fixed label-defined dose levels | Weight-based, adjustable per session |
| Time in clinic | About two hours per visit per the label | Varies by protocol |
| Off-label range | Label indication is depression-specific | Studied for chronic pain and other conditions |
Which route fits you is a clinical and financial question, not a ranking. Our full Spravato vs IV ketamine comparison walks through both in depth, including how patients typically weigh coverage against scheduling.
Frequently Asked Questions
What is the typical Spravato treatment schedule?
Twice weekly for weeks 1–4, once weekly for weeks 5–8, then weekly or every two weeks for maintenance, as described in the FDA prescribing information. Each visit runs roughly two hours, because the label requires at least two hours of post-dose monitoring. Your prescriber adjusts the maintenance interval based on clinical assessment. Budget for the full induction month when you plan work and childcare — the schedule is the part people underestimate.
What should you avoid while using Spravato?
- Driving or operating machinery until the next day, after a restful night's sleep
- Food for two hours and liquids for 30 minutes before dosing, which the label advises to reduce nausea and vomiting
- Alcohol and other central nervous system depressants, which require caution alongside a sedating medication
These instructions come from the FDA prescribing information. Confirm the specifics with your own prescriber, since other medications you take may add further restrictions.
How hard is it to get prescribed Spravato?
The clinical criteria are usually easier to meet than the paperwork. The common hurdles are documenting prior antidepressant trials at adequate dose and duration, clearing a cardiovascular and medical screen, and getting prior authorization approved. Denials frequently trace back to incomplete medication history rather than the diagnosis itself. Gathering pharmacy records and prior prescriber notes before your consultation removes most of that friction.
Does a higher success rate mean it will work for me?
No — population statistics describe groups, not individuals. A trial average tells you how a treatment performed across hundreds of people with a similar history; it cannot predict your response. Results vary, and some people do not improve. If there's no meaningful change by the end of the induction course, that's legitimate information: it's a reason to reassess options with your prescriber rather than to keep pushing on the same path.
Putting the Numbers in Perspective
Here's the honest read. The registration trials support a measurable but moderate group-level advantage for esketamine added to an oral antidepressant, with the clearest practical signal coming from continued dosing in people who improve. The common side effects — dissociation, dizziness, nausea, sedation — are frequent, well-characterized in the FDA label, and structured around a two-hour monitoring window. The time commitment is real: eight supervised visits in the first month, each requiring a ride home.
Key takeaway: Meaningful odds of improvement, predictable and short-lived side effects, and a genuine scheduling commitment — that's the trade-off, and it's one worth evaluating with a clinician rather than a search engine.
If your search for Spravato treatment near me has turned up more marketing than information, a consultation is the fastest way to replace guesswork with specifics about your own history, your medication record, and your coverage. Our team in Eagle serves patients throughout Boise and the Treasure Valley, and we're happy to tell you if esketamine isn't the right fit.
Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.