Ketamine-Assisted Psychotherapy: Training vs Treatment
Zora Neuro Spa Editorial · October 1, 2026

Choosing a ketamine provider is really two decisions wearing one coat: which medicine, and which people. If you're researching ketamine therapy for depression in Boise or Eagle, the training behind your clinician shapes your experience just as much as the dose does — yet almost no clinic page explains what that training involves. This guide covers what ketamine-assisted psychotherapy (KAP) training actually teaches clinicians, what the resulting credentials do and don't mean, and the questions that separate real preparation from marketing language.
Quick Answer
KAP training is post-licensure education that teaches licensed therapists and prescribers how to prepare a patient for a ketamine session, support them during it, and help them make sense of it afterward. It is clinician education — not a state license, and not a treatment you buy. For patients, the practical point is simple: the medicine is standardized, but the human support around it is not. A provider's training background is one of the clearest signals of how structured your sessions will be.
TL;DR
- KAP training is education for clinicians, not a treatment product. Curricula typically span pharmacology, session facilitation, and integration therapy. See what the five core training domains cover
- Infusion training and KAP training solve different problems. One focuses on medical safety; the other layers therapeutic skill on top. Compare a monitored infusion with a KAP session
- A certificate is not a license. As of 2026 there is no single federally recognized KAP certification board, so quality varies between programs. Understand the credential-versus-license distinction
- Six questions will tell you most of what you need to know about any clinic you're considering. Use the provider vetting checklist
- A full course of care is a sequence, not a single appointment. Walk through the phases from intake to maintenance review
In This Article
Here's the path we'll take, from clinician classroom to your first consultation:
- What Is Ketamine-Assisted Psychotherapy Training?
- What Do KAP Training Programs Actually Teach?
- How Does KAP Training Differ From Standard Infusion Training?
- Who Can Take KAP Training — And What Credential Do They Get?
- Why Does Clinician Training Change the Patient Experience?
- How Do You Vet a KAP Provider in Boise or Eagle?
- What Does a Full KAP Course of Care Look Like Start to Finish?
- Frequently Asked Questions
- Key Takeaways
What Is Ketamine-Assisted Psychotherapy Training?
Ketamine-assisted psychotherapy training is structured education for already-licensed clinicians that prepares them to deliver psychotherapy alongside ketamine dosing. It assumes the clinician already holds a license and adds a specific skill set on top of it.
Two words get used interchangeably online, and they shouldn't be:
- KAP training — what a clinician completes. Coursework, experiential learning, and supervised practice.
- KAP treatment — what a patient receives. Preparation, a supported dosing session, and integration work afterward.
Ketamine occupies an unusual position here. It is a legally available anesthetic medication with a long clinical record, described in the peer-reviewed literature as an NMDA receptor antagonist used across anesthesia, pain, and psychiatric settings (StatPearls, NCBI Bookshelf). That availability is why a whole training industry grew up around it while other psychedelic-adjacent compounds remain restricted.
Programs come from a mix of nonprofits, private institutes, and psychedelic-therapy research organizations. Names you'll commonly see on clinician bios include MAPS-affiliated training, Fluence, Polaris Insight Center, and the Ketamine Training Center. Each publishes its own curriculum, hour requirements, and prerequisites on its own website, and those details change — so verify current specifics directly with the program rather than trusting a clinic's summary of them.
What unites credible programs is the assumption that the medicine alone is not the intervention. The training treats the dosing session as one part of a therapeutic arc that begins before the appointment and continues after it.
Key takeaway: KAP training is clinician education layered onto an existing license — it tells you how a provider was prepared, not what results you should expect.
What Do KAP Training Programs Actually Teach?
Most published KAP curricula cluster into five domains: pharmacology and medical screening, set and setting, in-session presence, integration therapy, and ethics.
| Training domain | What it covers | Why it matters to you as a patient |
|---|---|---|
| Pharmacology & medical screening | Ketamine's mechanism, routes of administration, contraindications, vital-sign monitoring, documented adverse effects | Determines how carefully your history, blood pressure, and medication list are reviewed before dosing |
| Set & setting | Room design, music, lighting, eye shades, intention-setting, pre-session expectations | Shapes whether the environment feels clinical, chaotic, or genuinely calming |
| In-session presence | Non-directive support, when to speak and when to stay quiet, responding to distress or dissociation | Affects how supported you feel if the session becomes emotionally intense |
| Integration therapy | Structured sessions to process material, translate insight into behavior change, and coordinate with ongoing care | Determines whether the experience gets connected to your actual life or left to fade |
| Ethics, consent & boundaries | Informed consent under altered states, touch policies, power dynamics, scope of practice | Protects you during a window when you are unusually open and less able to advocate for yourself |
The medical portion tends to be the least negotiable. Ketamine's pharmacology, adverse-effect profile, and monitoring needs are well documented in the clinical literature (StatPearls), and any program worth its tuition covers screening, dissociative and cardiovascular effects, and emergency protocol. In practice, this is the part of ketamine assisted psychotherapy training that teaches a clinician to notice that your blood pressure reading is trending up mid-session and to know what the protocol says to do about it.
The psychotherapeutic portion varies far more. Program length runs from short intensives to multi-month certificate tracks that include supervision, case consultation, and — in many programs — a personal experiential session so the clinician has felt what they're asking patients to go through. Hours and requirements differ by program and are published on each program's own page.
Two domains deserve your attention as a patient. In-session presence is a skill, not a personality trait: knowing when silence is supportive and when it's neglect. Integration is where the therapeutic work usually happens — our step-by-step breakdown of how ketamine-assisted psychotherapy works, step by step walks through that phase in detail.
Key takeaway: Ask a clinic which of these five domains its clinicians trained in — a vague "we're certified" answer usually means the psychotherapy half was thin.
How Does KAP Training Differ From Standard Infusion Training?
Infusion training centers on medical safety: dosing calculations, hemodynamic monitoring, airway management, and emergency response. KAP training assumes those medical basics are handled and adds psychotherapeutic skill on top.
Both models are legitimate. They are built for different goals, and they cost and feel different.
| Element | Monitored IV infusion | Ketamine-assisted psychotherapy |
|---|---|---|
| Primary focus | Medical delivery and physiological safety | Medicine plus structured therapeutic process |
| Who is in the room | Nurse or prescriber monitoring vitals, often checking in periodically | A trained facilitator or therapist present for the session |
| Typical time block | Roughly a 40-minute infusion plus recovery and observation | Commonly a 2–3 hour block including preparation and integration |
| Before the session | Medical screening and consent | Screening plus one or more dedicated preparation sessions |
| After the session | Recovery, vitals check, discharge with a driver | A scheduled integration conversation, same day or within days |
| Main cost drivers | Medication, nursing time, facility monitoring | All of the above plus clinician time across preparation and integration |
| Best suited for | Patients who want a streamlined medical protocol | Patients who want the experience connected to ongoing therapy |
Monitoring requirements are not arbitrary. For the FDA-approved esketamine nasal spray, the prescribing information requires administration in a certified healthcare setting under a restricted program, with direct observation by a healthcare provider and monitoring for at least two hours after dosing (SPRAVATO prescribing information, FDA). That gives you a useful benchmark: if a provider treats post-dose observation as optional, that's worth questioning.
The practical difference patients notice most is what happens in the final hour. In a medically focused model, the visit ends when vitals are stable. In KAP, that hour is often where the conversation starts. Our walkthrough of what a ketamine-assisted psychotherapy session involves shows how that block is structured.
⚠️ Neither model is automatically "better." The right fit depends on whether you already have a therapist, how much structure you want, and what you can budget in time and cost. Suitability is decided in a clinical consultation, not on a website.
Who Can Take KAP Training — And What Credential Do They Get?
Enrollment in most KAP programs is limited to licensed clinicians — commonly LCSWs, LPCs, LMFTs, psychologists, APRNs, PAs, and physicians. Graduates receive a certificate of completion, which is documentation that a person finished a specific curriculum from a specific organization.
A certificate of completion is a record of training, not a protected title and not a government license. It does not expand what a clinician is legally allowed to do.
⚠️ As of 2026, there is no single federally recognized certification board for ketamine-assisted psychotherapy in the United States. Certificate quality and rigor vary widely between programs, and the word "certified" on a clinic page can mean anything from a weekend webinar to months of supervised practice. Ask which program, how many hours, and whether supervision was included.
Scope of practice still governs everything. Only licensed prescribers can order and administer ketamine. Therapists without prescriptive authority collaborate — they handle preparation, session support, and integration while a prescriber manages medical decisions. A well-run clinic makes that division explicit, and you can see how roles are split across our Boise and Eagle care team.
Here's what a training credential does and doesn't tell you:
- It tells you the clinician sought out education beyond their baseline license.
- It tells you which framework they were taught — psychodynamic, somatic, non-directive, or a blend.
- It doesn't tell you how many KAP sessions they've actually facilitated.
- It doesn't tell you whether the program required supervised practice or just lectures.
- It doesn't replace their underlying license, malpractice coverage, or medical backup plan.
Treat the certificate as a starting question, not an answer.
Why Does Clinician Training Change the Patient Experience?
Training shapes the three variables patients feel most directly: how thoroughly they're prepared, how responsive the room is during dosing, and whether integration actually gets scheduled.
Depression is a complex condition with multiple evidence-based treatment paths, and treatment plans are individualized (National Institute of Mental Health). Across the clinical research on ketamine and esketamine for difficult-to-treat depression, the medicine is consistently studied within a structured clinical framework — screening, supervised administration, defined monitoring, and follow-up. The FDA-approved esketamine label formalizes that with its REMS and post-dose observation requirements (FDA prescribing information).

How does training show up in ketamine therapy for depression?
It shows up in specifics rather than slogans. A well-prepared clinician will have a clear plan for each of these:
- Preparation — what you should expect, what your intention is, what happens if the session feels overwhelming.
- Responsiveness — recognizing the difference between productive emotional intensity and distress that needs grounding.
- Integration timing — many practitioners aim to schedule follow-up conversations close to the dosing session, working with the idea that the period afterward is a useful window for reflection. The reasoning behind that approach is explained in our overview of how ketamine works on the brain.
- Coordination — communicating with your existing prescriber or therapist rather than operating in isolation.
What does trained versus untrained support look like in the room?
The clearest way to see the difference is to compare the same three moments under two different models. The scenarios below are illustrative composites — not descriptions of specific patients — but they reflect the kinds of decisions KAP curricula actually drill.
| Moment in the session | A room without psychotherapy training | A room with KAP training |
|---|---|---|
| You start crying 20 minutes in | Staff ask if you'd like the session stopped, treating tears as an adverse event | The facilitator stays quiet, offers a grounding cue, and lets the emotion run its course while watching vitals |
| You say something cryptic mid-dose | It's noted in the chart and not revisited | It's written down and gently returned to during integration, when you can actually work with it |
| You leave feeling raw and unsure | You're discharged once your blood pressure is stable | You're discharged with a scheduled integration conversation and a plan for the next 48 hours |
Here's one more concrete example of how preparation changes things. A patient who is told beforehand that dissociation can feel like floating, time distortion, or watching themselves from a distance tends to interpret those sensations as expected rather than alarming. A patient who hears nothing about it in advance may spend the first half of the session trying to figure out whether something has gone wrong. Same medicine, same dose, very different hour.
To be transparent about the evidence: training is a proxy for process quality, not a guarantee of results. Outcomes vary between individuals, and no credential changes that. What training reliably changes is how structured, consistent, and well-documented your care is.
Key takeaway: You can't evaluate a clinician's skill from a website, but you can evaluate their process — and process is what training builds.
How Do You Vet a KAP Provider in Boise or Eagle?
Ask six questions. Any clinic worth choosing will answer all of them without hesitation, ideally in writing.
- Who prescribes the ketamine? Get the prescriber's name, license type, and whether they're on site during dosing.
- Who will physically be in the room with me? A nurse checking vitals and a therapist sitting with you are different roles.
- What KAP training did that person complete? Which program, roughly how many hours, and did it include supervised practice?
- How is integration scheduled? Is it built into the package, billed separately, or left to you to arrange?
- What is the medical emergency protocol? Who responds, what equipment is on site, and how are vitals monitored throughout?
- What is the total per-session time and cost? Including preparation, dosing, observation, and integration — not just the infusion itself.
What do good and vague answers actually sound like?
Specificity is the tell. Compare these examples, drawn from the same six questions:
| Question | A vague answer | A specific answer |
|---|---|---|
| Who's in the room? | "Our team takes great care of you." | "A registered nurse monitors vitals, and a licensed therapist sits with you for the full session." |
| What training? | "All our staff are ketamine certified." | "She completed a multi-month KAP certificate program that included supervised case consultation — here's the program name." |
| How is integration scheduled? | "We follow up after treatment." | "Integration is a 50-minute session booked within 48 hours, and it's included in the package price." |
| Emergency protocol? | "We're a medical facility." | "A prescriber is on site, we monitor blood pressure and oxygen throughout, and here's our written protocol." |
Idaho does not license "ketamine clinics" as a distinct regulatory category. Clinics operate under the licenses of their individual clinicians and their medical facility requirements. That means the vetting burden sits with you — which is exactly the kind of thing a consultation should resolve rather than deepen.
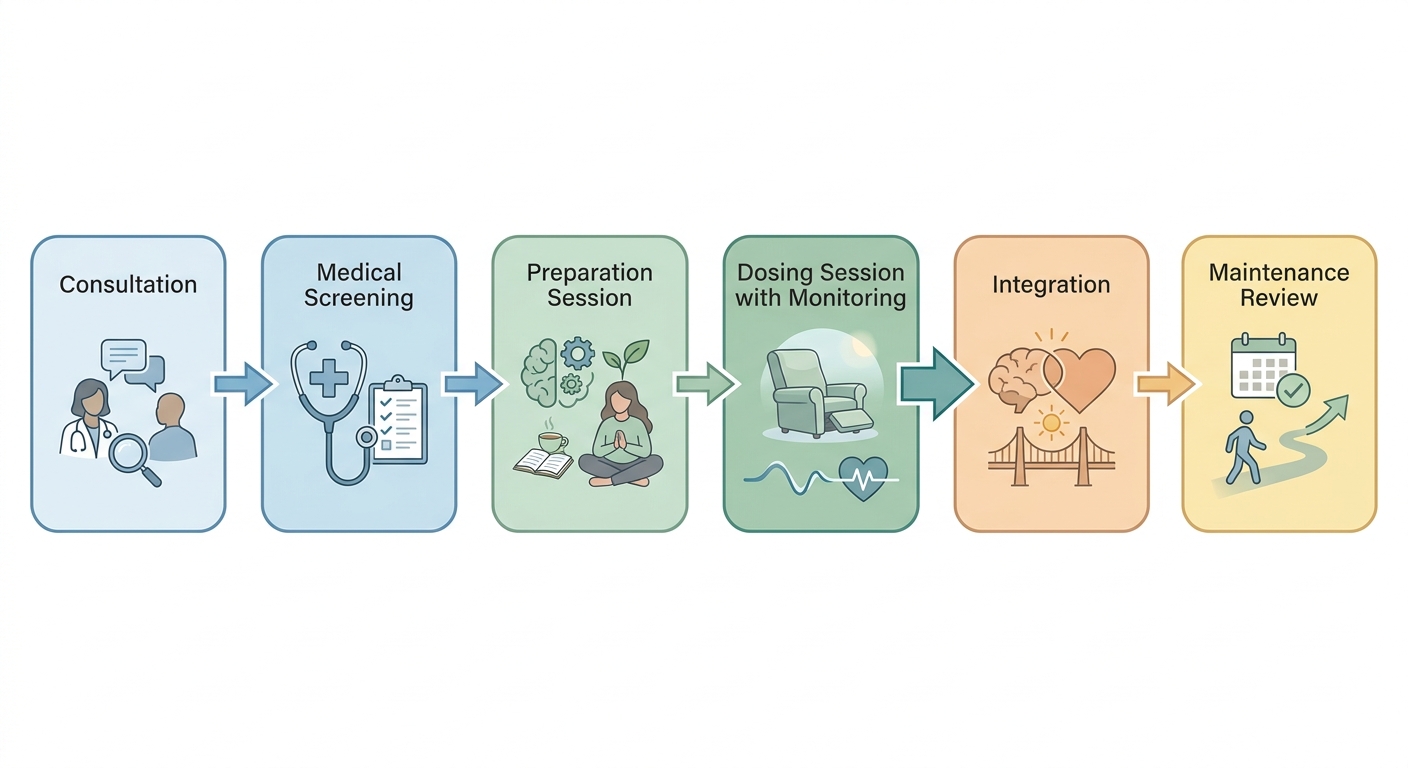
A good consultation should leave you with names, roles, a schedule, and a number — not a brochure. That's how we run ours: we walk through who prescribes, who sits with you, what training they hold, and what a realistic course of care looks like for your situation. If you want the cost and safety details before you call, they're laid out in our ketamine therapy cost, safety and process FAQ.
If a clinic can't tell you who will be in the room, that's your answer.
What Does a Full KAP Course of Care Look Like Start to Finish?
A course of care is a sequence of phases, not a single appointment. The exact schedule is set by your prescriber after screening, but the shape is generally consistent.
- Intake and medical screening — full history, current medications, blood pressure, and a discussion of whether ketamine is appropriate for you at all. Some people are screened out here, and that's a feature of good care.
- Preparation session(s) — one or more conversations covering expectations, intentions, logistics, and what to do if the experience feels difficult. Our guide to preparing for your first ketamine session covers the practical side.
- Dosing sessions — a series scheduled over several weeks, with the number and spacing determined by your prescriber. Details of the administration setting are outlined on our IV ketamine therapy in Boise and Eagle page.
- Integration — a structured conversation after each dosing session, or grouped at intervals, depending on the plan.
- Maintenance review — a check-in to discuss what to do next, which may mean spacing sessions out, pausing, or changing approach.
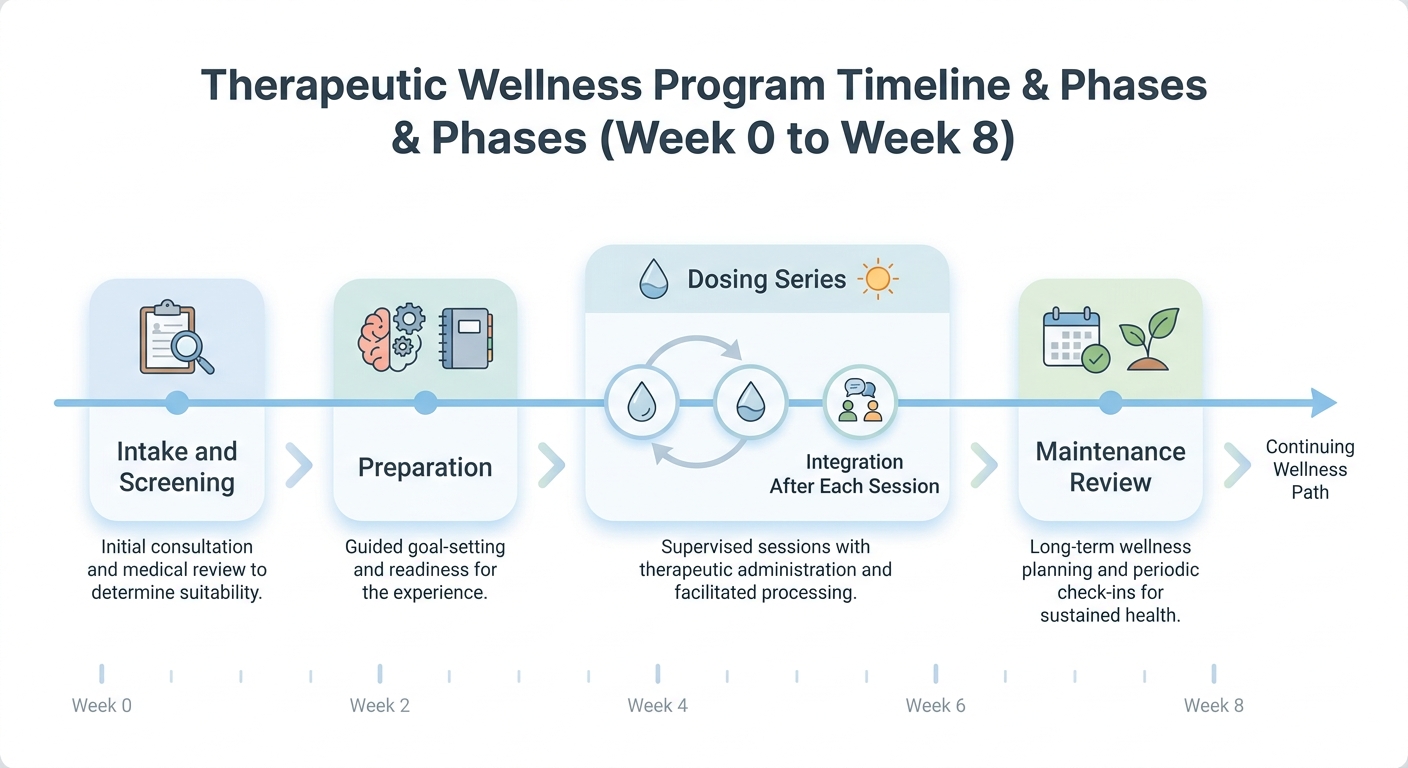
Throughout, you'll need a ride home after every dosing session and should plan a low-demand rest of the day. Costs generally reflect clinician time as much as medication, which is why a KAP block prices differently from a monitored infusion.
A practical example of what that means for your calendar: if your prescriber plans a series over several weeks, you're not booking one appointment — you're booking a preparation conversation, a run of dosing sessions with a driver lined up for each, integration time after them, and a review at the end. People who map that out in advance, including work schedules and childcare, tend to have a much smoother course than people who book the first session and improvise from there.
Key takeaway: Ask for the whole schedule up front — intake through maintenance review — so you can compare providers on the full course of care rather than a single session price.
Frequently Asked Questions
Is KAP training required to legally offer ketamine therapy?
No. Ketamine is prescribed off-label for psychiatric use by licensed prescribers, and no state currently requires a KAP certificate to do so. Idaho also doesn't license ketamine clinics as a separate category. That's precisely why voluntary training is a meaningful differentiator — it's a choice a clinician made rather than a box they were forced to tick. It also means you should ask about training specifically, because nothing obligates a clinic to volunteer it.
How much does ketamine-assisted psychotherapy training cost clinicians?
Tuition varies widely depending on program length, whether supervision is included, and whether there's an experiential component. Programs publish current pricing on their own websites, and figures change year to year, so the only reliable number is the one on the program's own page. As a patient, the more useful question isn't what it cost — it's how many hours the program ran and whether supervised practice was part of it.
Can my existing therapist join my ketamine sessions?
Often, yes. Many clinics support a collaborative model where your outside therapist handles preparation and integration while the clinic manages prescribing, dosing, and medical monitoring. It requires coordination: a release-of-information form, a shared understanding of roles, and agreement on who does what if something comes up mid-session. Ask both your therapist and the clinic early, since scheduling and paperwork take time to arrange.
Does KAP work better than ketamine infusions alone?
Honest answer: the evidence base for ketamine's use in difficult-to-treat depression is far more developed than the evidence comparing KAP directly against infusion-only care. As of 2026, head-to-head research on whether adding structured psychotherapy improves outcomes is promising but still limited. Clinicians who favor KAP argue that structured preparation and integration help patients make use of the experience — that's a reasoned position, not a proven superiority claim. For local context, see our overview of ketamine for depression in Boise.
What are the most common ketamine therapy side effects?
The documented effects of ketamine include dissociation, sedation, dizziness, nausea, and short-term increases in blood pressure and heart rate (StatPearls). Most are dose-related and short-lived, which is why monitored administration and post-dose observation exist in the first place. Training matters here too: a clinician who has studied ketamine therapy side effects in depth knows which sensations are expected, which ones warrant a pause, and how to explain the difference to you beforehand so you're not guessing mid-session. Your own risk profile is reviewed during medical screening, not from an article.
How does ketamine assisted psychotherapy work from the patient's side?
In sequence. You're screened, then you sit down for at least one preparation conversation about expectations and intentions. On dosing day you're settled in a quiet room with monitoring in place, and a trained clinician stays present through the experience. Afterward — same day or within a few days — you have an integration conversation to put words to what came up and decide what to carry into daily life. That preparation-dosing-integration loop is the defining structure of ketamine psychotherapy, and it's what distinguishes it from a medication appointment.
Do you see patients from Middleton and elsewhere in the Treasure Valley?
Yes. Our locations are in Boise and Eagle, and people travel in from across the wider Treasure Valley, including Middleton, for assisted psychotherapy and infusion-based care. If you're coming from outside Boise or Eagle, plan the logistics early — you can't drive yourself home after a dosing session, so a ride is part of the appointment, not an optional extra. It's worth raising travel distance during your consultation so sessions can be scheduled in a way that works with the drive.
Key Takeaways
Before you pick up the phone, here's the short version of everything above:
- Training and treatment are different things. Ketamine assisted psychotherapy training is education a clinician completes; KAP treatment is what you receive.
- Five domains define a credible curriculum: pharmacology and screening, set and setting, in-session presence, integration therapy, and ethics.
- Infusion care and ketamine psychotherapy are built for different goals. One prioritizes medical delivery; the other adds structured preparation and integration around it.
- "Certified" is not a regulated claim. Ask for the program name, the hour count, and whether supervision was included.
- Process is the thing you can actually evaluate. Specific answers about roles, scheduling, monitoring, and cost tell you more than any credential list.
- Safety details stay with your clinician. Suitability, dosing, and ketamine therapy side effects are assessed in a medical screening, and results vary between individuals.
Where to Go From Here
Training is what separates a medicine appointment from a therapeutic process. When you understand what KAP curricula cover — screening, setting, presence, integration, and ethics — you stop comparing clinics on price alone and start comparing them on process, which is the thing you'll actually experience.
If you're weighing ketamine therapy for depression, anxiety, PTSD, OCD, chronic pain, or migraines in the Boise and Eagle area, take the six questions from this article to every provider you contact. Suitability is always determined in a clinical consultation, and results vary between individuals — but the quality of the conversation you have before treatment tells you a great deal about the quality of the care that follows.
Clinical statements in this guide are drawn from published sources — FDA prescribing information for esketamine, the StatPearls ketamine monograph on NCBI Bookshelf, and the National Institute of Mental Health — and are general education, not medical advice. Training program details vary by organization and change over time; verify them directly with the program. Information about third-party platforms reflects publicly available details at the time of writing and may have changed. Please verify directly with the provider. See our Terms of Use for more.